Related Experiment Video
Updated: Sep 27, 2025


Validated Immunochemical Assay for Comprehensive Determination of the Human Epidermal Growth Factor Receptor 2 Released from and Bound to Cells
Published on: May 9, 2025
Endocrine Therapy Response and 21-Gene Expression Assay for Therapy Guidance in HR+/HER2- Early Breast Cancer
Ulrike A Nitz1,2, Oleg Gluz1,2,3, Sherko Kümmel1,4,5
1West German Study Group, Moenchengladbach, Germany.

Purpose:
To our knowledge, WSG-ADAPT-HR+/HER2- (ClinicalTrials.gov identifier: NCT01779206; n = 5,625 registered) is the first trial combining the 21-gene expression assay (recurrence score [RS]) and response to 3-week preoperative endocrine therapy (ET) to guide systemic therapy in early breast cancer.
Materials And Methods:
Baseline and postendocrine Ki67 (Ki67post) were evaluated centrally. In the endocrine trial, all patients received exclusively ET: patients with pathologic regional lymph node status (pN) 0-1 (ie, 0-3 involved lymph nodes) entered control arm if RS ≤ 11 and experimental arm if RS12-25 with ET response (Ki67post ≤ 10%). All other patients (including N0-1 RS12-25 without ET response) received dose-dense chemotherapy (CT) followed by ET in the CT trial. Primary end point of the endocrine trial was noninferiority of 5-year invasive disease-free survival (5y-iDFS) in experimental (v control) arm; secondary end points included distant DFS, overall survival, and translational research.
Results:
Intention-to-treat population comprised 2,290 patients (n = 1,422 experimental v n = 868 control): 26.3% versus 34.6% premenopausal and 27.4% versus 24.0% pN1. One-sided 95% lower confidence limit of the 5y-iDFS difference was -3.3%, establishing prespecified noninferiority (P = .05). 5y-iDFS was 92.6% (95% CI, 90.8 to 94.0) in experimental versus 93.9% (95% CI, 91.8 to 95.4) in control arm; 5-year distant DFS was 95.6% versus 96.3%, and 5-year overall survival 97.3% versus 98.0%, respectively. Differences were similar in age and nodal subgroups. In N0-1 RS12-25, outcome of ET responders (ET alone) was comparable with that of ET nonresponders (CT) for age > 50 years and superior for age ≤ 50 years. ET response was more likely with aromatase inhibitors (mostly postmenopausal) than with tamoxifen (mostly premenopausal): 78.1% versus 41.1% (P < .001). ET response was 78.8% in RS0-11, 62.2% in RS12-25, and 32.7% in RS > 25 (n = 4,203, P < .001).
Conclusion:
WSG-ADAPT-HR+/HER2- demonstrates that guiding systemic treatment by both RS and ET response is feasible in clinical routine and spares CT in pre- and postmenopausal patients with ≤ 3 involved lymph nodes.
Insights
This study shows that using the 21-gene recurrence score (RS) and endocrine therapy (ET) response can guide treatment for early breast cancer, successfully avoiding chemotherapy in many patients. This personalized approach improves outcomes and reduces treatment burden.
Area of Science:
- Oncology
- Genomics
- Clinical Trials
Background:
- Early breast cancer treatment decisions often involve balancing efficacy with treatment burden.
- The 21-gene recurrence score (RS) and response to endocrine therapy (ET) are emerging biomarkers for guiding treatment.
Purpose of the Study:
- To evaluate the feasibility and efficacy of combining the 21-gene recurrence score (RS) and response to preoperative endocrine therapy (ET) to guide systemic treatment in early HR+/HER2- breast cancer.
- To determine if this combined approach can spare patients from chemotherapy.
Main Methods:
- The WSG-ADAPT-HR+/HER2- trial (NCT01779206) enrolled 5,625 patients.
- Patients were stratified based on RS and response to 3-week ET (assessed by Ki67 reduction).
- Treatment arms included ET alone or dose-dense chemotherapy followed by ET, guided by RS and ET response.
Main Results:
- Noninferiority of 5-year invasive disease-free survival (5y-iDFS) was established for the experimental arm (92.6%) versus the control arm (93.9%).
- Chemotherapy was avoided in a significant proportion of patients, particularly those with a low RS or good ET response.
- Endocrine therapy response varied by RS and menopausal status, being higher with aromatase inhibitors.
Conclusions:
- Combining RS and ET response is a feasible strategy for guiding systemic therapy in early HR+/HER2- breast cancer.
- This approach successfully spares chemotherapy in eligible pre- and postmenopausal patients with limited lymph node involvement.
- Personalized treatment selection based on genomic and predictive biomarkers enhances treatment de-escalation.
Related Concept Videos
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against...
 02:50
Combination Therapies and Personalized Medicine
The combination of the drug acetazolamide and sulforaphane is a good example of combination therapy to treat cancer. The cells in the interior of a large tumor often die due to the hypoxic and...
 01:22
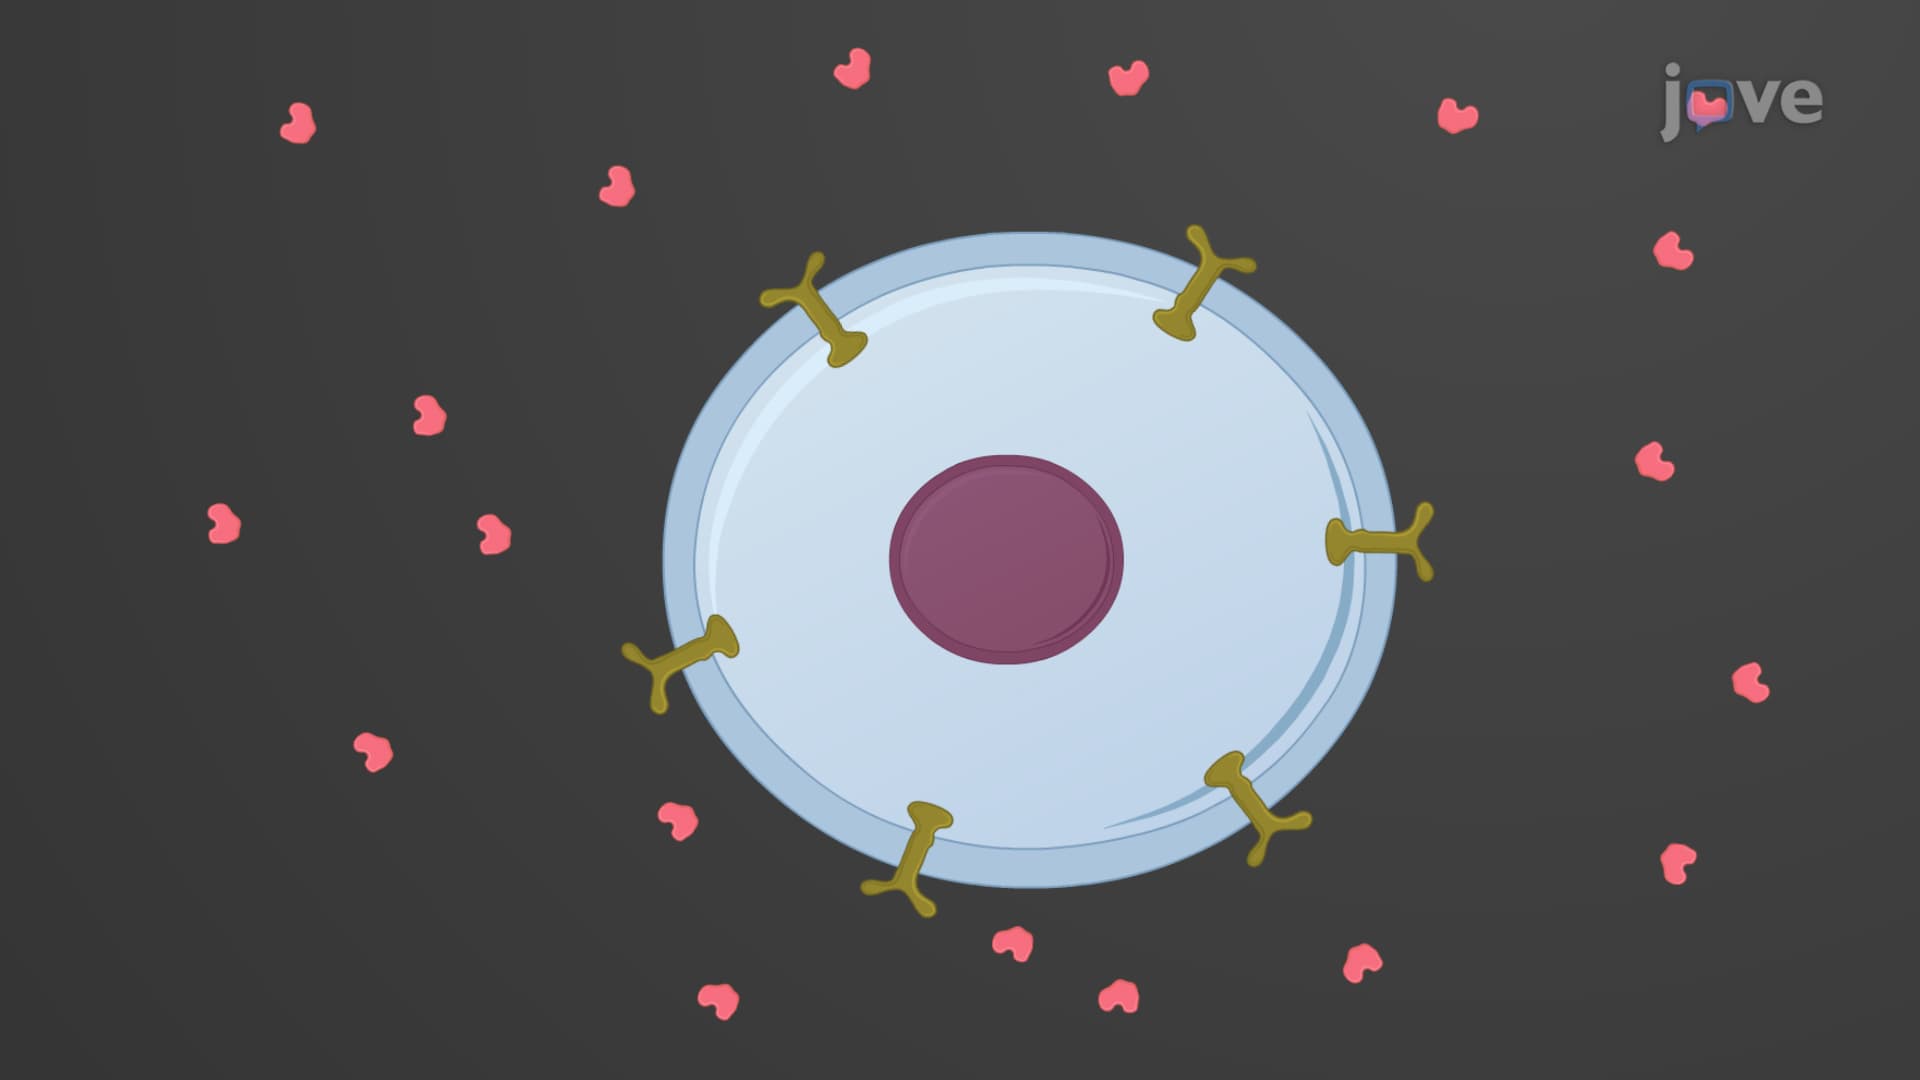
Target Cell Response to Hormones
Notably, the cellular response can be regulated by altering the number of receptors expressed in the cell. For example, prolonged exposure to elevated hormone levels results in a gradual decline or down-regulation in the number of receptors for that specific hormone on the cell surface. Conversely, in response to low hormone levels, cells may use up-regulation, producing an...
 02:38
Mitogens and the Cell Cycle