Related Experiment Video
Updated: Aug 7, 2026
Acupoint Needle-Embedding Combined with Ironing Therapy for Postoperative Pain After Anal Surgery
Published on: June 23, 2023
Ketorolac versus aspirin for postpartum uterine pain

Ketorolac tromethamine, a new nonsteroidal antiinflammatory analgesic, was evaluated for relative efficacy, safety and time course of analgesia in a stratified, randomized, parallel, double-blind trial. The study involved 120 hospitalized women (4 groups of 30) with moderate or severe postpartum uterine pain treated with single oral doses of ketorolac 5 mg and 10 mg, aspirin 650 mg or placebo. At regular interviews for 6 hours patients rated pain intensity, pain relief and side effects. Significant differences (p less than or equal to 0.05, two-tailed) occurred among the 4 treatments for various measurements of summed and peak analgesia. Ketorolac 10 mg was significantly superior to placebo in 5 of 5 major efficacy measurements, and aspirin was significantly superior in 3 of 5. Ketorolac 10 mg gave the highest mean rating for summed pain intensity differences (13.6, p = 0.0002 versus placebo), followed by aspirin (11.9, p = 0.012), ketorolac 5 mg (10.9, p = 0.072) and placebo (8.6). With ketorolac 10 mg and 5 mg and aspirin, analgesia lasted 6 hours, with peak efficacy at 3 hours. Side effects were not significant. Our results suggested a positive dose-response relationship for ketorolac. Compared to aspirin, ketorolac 10 mg induced equal or more analgesia, whereas ketorolac 5 mg was near the minimum effective dose and seemed less effective than aspirin.
Ketorolac tromethamine, a new nonsteroidal antiinflammatory analgesic, was evaluated for relative efficacy, safety and time course of analgesia in a stratified, randomized, parallel, double-blind trial. The study involved 120 hospitalized women (4 groups of 30) with moderate or severe postpartum uterine pain treated with single oral doses of ketorolac 5 mg and 10 mg, aspirin 650 mg or placebo. At regular interviews for 6 hours patients rated pain intensity, pain relief and side effects. Significant differences (p less than or equal to 0.05, two-tailed) occurred among the 4 treatments for various measurements of summed and peak analgesia. Ketorolac 10 mg was significantly superior to placebo in 5 of 5 major efficacy measurements, and aspirin was significantly superior in 3 of 5. Ketorolac 10 mg gave the highest mean rating for summed pain intensity differences (13.6, p = 0.0002 versus placebo), followed by aspirin (11.9, p = 0.012), ketorolac 5 mg (10.9, p = 0.072) and placebo (8.6). With ketorolac 10 mg and 5 mg and aspirin, analgesia lasted 6 hours, with peak efficacy at 3 hours. Side effects were not significant. Our results suggested a positive dose-response relationship for ketorolac. Compared to aspirin, ketorolac 10 mg induced equal or more analgesia, whereas ketorolac 5 mg was near the minimum effective dose and seemed less effective than aspirin.

Related Concept Videos
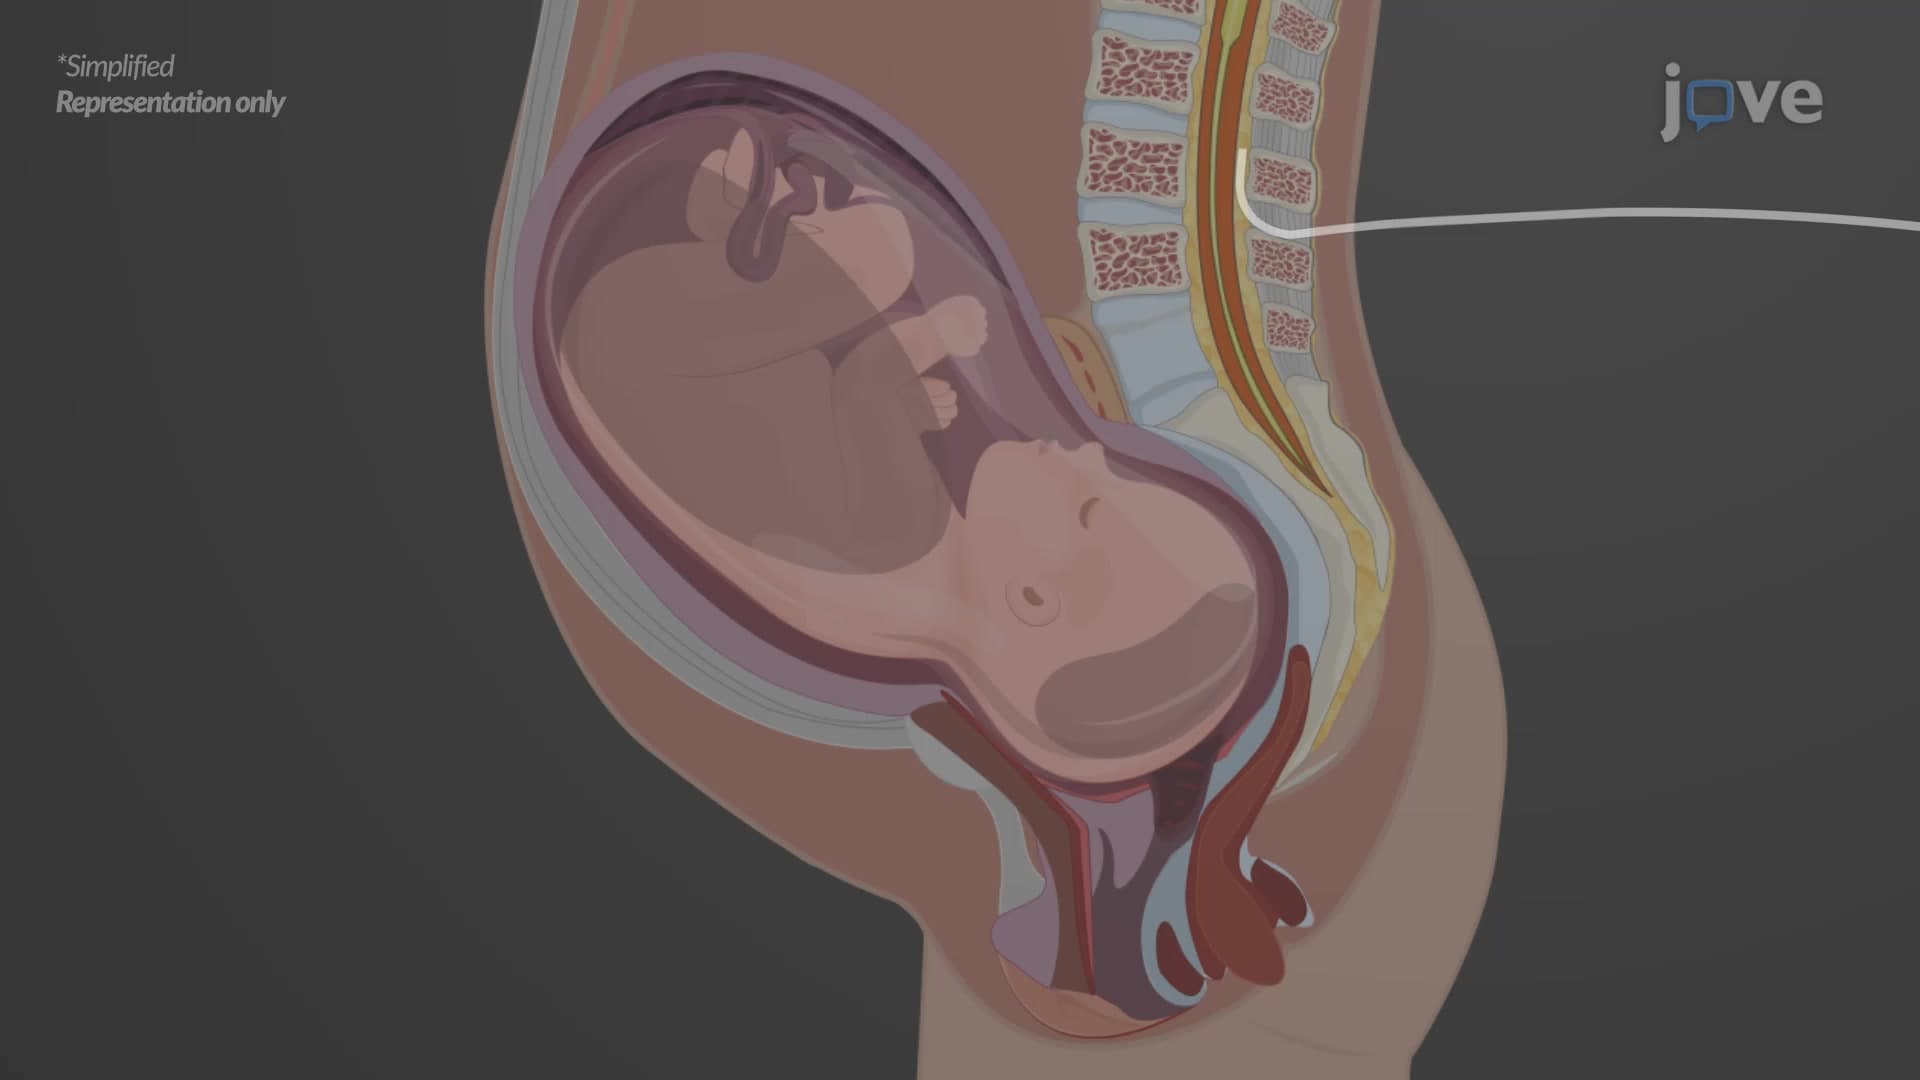 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:15
Opioid Analgesics: Synthetic and Semisynthetic Opioids
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...