Real world data of anticoagulant treatment in non-valvular atrial fibrillation across renal function status
Related Experiment Video
Updated: Sep 27, 2025

Catheter Ablation in Combination With Left Atrial Appendage Closure for Atrial Fibrillation
Published on: February 26, 2013
Jose Miguel Calderon1, Fernando Martinez1,2, Antonio Fernandez1
1Cardiovascular and Renal Research Group, INCLIVA Research Institute, University of Valencia, Avda Blasco Ibañez, 17, 46010, Valencia, Spain.

Insights
Anticoagulant treatment for non-valvular atrial fibrillation (AF) patients with kidney dysfunction reduces stroke and mortality risks. Novel oral anticoagulants (NOACs) provided superior protection compared to warfarin (VKA) and aspirin.
Area of Science:
- Cardiology
- Nephrology
- Pharmacology
Background:
- Non-valvular atrial fibrillation (AF) patients with renal dysfunction face elevated risks of stroke, TIA, intracranial hemorrhage, and mortality.
- Current guidelines recommend anticoagulation for AF patients with increased stroke risk (CHA2DS2-VASc Score ≥ 2).
- Real-world data on anticoagulant effectiveness across varying degrees of renal dysfunction (KDIGO categories) is crucial.
Purpose of the Study:
- To evaluate the real-world impact of anticoagulant treatments on non-valvular AF patients across different stages of renal dysfunction.
- To compare the effectiveness of different anticoagulant therapies (untreated, VKA, NOAC, aspirin) in mitigating adverse events.
- To assess the association between renal dysfunction severity and the risk of stroke, TIA, intracranial hemorrhage, and all-cause mortality.
Main Methods:
- Retrospective analysis of electronic health records from 65,734 AF patients over a 3.2-year follow-up.
- Patients were categorized into KDIGO stages (G1-G4) based on renal function.
- Cox-proportional hazard models were used to adjust for confounders and calculate event risks.
Main Results:
- The risk of stroke, TIA, and all-cause mortality significantly increased from KDIGO G1 to G4.
- Anticoagulant treatments, including VKA, NOAC, and aspirin, reduced the risk of these events across all renal dysfunction categories.
- Novel oral anticoagulants (NOACs) demonstrated significantly better protection against stroke, TIA, and all-cause mortality compared to VKAs and aspirin.
Conclusions:
- Renal dysfunction is an independent risk factor for adverse events in AF patients.
- Anticoagulant therapy is effective in reducing stroke and mortality in AF patients with varying degrees of renal impairment.
- NOACs appear to offer superior protection compared to VKAs and aspirin in this high-risk population, highlighting the need for optimized anticoagulant use.
Abstract:
The objective is to assess the impact of anticoagulant treatment in non-valvular atrial fibrillation (AF) and different categories of renal dysfunction in real world. Electronic Health recordings of patients with diagnosis of AF and renal function collected throughout 5 years and classified according to KDIGO categories. Stroke, transitory ischemic attack (TIA), intracranial hemorrhage and all-cause mortality were identified. Anticoagulant treatments during the study period were classified in untreated (never received therapy), VKA, NOAC and Aspirin. The risk of events was calculated by Cox-proportional hazard models adjusted by confounders. A total of 65,734 patients with AF, mean age 73.3 ± 10.49 years old and 47% females and follow-up of 3.2 years were included. KDIGO classification were: G1 33,903 (51.6%), G2 17,456 (26.6%), G3 8024 (12.2%) and G4 6351 (9.7%). There were 8592 cases of stroke and TIA, 437 intracranial hemorrhage, and 9603 all-cause deaths (incidence 36, 2 and 38 per 103 person/year, respectively). 4.1% of patients with CHA2DS2-VASc Score 2 or higher did not receive anticoagulant therapy. Risk of stroke, TIA, and all-cause mortality increased from G1 to G4 groups. Anticoagulant treatments reduced the risk of events in the four categories, but NOAC seemed to offer significantly better protection. Renal dysfunction increases the risk of events in AF and anticoagulant treatments reduced the risk of stroke and all-cause mortality, although NOAC were better than VKA. Efforts should be done to reduce the variability in the use of anticoagulants even in this high risk group.

Related Concept Videos
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:06
Renal Drug Clearance: Overview
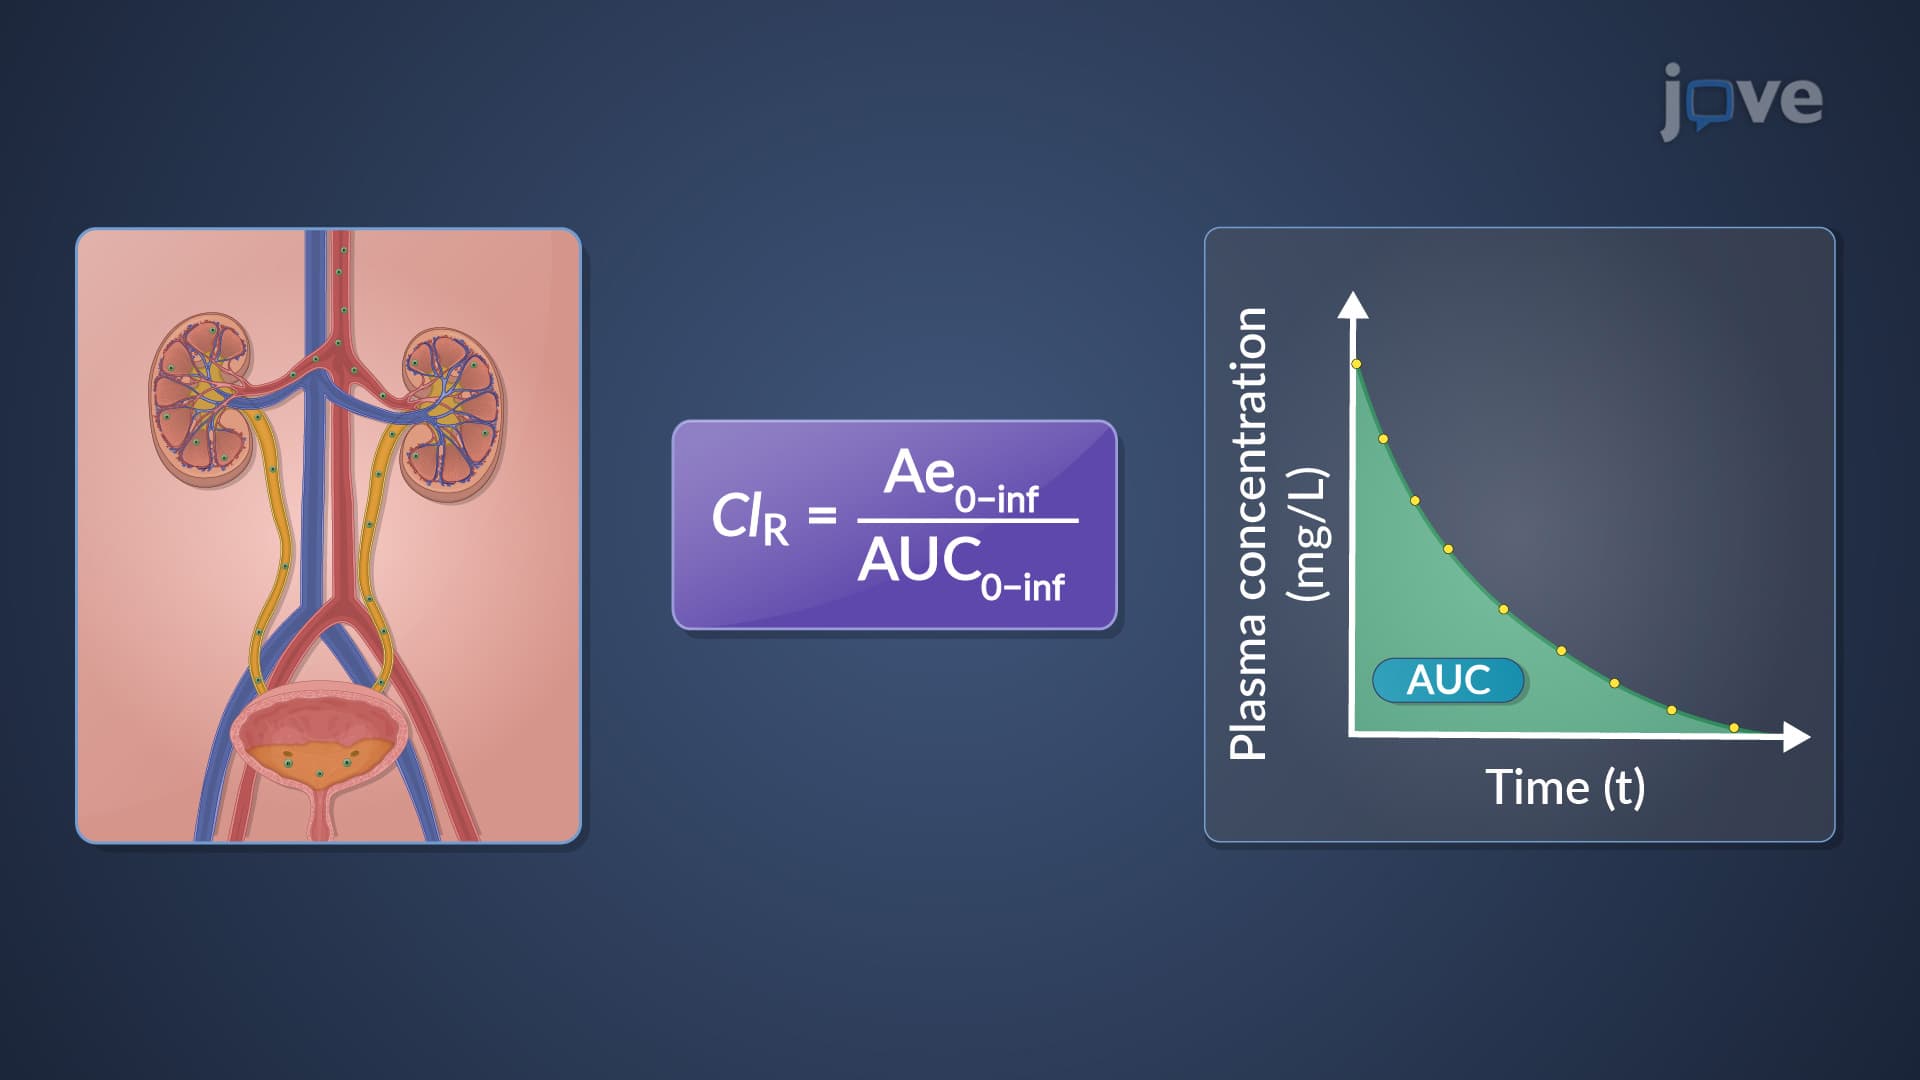
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:09
Factors Affecting Renal Clearance: Drug Distribution and Drug Interactions
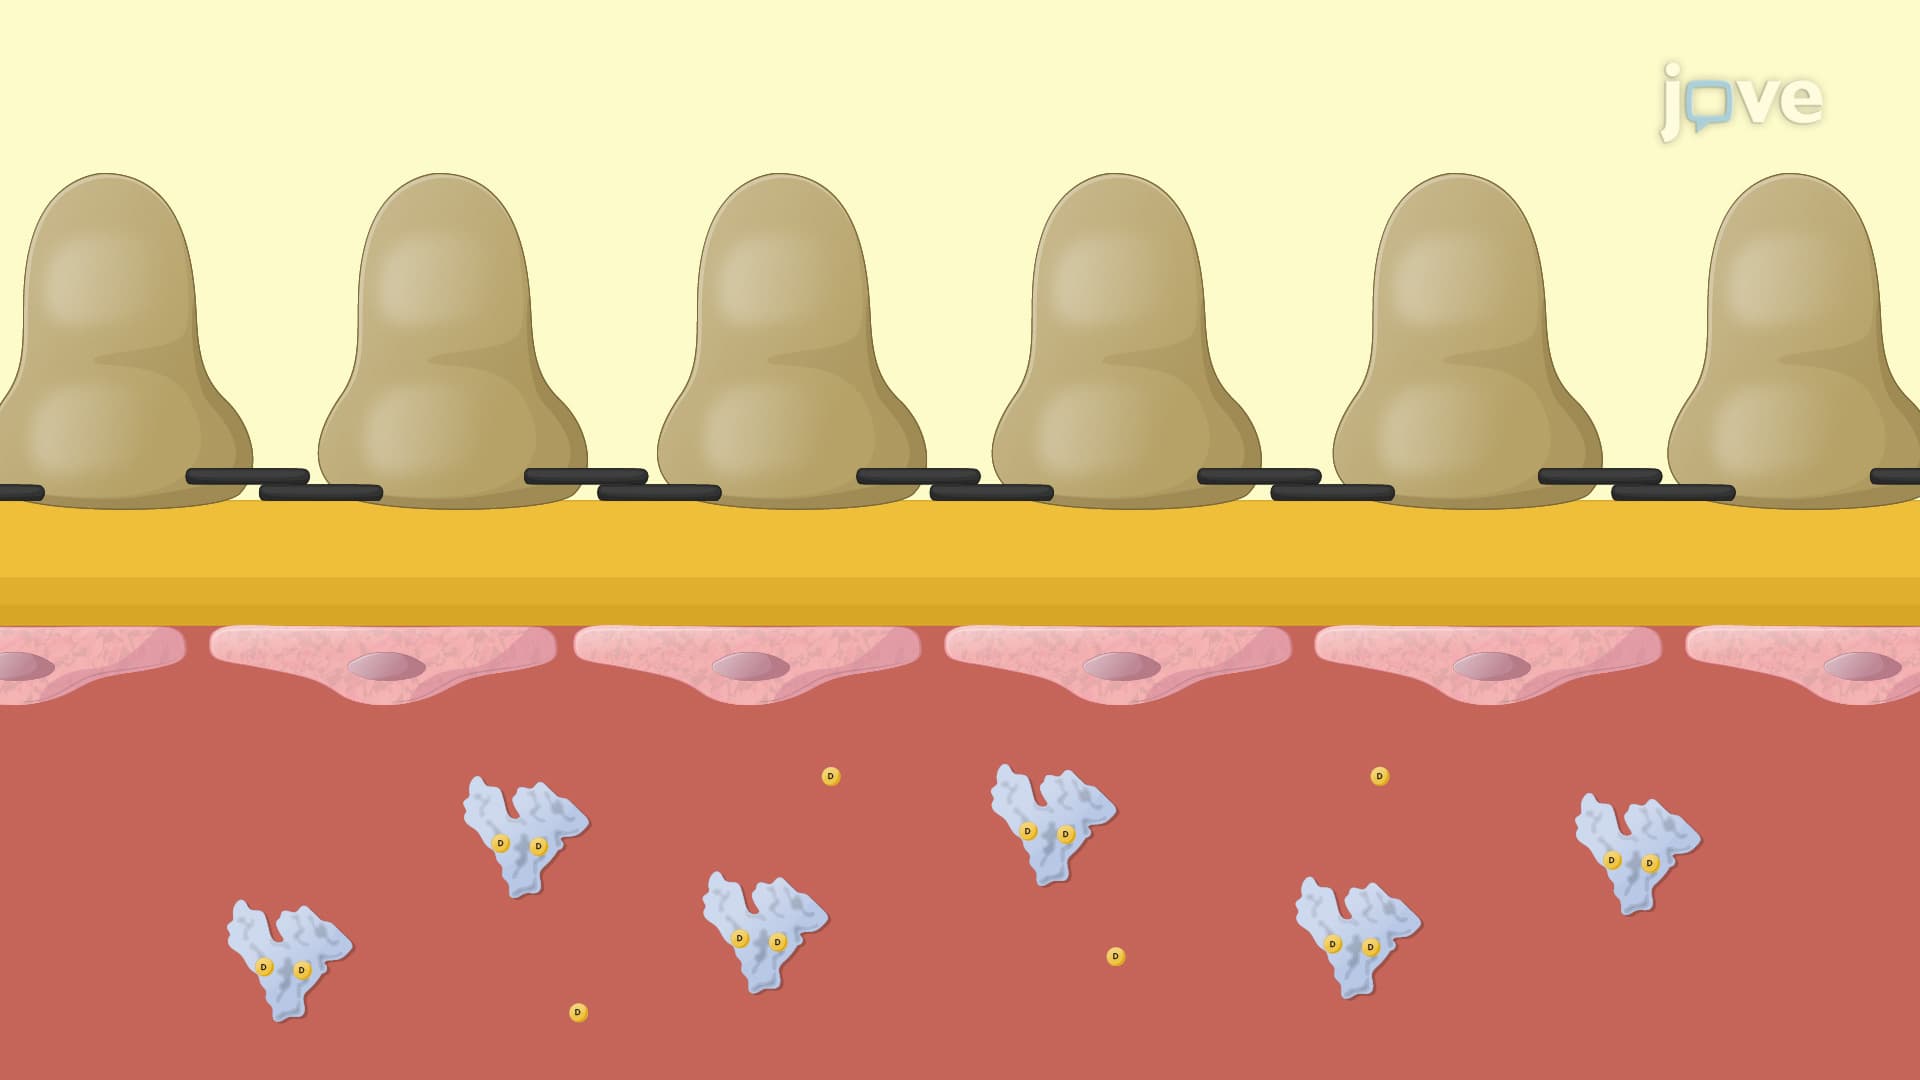
One important factor is the relationship between renal clearance and the apparent volume of distribution. Renal clearance tends to be inversely proportional to the apparent volume of distribution. Drugs with an extensive distribution volume or those...
 01:08
Renal Drug Clearance: Comparison Between Renal Excretion Methods
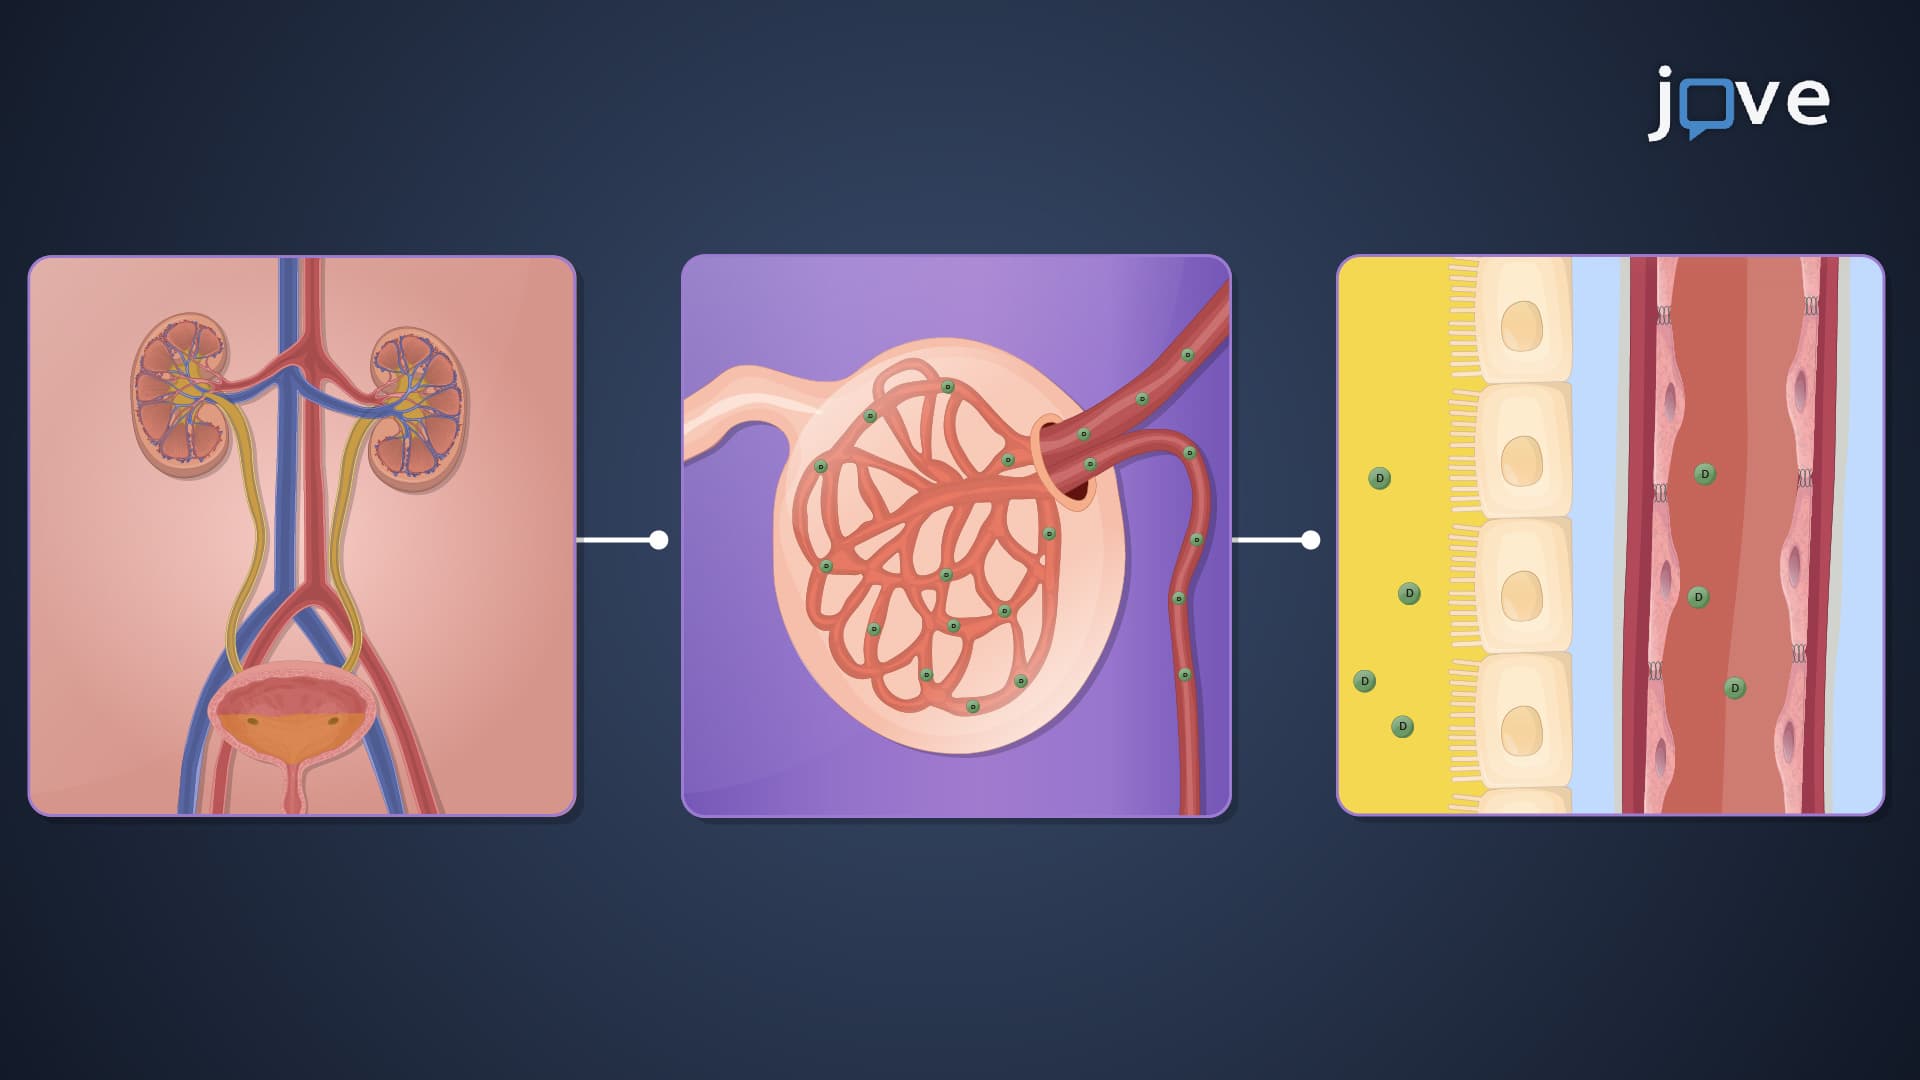
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...