Related Experiment Video
Updated: Sep 26, 2025
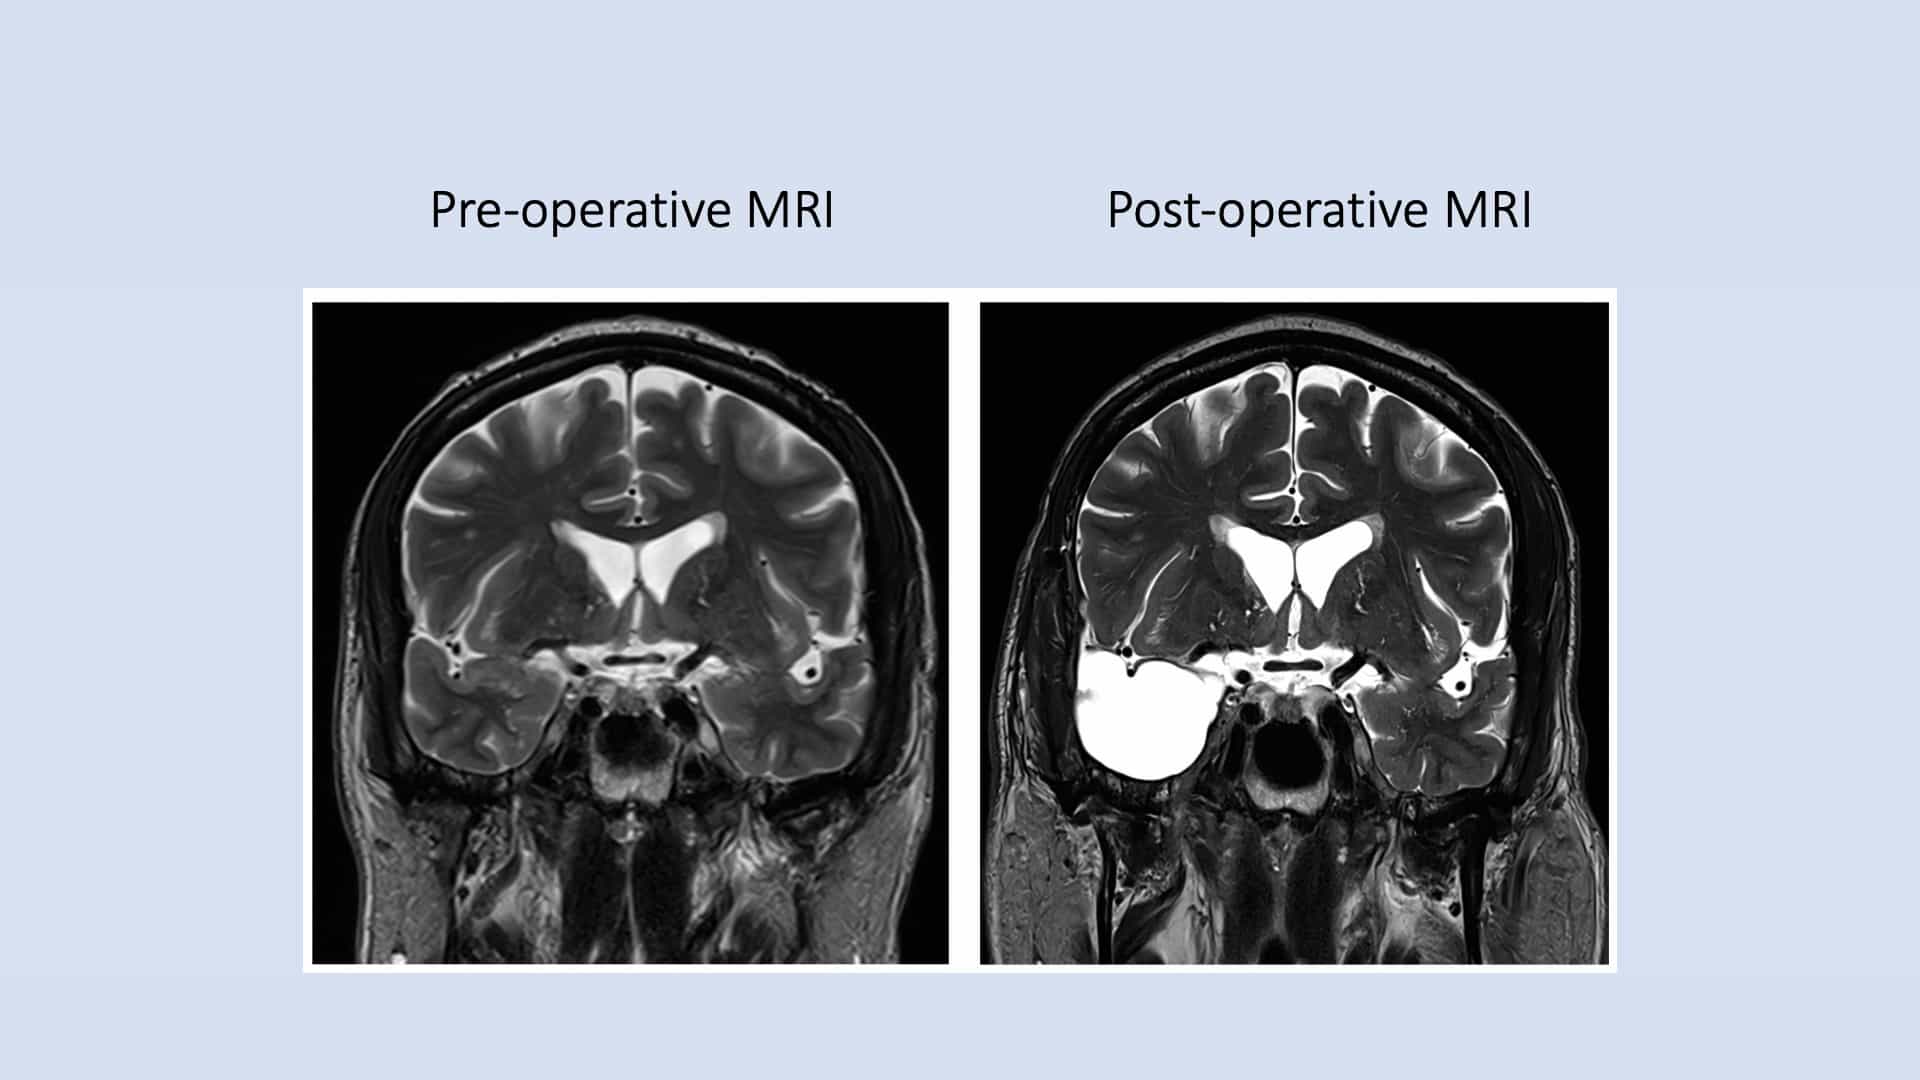
Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Epilepsy Surgery in Extratemporal vs Temporal Lobe Epilepsy: Changes in Surgical Volumes and Seizure Outcome Between
Anne Hagemann1, Christian G Bien1, Thilo Kalbhenn1
1From the Society for Epilepsy Research (A.H., C.G.B.); and Departments of Epileptology (Krankenhaus Mara) (C.G.B., J.L.H., P.G.) and Neurosurgery (Evangelisches Klinikum Bethel) (T.K.), Medical School, Bielefeld University, Germany.

Background And Objectives:
Seizure outcome after extratemporal lobe epilepsy (exTLE) surgery has often been poorer than after temporal lobe epilepsy (TLE) surgery, but recent improvements in diagnostics and surgery may have changed this. Our aim was to analyze the changes in presurgical and surgical volumes and seizure outcome 2 years after surgery for patients with exTLE compared with those with TLE.
Methods:
We performed a retrospective, single-center cohort study including patients from the Bethel presurgical-surgical-postsurgical database from 1990 to 2017. We used logistic regression to analyze factors influencing the odds for surgery and the odds for seizure freedom after surgery.
Results:
We included 3,822 patients with presurgical evaluation, 2,404 of whom had subsequently undergone surgery. The proportion of patients with exTLE in presurgical evaluation increased from 41% between 1990 and 1993 to 64% in 2014-2017. The odds for surgery decreased over time (2003-2011: odds ratio [OR] 0.50 [95% CI 0.36-0.70]; 2012-2017: OR 0.24 [CI 0.17-0.35]; reference: 1990-2002) and patients with exTLE had lower odds for surgery than patients with TLE, but this difference diminished over time (exTLE vs TLE 1990-2002: OR 0.14 [CI 0.09-0.20]; 2003-2011: OR 0.32 [CI 0.24-0.44]; 2012-2017: OR 0.46 [CI 0.34-0.63]). Etiology, the side of the epileptogenic lesion, and invasive recordings influenced the odds for surgery. The most frequent reasons for not undergoing surgery were missing identification of a circumscribed epileptogenic zone or an unacceptable risk of postsurgical deficits in patients with exTLE and the patient's decision in patients with TLE. Compared with patients with TLE, the odds for seizure freedom after surgery started lower for patients with exTLE in earlier years, but increased (≤2 lobes 1990-2002: OR 0.47 [CI 0.33-0.68]; 2003-2011: OR 0.62 [CI 0.44-0.87]; 2012-2017: OR 0.78 [CI 0.53-1.15]; ≥3 lobes 1990-2002: OR 0.37 [CI 0.22-0.62]; 2003-2011: OR 0.73 [CI 0.43-1.23]; 2012-2017: OR 1.46 [CI 0.91-2.42]). Etiology, age at surgery, and invasive recordings were further predictors for the odds for seizure freedom.
Discussion:
Over the past 28 years, the success of resective surgery for patients with exTLE has improved. At the same time, the number of patients with exTLE being evaluated for surgery increased, as well as their odds for undergoing surgery.
More Related Videos
 09:32
Network Analysis of Foramen Ovale Electrode Recordings in Drug-resistant Temporal Lobe Epilepsy Patients
Published on: December 18, 2016
 06:04
Author Spotlight: Studying Clinical Characters and Epilepsy Outcomes After Frontal Disconnection in Patients with MOGHE
Published on: August 16, 2024
