Related Experiment Video
Updated: Sep 26, 2025


Deep Neuromuscular Blockade Leads to a Larger Intraabdominal Volume During Laparoscopy
Published on: June 25, 2013
Risk factors for administration of additional reversal following neuromuscular blockade with rocuronium in children:
Susan R Vishneski1, Amit K Saha1, Madeline R Fram2
1Department of Anesthesiology, Wake Forest School of Medicine, Winston-Salem, North Carolina, USA.

Insights
Residual neuromuscular blockade in children is often treated with additional reversal agents. Key risk factors include short time to reversal, high rocuronium dose, low initial neostigmine dose, and African American race.
Area of Science:
- Anesthesiology
- Pediatric Anesthesia
- Pharmacology
Background:
- Residual neuromuscular blockade (RNB) in pediatric patients is not well understood.
- Risk factors for requiring additional reversal after initial rocuronium reversal are unclear.
Purpose of the Study:
- To identify patient and anesthetic factors associated with the need for additional reversal in children.
- To investigate risk factors for residual neuromuscular blockade after neostigmine reversal of rocuronium.
Main Methods:
- Retrospective electronic health record review of pediatric patients (<18 years) receiving rocuronium and neostigmine reversal (2017-2020).
- Defined outcome as administration of additional neostigmine or sugammadex post-initial reversal.
- Analyzed covariates including time to reversal, rocuronium dose, initial neostigmine dose, race, and monitoring use.
Main Results:
- 1.58% (101/6373) of patients required additional reversal.
- Significant risk factors included time <28 minutes from rocuronium to neostigmine (OR 1.52), cumulative rocuronium dose >0.45 mg/kg/hr (OR 1.71), initial neostigmine dose <0.05 mg/kg (OR 4.98), and African American race (OR 1.78).
Conclusions:
- Time to reversal, cumulative rocuronium dose, initial neostigmine dose, and African American race are associated with increased need for additional reversal.
- These findings highlight key factors contributing to residual neuromuscular blockade in pediatric patients.
- Optimizing reversal strategies may reduce the incidence of residual neuromuscular blockade.
Background:
The prevalence and risk factors for residual neuromuscular blockade in children remain poorly characterized. We hypothesize that specific patient and anesthetic risk factors may be associated with the administration of additional reversal in children following initial reversal of rocuronium with neostigmine.
Methods:
Our electronic health record was queried for patients <18 years of age who received rocuronium and reversal with neostigmine from 2017 through 2020. Patients receiving other nondepolarizing neuromuscular blocking drugs were excluded. The outcome of interest was defined as the administration of additional neostigmine or sugammadex following primary reversal with neostigmine. Time between the last dose of rocuronium and initial dose of neostigmine, and the cumulative dose of rocuronium were dichotomized. These were combined with other covariates including age, weight, sex, racial group, procedure type, ASA physical status, >1 rocuronium dose administered during the procedure, initial neostigmine dose <0.05 mg kg-1 , use of train-of-four monitoring, duration of anesthesia, inpatient or outpatient, emergency case, neuromuscular disease, and extremes of weight, to assess possible associations with the primary outcome.
Results:
During the study period, 101/6373 (1.58%) patients received rocuronium and additional reversal. Dichotomization of time between last dose of rocuronium and neostigmine yielded <28 min since the last dose of rocuronium and cumulative dose of rocuronium >0.45 mg kg-1 hr-1 . These were associated with the administration of additional reversal with an OR 1.52 (95% CI, 1.08-2.35) and OR 1.71 (95% CI, 1.10-2.67), respectively. Other risk factors included an initial neostigmine dose <0.05 mg kg-1 , OR 4.98 (95% CI, 2.84-6.49), and African American race, OR 1.78 (95% CI, 1.07-2.87).
Conclusion:
Risk factors associated with the administration of additional reversal included time <28 min from the last dose of rocuronium to initial dose of neostigmine, cumulative dose of rocuronium >0.45 mg kg-1 hr-1 , initial neostigmine dose <0.05 mg kg-1 , and African American race.

Related Concept Videos
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:17
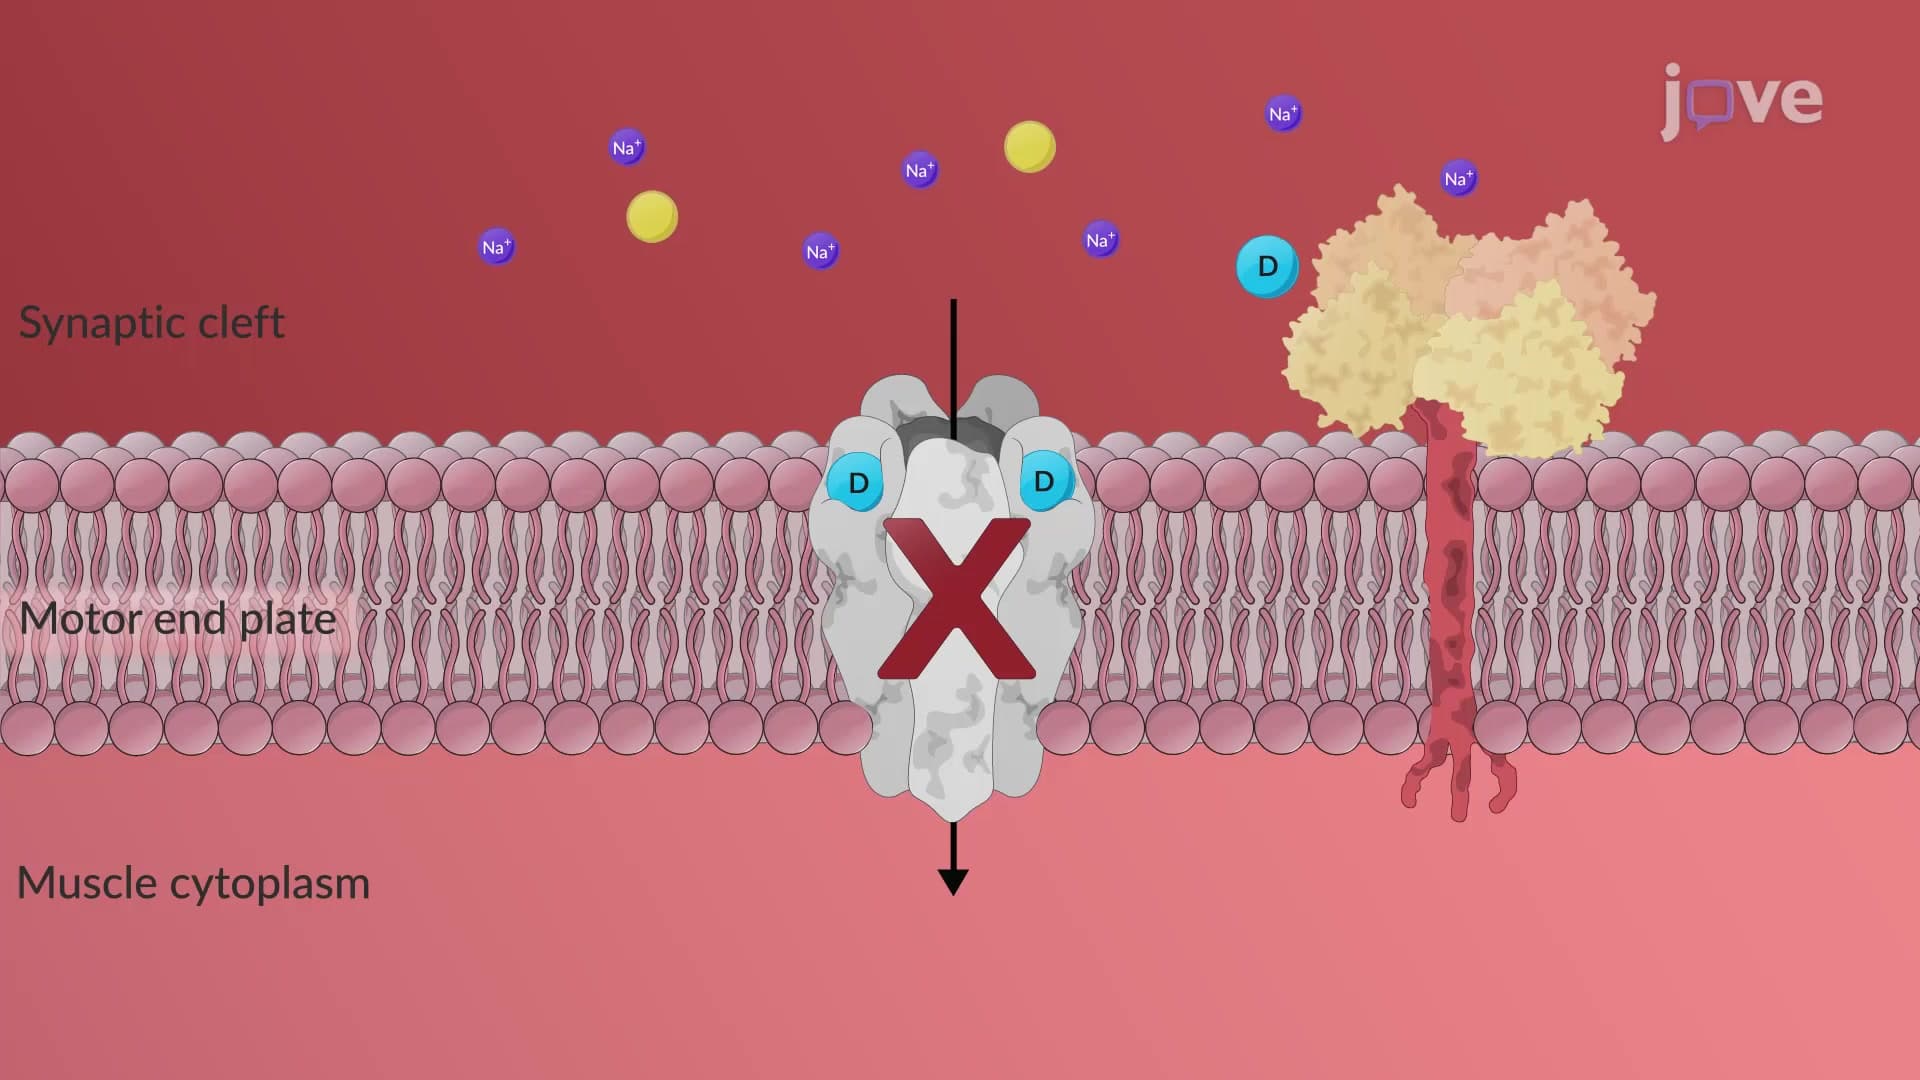
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...