Association Between the Frailty Index and Clinical Outcomes after Coronary Artery Bypass Grafting
Related Experiment Video
Updated: Sep 26, 2025
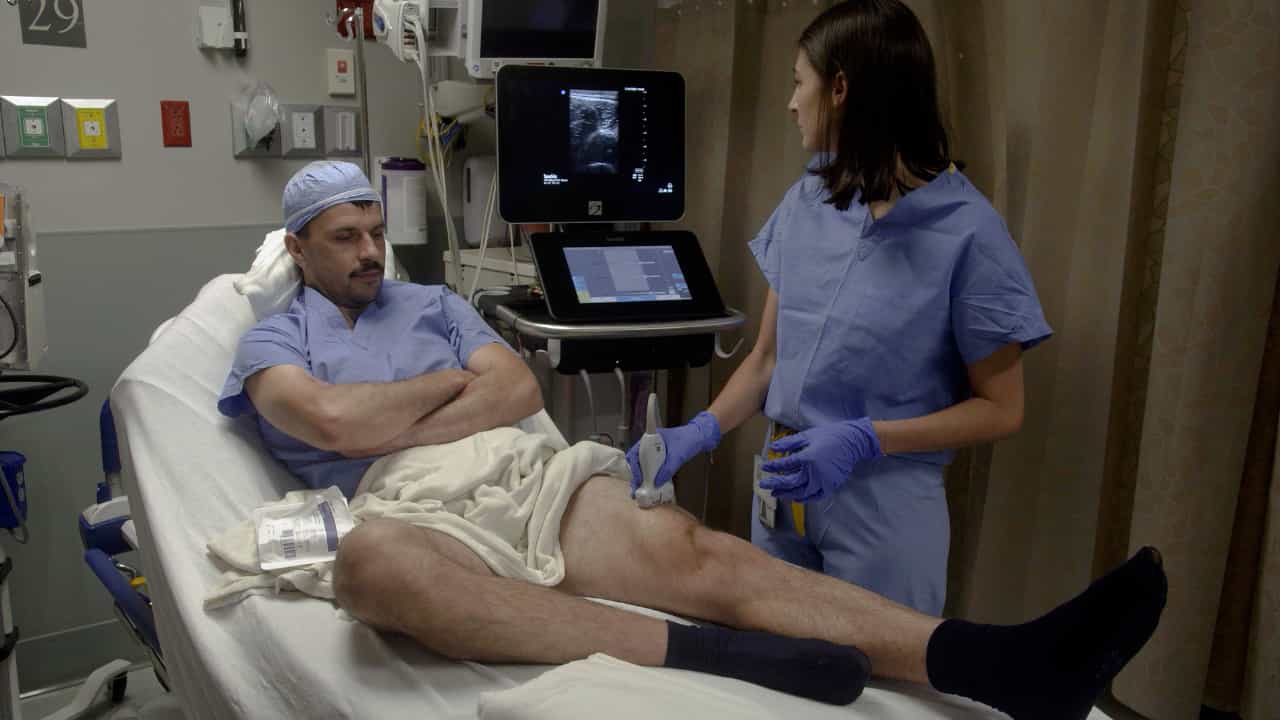
Author Spotlight: Assessing Surgical Frailty with Point-of-Care Ultrasound of Quadriceps Muscles
Published on: July 26, 2024
Chan Hyeong Kim1, Yoonjin Kang1, Ji Seong Kim1
1Department of Thoracic and Cardiovascular Surgery, Seoul National University Hospital, Seoul National University College of Medicine, Seoul, Korea.

Insights
The frailty index (FI-L), using lab data and vital signs, predicts mortality and complications after coronary artery bypass grafting (CABG). A 32% FI-L cutoff identifies high-risk patients for improved outcomes.
Area of Science:
- Cardiology
- Geriatrics
- Surgical Outcomes
Background:
- Coronary artery bypass grafting (CABG) is a major surgery with significant risks.
- Assessing patient frailty preoperatively is crucial for predicting surgical outcomes.
- Traditional frailty assessments may not fully capture physiological status.
Purpose of the Study:
- To evaluate the predictive value of the frailty index calculated using laboratory data and vital signs (FI-L) in CABG patients.
- To determine the association of FI-L with mortality and postoperative complications following CABG.
- To identify an optimal FI-L cutoff for predicting adverse events post-CABG.
Main Methods:
- A cohort of 508 patients undergoing CABG between 2018-2021 was analyzed.
- The frailty index (FI-L) was computed using 32 preoperative laboratory and vital sign parameters.
- Primary endpoints included operative and medium-term all-cause mortality; secondary endpoints were postoperative complications and MACCEs.
Main Results:
- The mean FI-L was 20.9%. Early mortality was 1.6%. Common complications included atrial fibrillation (29.1%) and respiratory issues (7.5%).
- Higher FI-L was significantly associated with medium-term all-cause mortality (HR 1.042), MACCEs (sHR 1.054), atrial fibrillation (OR 1.02), acute kidney injury (OR 1.06), and re-operation for bleeding (OR 1.09).
- A 32% FI-L cutoff was identified as optimal for predicting all-cause mortality post-CABG.
Conclusions:
- The FI-L is a significant prognostic factor in patients undergoing CABG.
- FI-L effectively predicts medium-term all-cause mortality and various postoperative complications.
- This index offers a valuable tool for risk stratification in CABG patients.
Background:
This study investigated the predictive value of the frailty index calculated using laboratory data and vital signs (FI-L) in patients who underwent coronary artery bypass grafting (CABG).
Methods:
This study included 508 patients (age 67.3±9.7 years, male 78.0%) who underwent CABG between 2018 and 2021. The FI-L, which estimates patients' frailty based on laboratory data and vital signs, was calculated as the ratio of variables outside the normal range for 32 preoperative parameters. The primary endpoints were operative and medium-term all-cause mortality. The secondary endpoints were early postoperative complications and major adverse cardiac and cerebrovascular events (MACCEs).
Results:
The mean FI-L was 20.9%±10.9%. The early mortality rate was 1.6% (n=8). Postoperative complications were atrial fibrillation (n=148, 29.1%), respiratory complications (n=38, 7.5%), and acute kidney injury (n=15, 3.0%). The 1- and 3-year survival rates were 96.0% and 88.7%, and the 1- and 3-year cumulative incidence rates of MACCEs were 4.87% and 8.98%. In multivariable analyses, the FI-L showed statistically significant associations with medium-term all-cause mortality (hazard ratio [HR], 1.042; 95% confidence interval [CI], 1.010-1.076), MACCEs (subdistribution HR, 1.054; 95% CI, 1.030-1.078), atrial fibrillation (odds ratio [OR], 1.02; 95% CI, 1.002-1.039), acute kidney injury (OR, 1.06; 95% CI, 1.014-1.108), and re-operation for bleeding (OR, 1.09; 95% CI, 1.032-1.152). The minimal p-value approach showed that 32% was the best cutoff for the FI-L as a predictor of all-cause mortality post-CABG.
Conclusion:
The FI-L was a significant prognostic factor related to all-cause mortality and postoperative complications in patients who underwent CABG.
More Related Videos
 05:53
Measuring Frailty in HIV-infected Individuals. Identification of Frail Patients is the First Step to Amelioration and Reversal of Frailty
Published on: July 24, 2013
 05:16
Cutoff Value of Phase Angle by Bioelectrical Impedance Analysis at Admission as a Prognostic Factor in Patients with Acute Heart Failure
Published on: June 10, 2025
Related Concept Videos
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:26
Heart Failure III: Clinical Manifestations
 01:30
Coronary Artery Disease I: Introduction
 01:26
Coronary Artery Disease II: Pathophysiology
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations