The performance of HEAR score for identification of low-risk chest pain: a systematic review and meta-analysis
Related Experiment Video
Updated: Sep 26, 2025

Signal Acquisition, Score Interpretation, and Economics of a Non-Invasive Point-of-Care Test for Coronary Artery Disease
Published on: August 9, 2024
Mahsan Khaleghi Rad1, Mohammad Mahdi Pirmoradi1, Amin Doosti-Irani2
1Department of Emergency Medicine, Tehran University of Medical Sciences, Tehran.

Insights
The HEAR score, excluding troponin, can safely identify low-risk chest pain patients in the emergency department (ED) for early discharge. However, it is not recommended for prehospital use.
Area of Science:
- Emergency Medicine
- Cardiology
- Diagnostic Accuracy
Background:
- Chest pain is a frequent emergency department (ED) presentation.
- The HEART score aids in risk stratification for acute chest pain.
- The HEAR score (History, ECG, Age, Risk Factors) is a troponin-inclusive HEART score variant.
Purpose of the Study:
- To systematically review and meta-analyze the HEAR score's performance in hospital and prehospital settings.
- To assess the HEAR score's utility for risk stratification in acute chest pain patients.
- To evaluate the HEAR score's potential for reducing unnecessary testing and length of stay.
Main Methods:
- Systematic review and meta-analysis of English studies on the HEAR score in acute chest pain.
- Searched MEDLINE, Embase, and other databases from 1946 to July 2021.
- Assessed study quality using QUADAS-2; pooled data using inverse variance and random-effects models.
Main Results:
- Included 10 studies with 33,843 patients; studies had low to moderate risk of bias.
- In the ED, HEAR score <2 cutoff showed 99.03% sensitivity and 99.84% NPV for major adverse cardiac events.
- Prehospital HEAR score <4 cutoff had 85.01% sensitivity and 91.48% NPV.
Conclusions:
- The HEAR score <2 is suitable for early discharge strategies in the ED setting.
- The HEAR score is not currently recommended for use in the prehospital setting.
- Further research may refine HEAR score application in diverse clinical environments.
Abstract:
Chest pain is one of the most common presentations to the emergency department (ED) and HEART score (history, ECG, age, risk factors, and cardiac troponin) is recommended for risk stratification. It has been proposed that the sum of four items with no troponin (HEAR score) below 2 can be used safely to lower testing and reduce length of stay. To assess the performance of the HEAR score in hospital and prehospital settings, we performed a systematic review and meta-analysis. English studies on the performance of the HEAR score in patients with acute chest pain were included. They were excluded if data are inaccessible. MEDLINE, Embase, Evidence-Based Medicine Reviews, Scopus, and web of science were searched from 1946 to July 2021. The quality of studies was assessed using Quality Assessment of Diagnostic Accuracy Studies version 2. Acute coronary syndrome or major adverse cardiac events prediction were outcomes of interest. The performance indices with 95% confidence intervals (CIs) were extracted. Inverse variance and the random-effects model were used to report the results. Of the 692 articles on the HEAR score, 10 studies were included in the analysis with 33 843 patients. Studies were at low to moderate risk of bias. Three studies were in prehospital and three were retrospective. The pooling of data on the HEAR score showed that the sensitivity at the HEAR<2, <3, and <4 cutoffs in the ED were 99.03% (95% CI, 98.29-99.77), 97.54% (95% CI, 94.50-100), and 91.80% (95% CI, 84.62-98.98), respectively. The negative predictive values (NPVs) for the above cutoffs were 99.84% (95% CI, 99.72-99.95), 99.75% (95% CI, 99.65-99.85), and 99.57% (95% CI, 99.11-100), respectively. Of note, for the HEAR<2, negative likelihood ratio was 0.07 (95% CI, 0.02-0.12). In the prehospital, at the HEAR<4 cutoff, the pooled sensitivity and NPV were 85.01% (95% CI, 80.56-89.47) and 91.48% (95% CI, 87.10-95.87), respectively. This study showed that in the ED, the HEAR score<2 can be used for an early discharge strategy. Currently, this score cannot be recommended in prehospital setting. Prospero (CRD42021273710).
More Related Videos
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
 04:40
Identifying Coronary Artery Calcification on Non-gated Computed Tomography Scans
Published on: August 28, 2018
Related Concept Videos
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:29
Angina III: Clinical Manifestations and Assessment
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:26
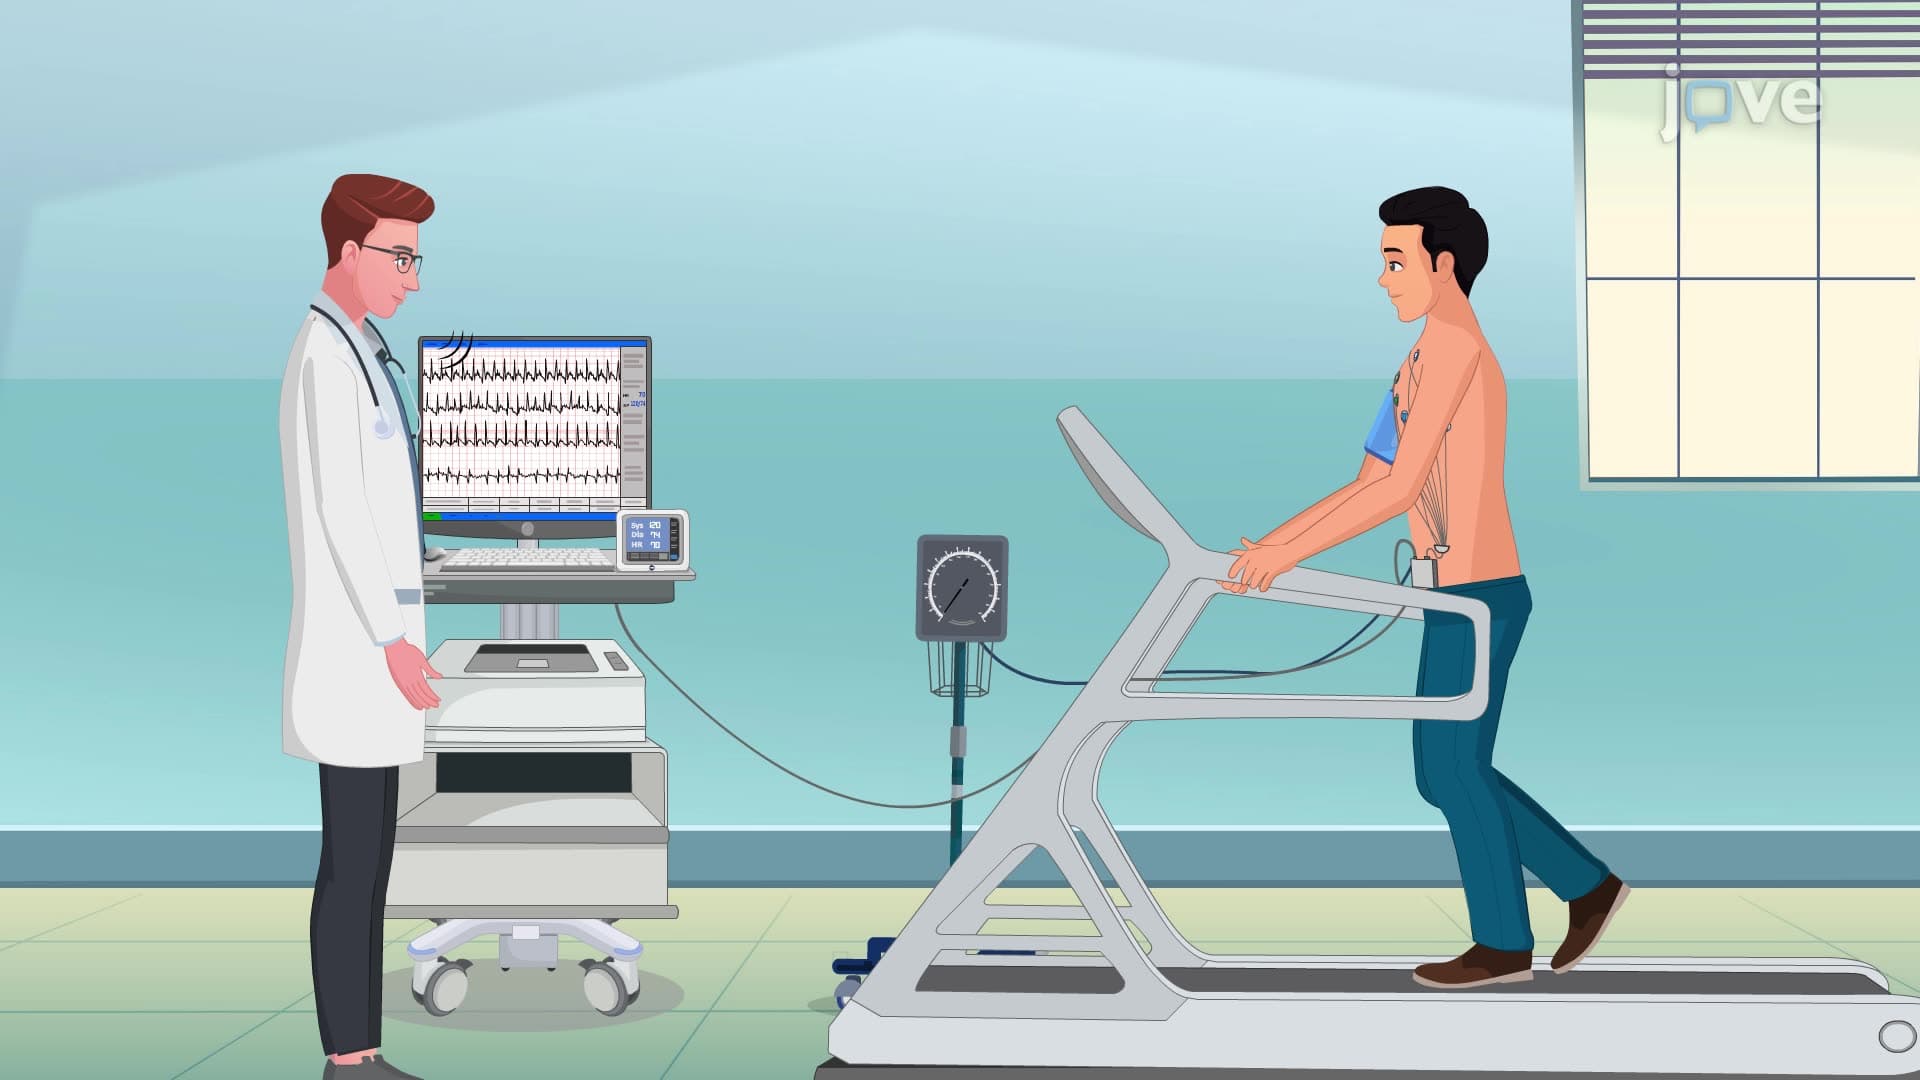
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:17
Imaging Studies for Cardiovascular System I:Echocardiography
Indications: Echocardiography is utilized to diagnose heart failure, valve disorders, and myocardial infarction. It also assesses cardiac structures' size, shape, and motion,...
 01:23
Assessment of the Cardiovascular System I: Subjective Data
Initial Enquiry
Ask the patient about their primary concern and thoroughly explore all reported symptoms.
Medical History
Investigate past illnesses affecting the cardiovascular system, such as angina, anemia, rheumatic fever, congenital heart disease, stroke, thrombophlebitis, dysrhythmias, varicosities
Inquire about symptoms...