Related Experiment Video
Updated: Sep 26, 2025
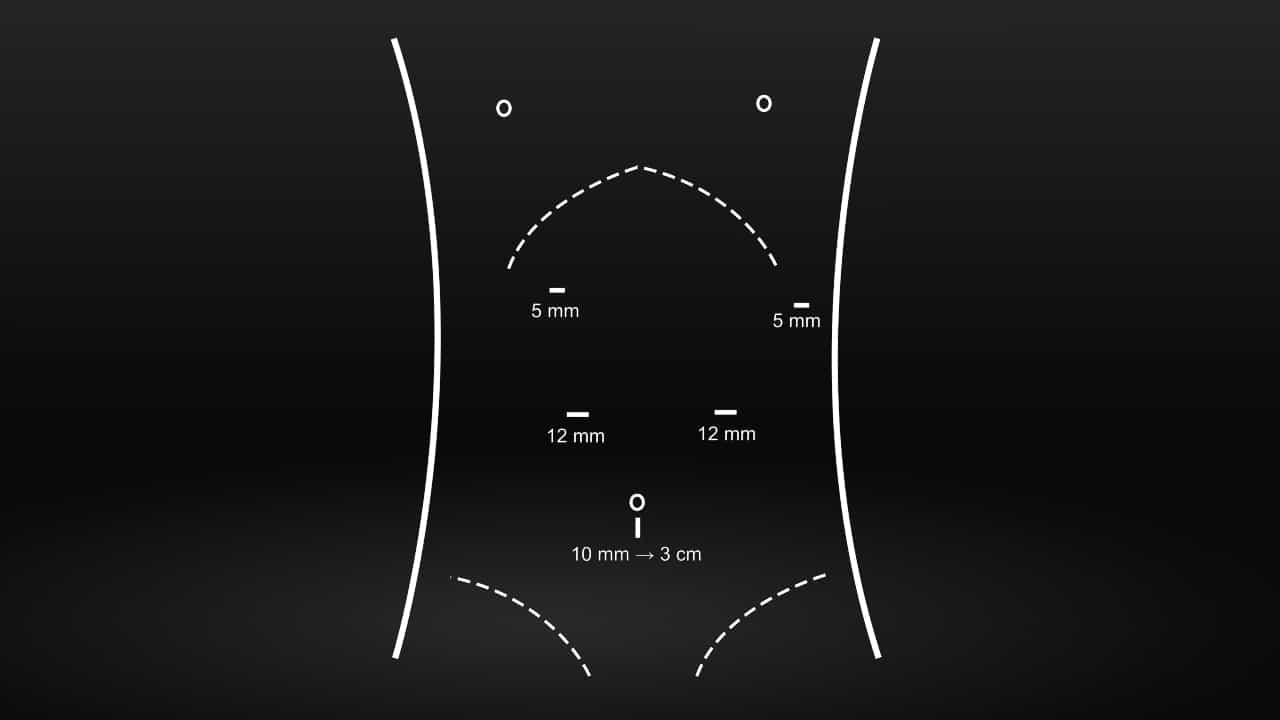

Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Pathophysiology and management of bleeding and thrombosis in patients with liver disease
Bente P van den Boom1, Ton Lisman1
1Surgical Research Laboratory and Section of Hepatobiliary Surgery and Liver Transplantation, Department of Surgery, University of Groningen, University Medical Center Groningen, Groningen, the Netherlands.

Patients with liver disease often develop complex changes in their haemostatic system. Frequently observed changes include thrombocytopaenia and altered plasma levels of most of the proteins involved in haemostasis. Although liver disease was historically classified as a haemostasis-related bleeding disorder, it has now been well established that the antihaemostatic changes that promote bleeding are compensated for by prohaemostatic changes. Conventional coagulation tests however do not accurately reflect these prohaemostatic changes, resulting in an underestimation of haemostatic potential. Novel coagulation tests, such as viscoelastic tests (VETs) and thrombin generation assays (TGAs) better reflect the net result of the haemostatic changes in patients with liver disease, and demonstrate a new, "rebalanced" haemostatic status. Although rebalanced, this haemostatic status is more fragile than in patients without liver disease. Patients with liver disease are therefore not only at risk of bleeding but also at risk of thrombosis. Notably, however, many haemostatic complications in liver disease are not related to the haemostatic failure. It is, therefore, crucial to identify the cause of the bleed or thrombotic complication in order to provide adequate treatment. In this paper, we will elaborate on the haemostatic changes that occur in liver disease, reflect on laboratory and clinical studies over the last few years, and explore the pathophysiologies of bleeding and thrombosis in this specific patient group.
Patients with liver disease often develop complex changes in their haemostatic system. Frequently observed changes include thrombocytopaenia and altered plasma levels of most of the proteins involved in haemostasis. Although liver disease was historically classified as a haemostasis-related bleeding disorder, it has now been well established that the antihaemostatic changes that promote bleeding are compensated for by prohaemostatic changes. Conventional coagulation tests however do not accurately reflect these prohaemostatic changes, resulting in an underestimation of haemostatic potential. Novel coagulation tests, such as viscoelastic tests (VETs) and thrombin generation assays (TGAs) better reflect the net result of the haemostatic changes in patients with liver disease, and demonstrate a new, "rebalanced" haemostatic status. Although rebalanced, this haemostatic status is more fragile than in patients without liver disease. Patients with liver disease are therefore not only at risk of bleeding but also at risk of thrombosis. Notably, however, many haemostatic complications in liver disease are not related to the haemostatic failure. It is, therefore, crucial to identify the cause of the bleed or thrombotic complication in order to provide adequate treatment. In this paper, we will elaborate on the haemostatic changes that occur in liver disease, reflect on laboratory and clinical studies over the last few years, and explore the pathophysiologies of bleeding and thrombosis in this specific patient group.

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:30
Venous Thrombosis IV: Nursing Management
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:29
Venous Thrombosis III: Interprofessional Care
 01:24
Esophageal Varices-I: Introduction