Related Experiment Video
Updated: Sep 26, 2025


A Large Animal Model for Acute Kidney Injury by Temporary Bilateral Renal Artery Occlusion
Published on: February 2, 2021
Optimization of levetiracetam dosing regimen in critically ill patients with augmented renal clearance: a Monte Carlo
Idoia Bilbao-Meseguer1,2, Helena Barrasa3,4, Alicia Rodríguez-Gascón1,5
1Pharmacokinetic, Nanotechnology and Gene Therapy Group (PharmaNanoGene), Faculty of Pharmacy, Centro de Investigación Lascaray Ikergunea, University of the Basque Country UPV/EHU, Paseo de la Universidad 7, 01006, Vitoria-Gasteiz, Spain.

Background:
Levetiracetam pharmacokinetics is extensively altered in critically ill patients with augmented renal clearance (ARC). Consequently, the dosage regimens commonly used in clinical practice may not be sufficient to achieve target plasma concentrations. The aim of this study is to propose alternative dosage regimens able to achieve target concentrations in this population. Furthermore, the feasibility of the proposed dosing regimens will be discussed from a clinical point of view.
Methods:
Different dosage regimens for levetiracetam were evaluated in critically ill patients with ARC. Monte Carlo simulations were conducted with extended or continuous infusions and/or high drug doses using a previously developed population pharmacokinetic model. To assess the clinical feasibility of the proposed dosages, we carried out a literature search to evaluate the information on toxicity and efficacy of continuous administration or high doses, as well as the post-dilution stability of levetiracetam.
Results:
According to the simulations, target concentrations in patients with CrCl of 160 or 200 mL/min can be achieved with the 3000 mg daily dose by prolonging the infusion time of levetiracetam. For patients with CrCl of 240 mL/min, it would be necessary to administer doses higher than the maximum recommended. Available evidence suggests that levetiracetam administration in continuous infusion or at higher doses than those approved seems to be safe. It would be desirable to re-examinate the current recommendations about drug stability and to achieve a consensus in this issue.
Conclusions:
Conventional dosage regimens of levetiracetam (500-1500 mg twice daily in a short infusion) do not allow obtaining drug plasma concentrations among the defined target in critically ill patients with ARC. Therefore, new dosing guidelines with specific recommendations for patients in this subpopulation are needed. This study proposes new dosages for levetiracetam, including extended (4 or 6 h) infusions, continuous infusions or the administration of doses higher than the recommended in the summary of product characteristics (> 3000 mg). These new dosage recommendations take into account biopharmaceutical and pharmacokinetic aspects and meet feasibility criteria, which allow them to be transferred to the clinical environment with safety and efficacy. Nevertheless, further clinical studies are needed to confirm these results.
More Related Videos
 06:14
Optimized LC-MS/MS Method for the High-throughput Analysis of Clinical Samples of Ivacaftor, Its Major Metabolites, and Lumacaftor in Biological Fluids of Cystic Fibrosis Patients
Published on: October 15, 2017
 05:33
A Model for Epilepsy of Infectious Etiology using Theiler's Murine Encephalomyelitis Virus
Published on: June 23, 2022
Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:08
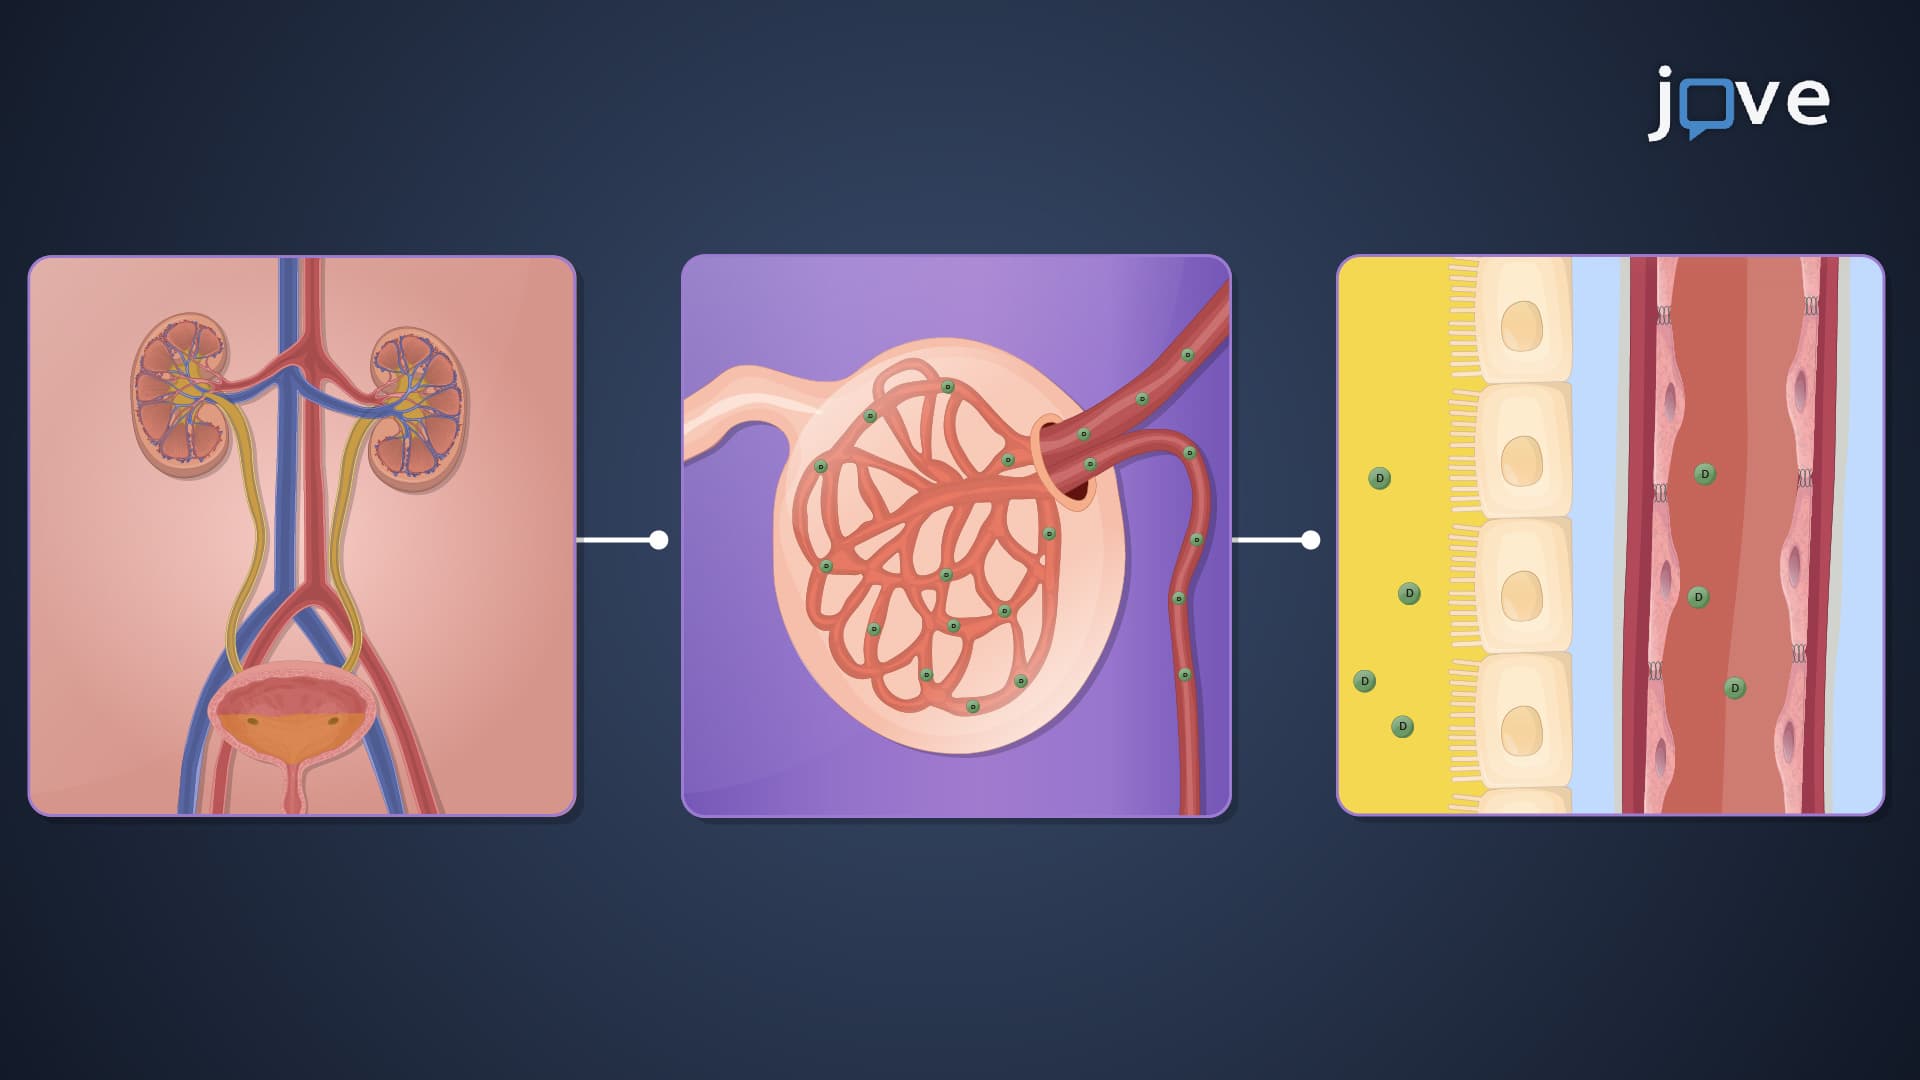
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...
 00:56
One-Compartment Open Model for IV Bolus Administration: Estimation of Clearance
In the one-compartment open model for intravenous (IV) bolus administration, clearance is estimated by dividing the elimination rate by the plasma drug concentration. This equation leverages the elimination rate constant and the apparent...
 01:06
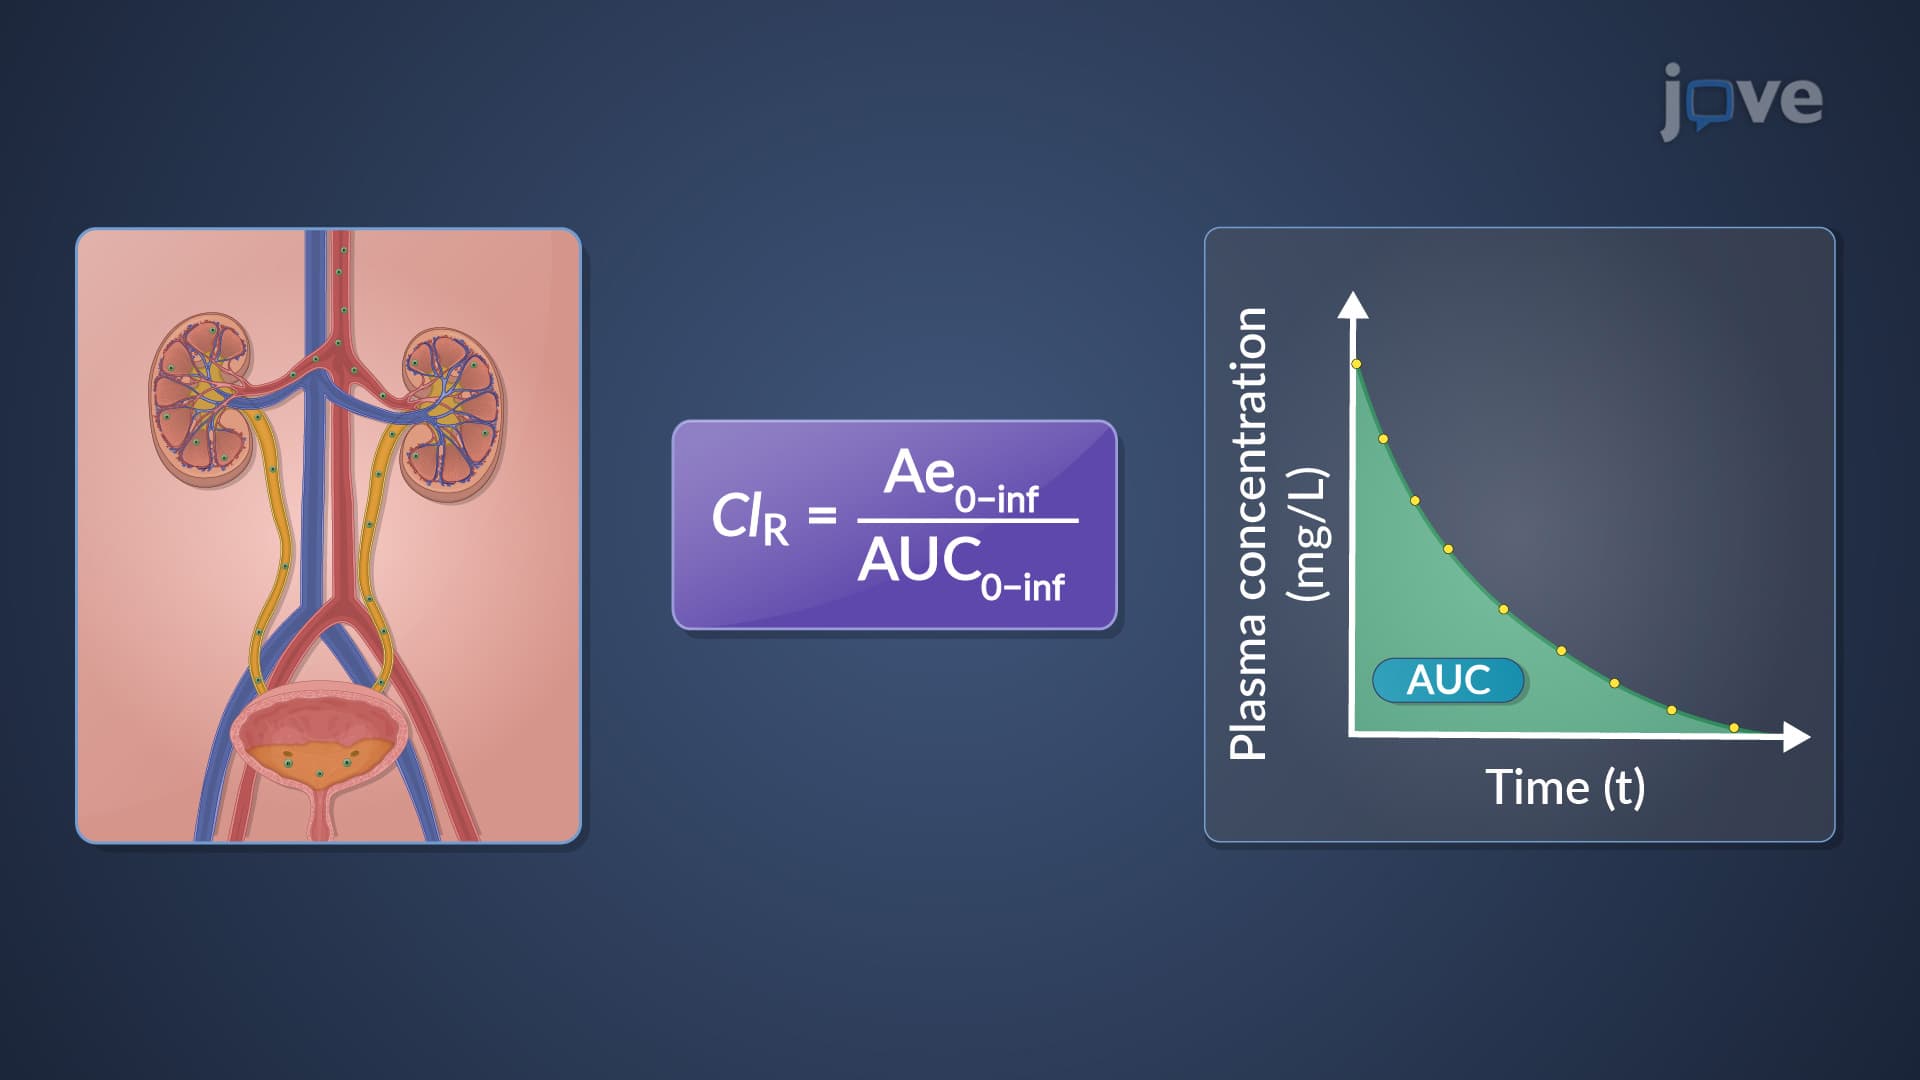
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:15
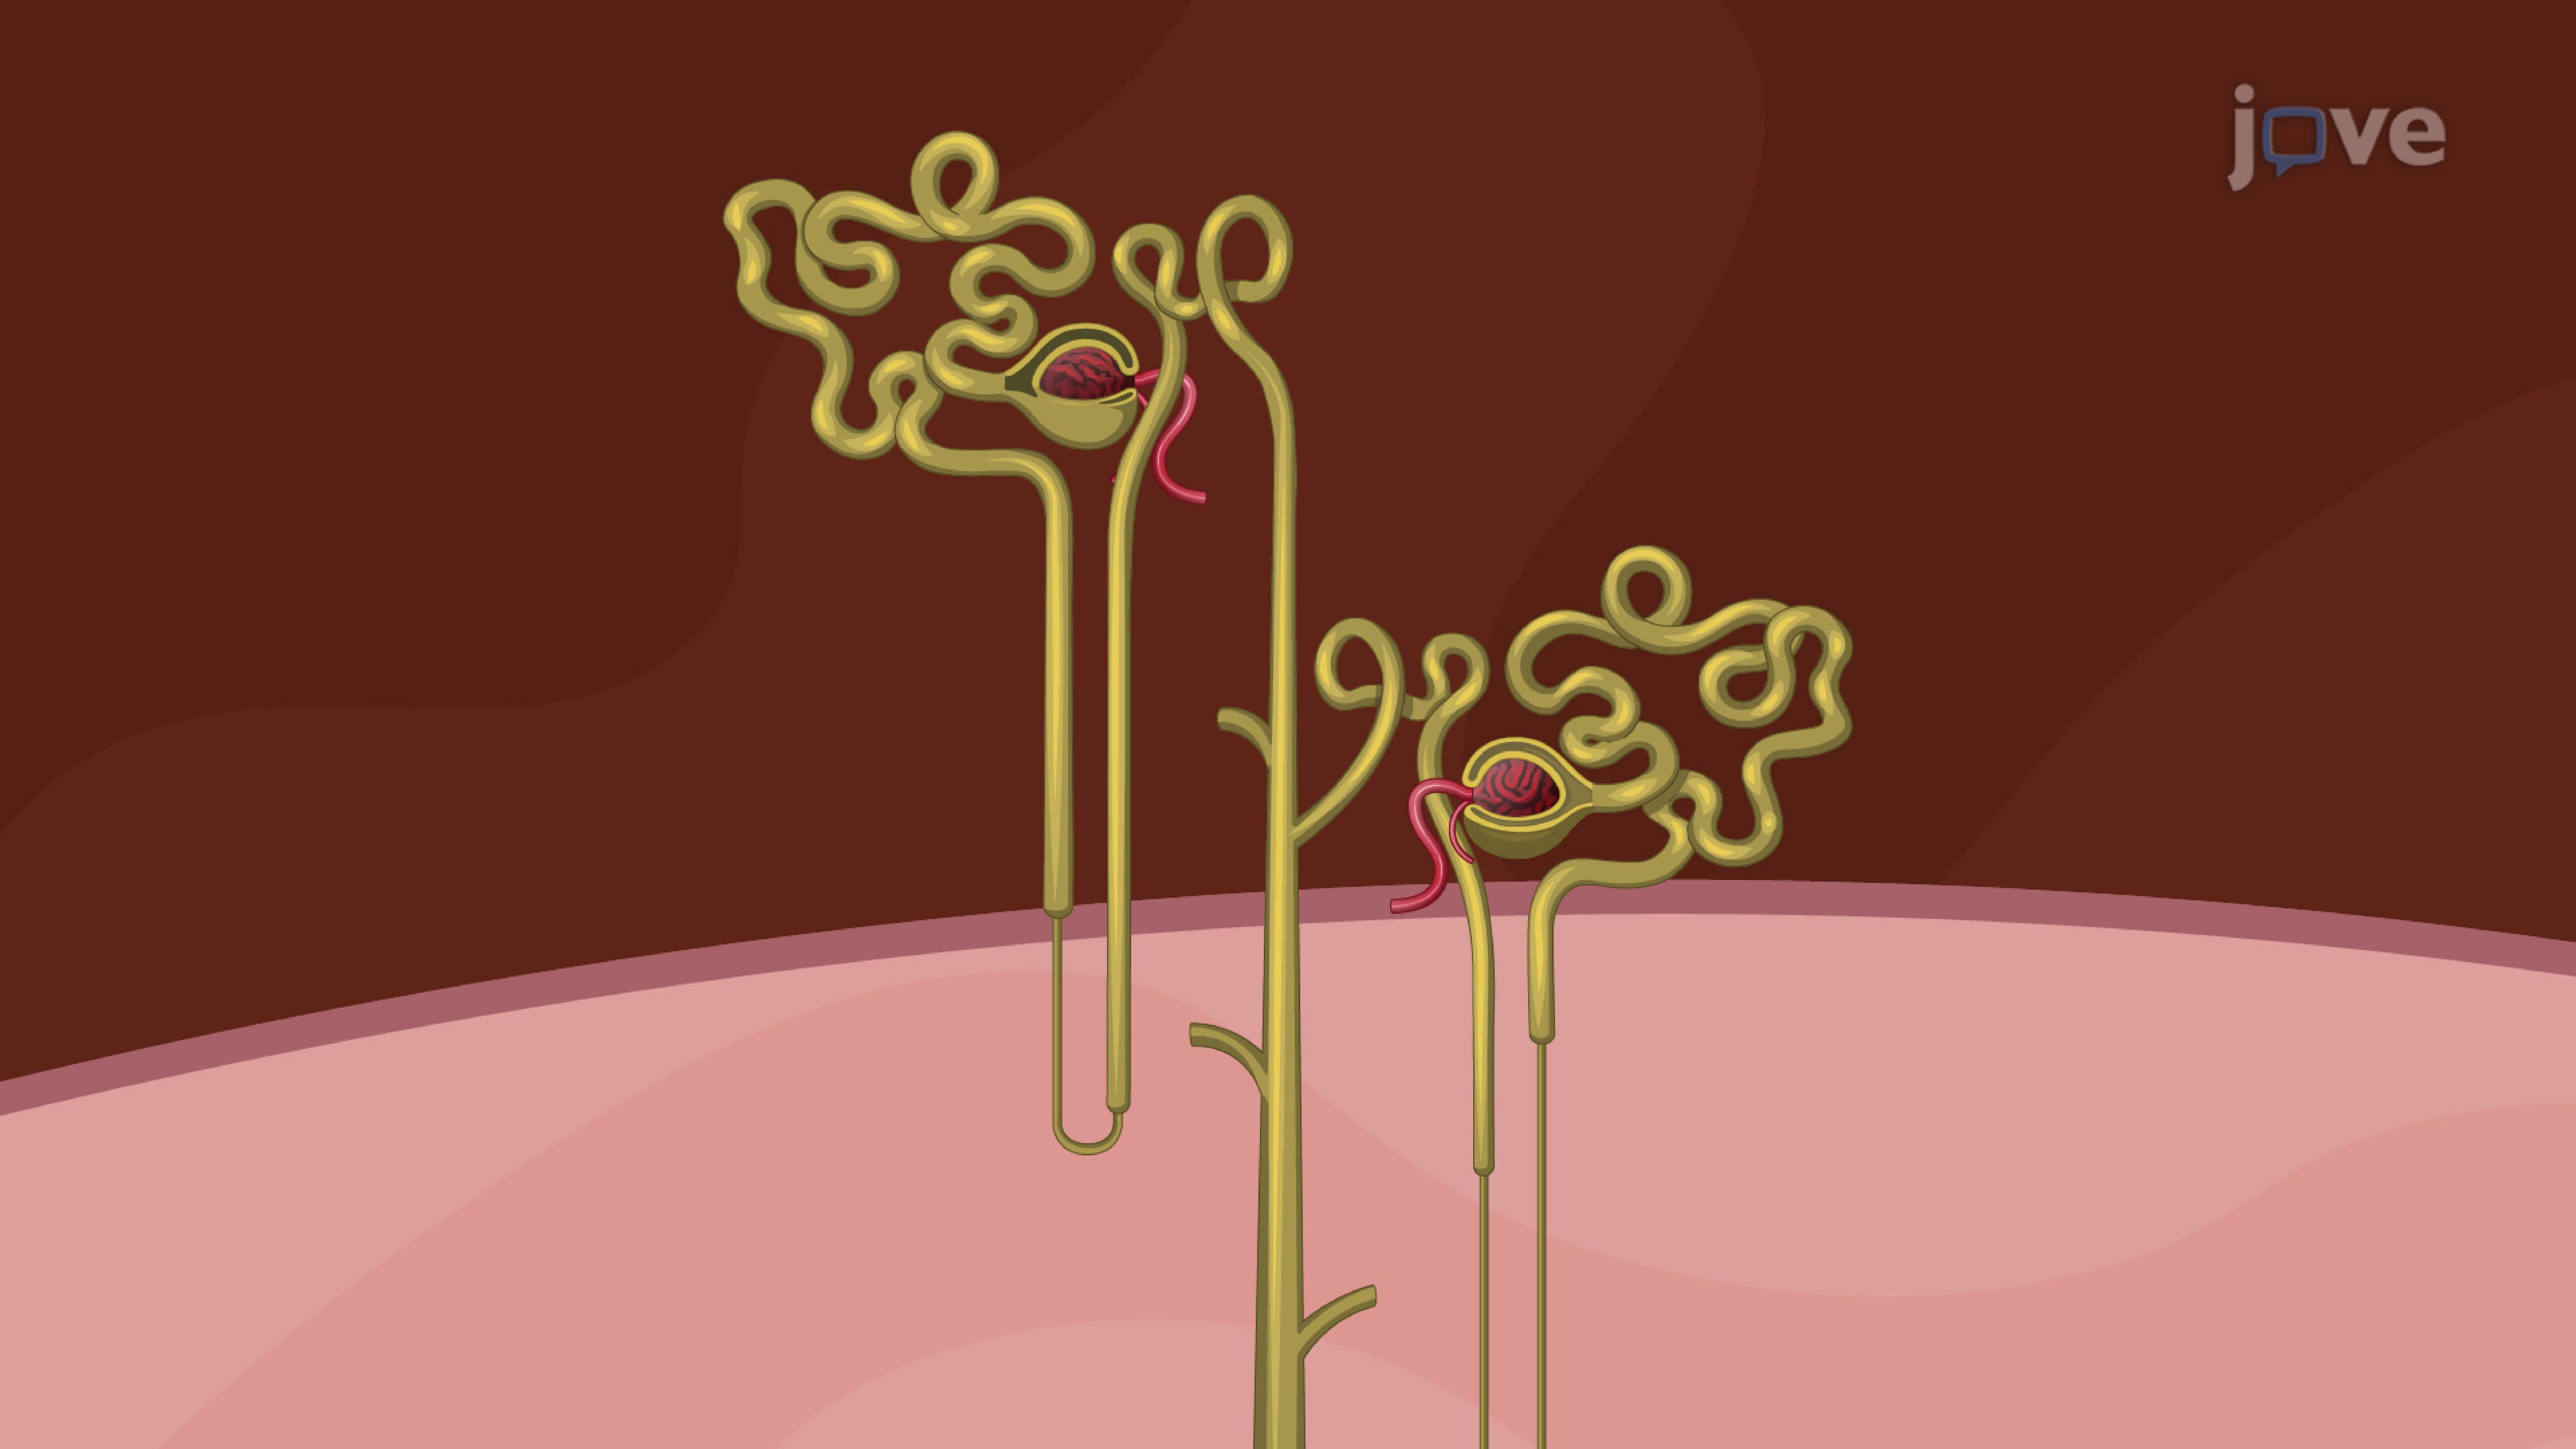
Renal Drug Excretion: Overview
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
 01:07
Determination of Renal Drug Clearance: Graphical and Midpoint Methods
The graphical method involves plotting the rate of drug excretion in urine against the plasma drug concentration. By analyzing the graph, the clearance can be calculated and obtained. Drugs rapidly excreted by the kidneys exhibit a...