Related Experiment Video
Updated: Sep 26, 2025


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Three Column Cervical Fracture-Dislocation in a 3-Year-Old Boy
Sananthan Sivakanthan1, Abdullah Feroze1, Jessica Eaton1
1Department of Neurological Surgery, University of Washington, Seattle, USA.

Insights
Severe pediatric cervical spinal cord transection is rare. This case highlights successful surgical management with halo vest and posterior fusion, leading to some upper extremity function recovery.
Area of Science:
- Pediatric neurosurgery
- Spinal cord injury research
- Traumatology
Background:
- Complete traumatic cervical fracture-dislocation with spinal cord transection is exceptionally rare in children.
- Existing literature lacks evidence-based guidelines for managing such severe pediatric spinal cord injuries.
- This case addresses a critical knowledge gap in pediatric spinal trauma management.
Observation:
- A 3-year-old child presented with a complete C6 spinal cord injury (ASIA A) due to traumatic cervical fracture-dislocation.
- The patient sustained concurrent injuries to the liver, spleen, bowel, and abdominal aorta.
- Intraoperative monitoring revealed motor evoked potential signals below the injury level, suggesting preserved neural pathways.
Findings:
- The patient underwent halo placement for reduction, followed by open reduction, internal fixation, and posterior segmental instrumented fusion.
- Postoperative follow-up showed no improvement in leg function but demonstrated recovery of upper extremity function.
- Electrographic evidence of sub-lesional function correlated with observed upper extremity motor improvements.
Implications:
- This case demonstrates the feasibility of surgical intervention for complete pediatric cervical spinal cord transection.
- Early surgical stabilization and fusion may be beneficial, even in cases with apparent complete injury.
- The findings suggest potential for neurological recovery below the clinical injury level in pediatric patients, emphasizing the importance of intraoperative neuromonitoring.
Abstract:
Complete traumatic cervical fracture-dislocation with spinal cord transection in children is a rare entity with no evidence-based guidelines on management. The authors reviewed the literature for pediatric spinal cord injury and present the case of a 3-year-old with traumatic cervical fracture-dislocation and spinal cord transection who presented as a cervical-6 complete spinal cord injury (ASIA A). His other organ systems injured included liver, spleen, bowel, and abdominal aortic injury. The patient underwent halo placement for preoperative reduction followed by open reduction and internal fixation with posterior segmental instrumented fusion. Intraoperatively, the patient had motor evoked potential signals present below the level of his injury. Early postoperative follow-up demonstrated that, although his leg function did not improve, he did demonstrate improvement in upper extremities. This is a rare case of complete cervical spinal cord transection in a pediatric patient. We elected to manage this challenging case with initial external reduction and orthosis with a halo vest followed by acute posterior cervical fusion. Despite a cervical-6 injury level on clinical exam, there was electrographic evidence of function below that level on intraoperative neuromonitoring. Postoperatively the patient has recovered some lost function.

Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:16
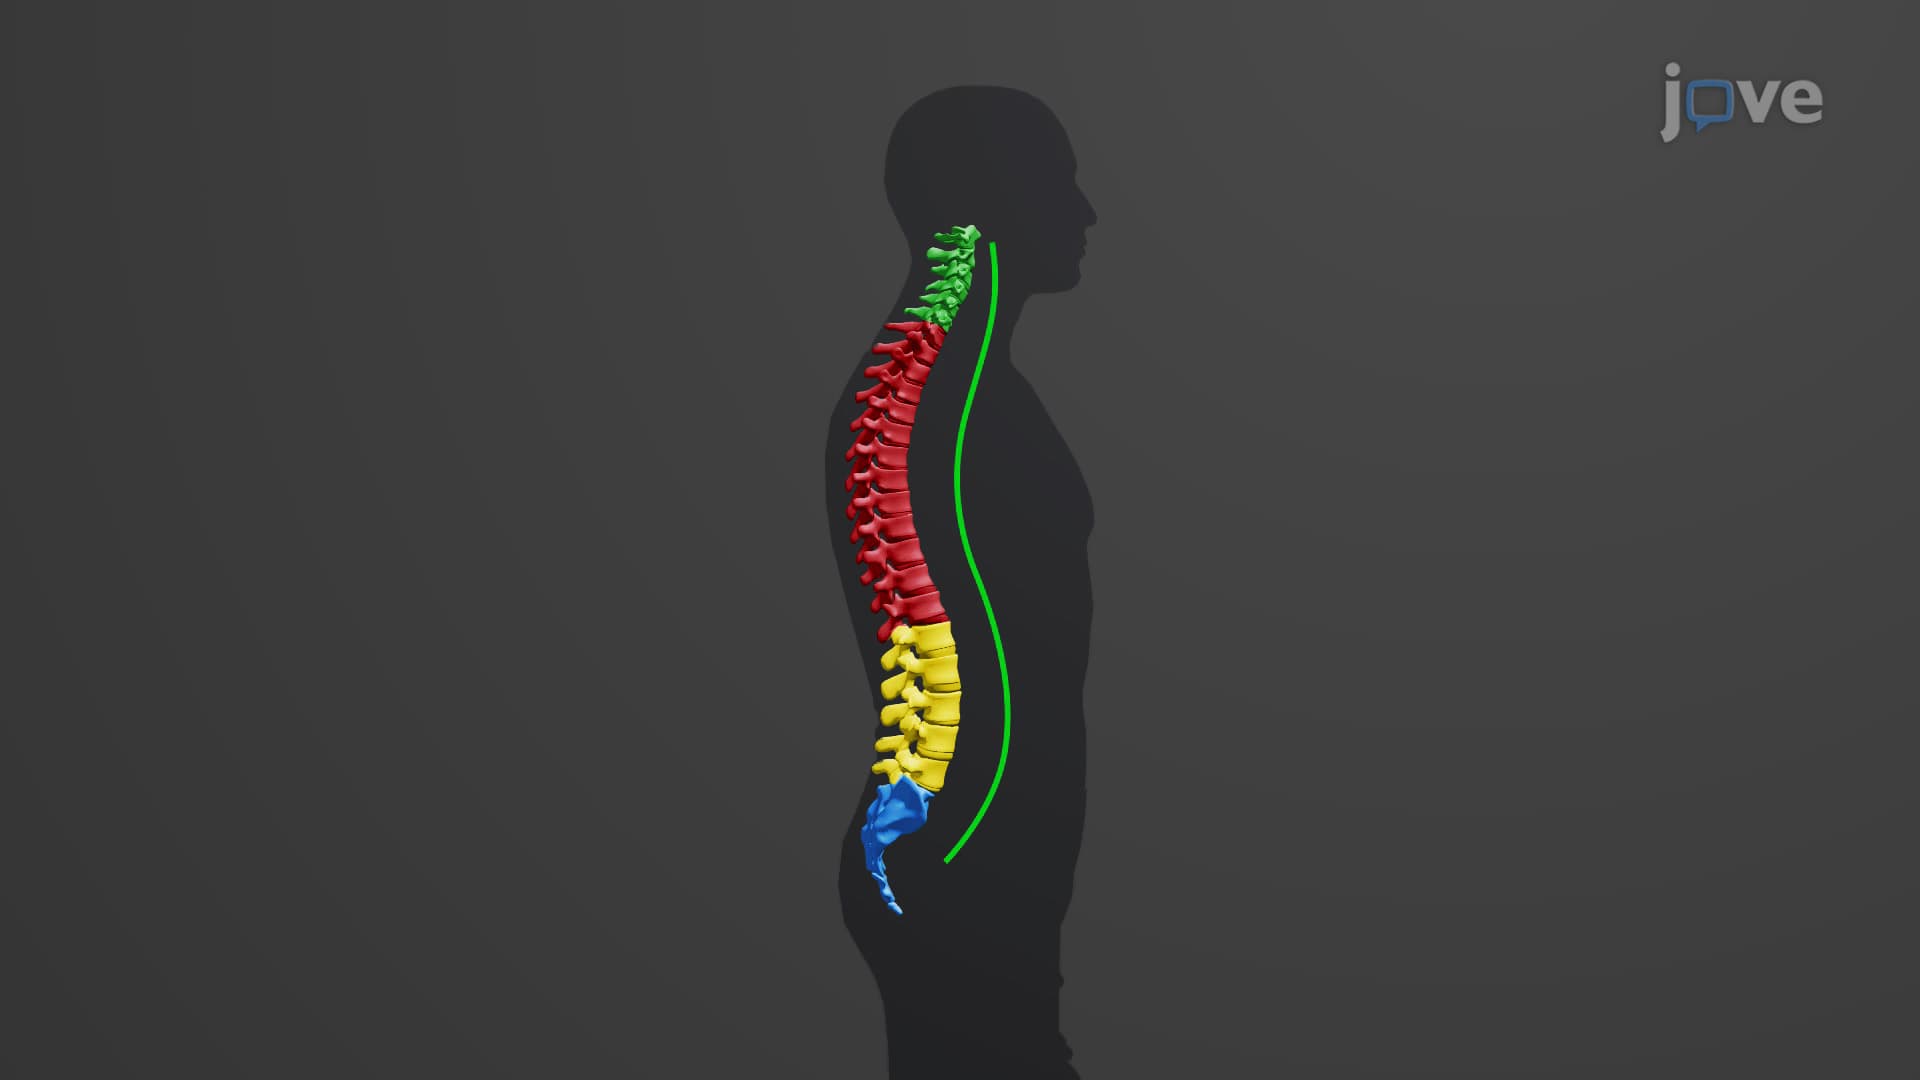
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:28
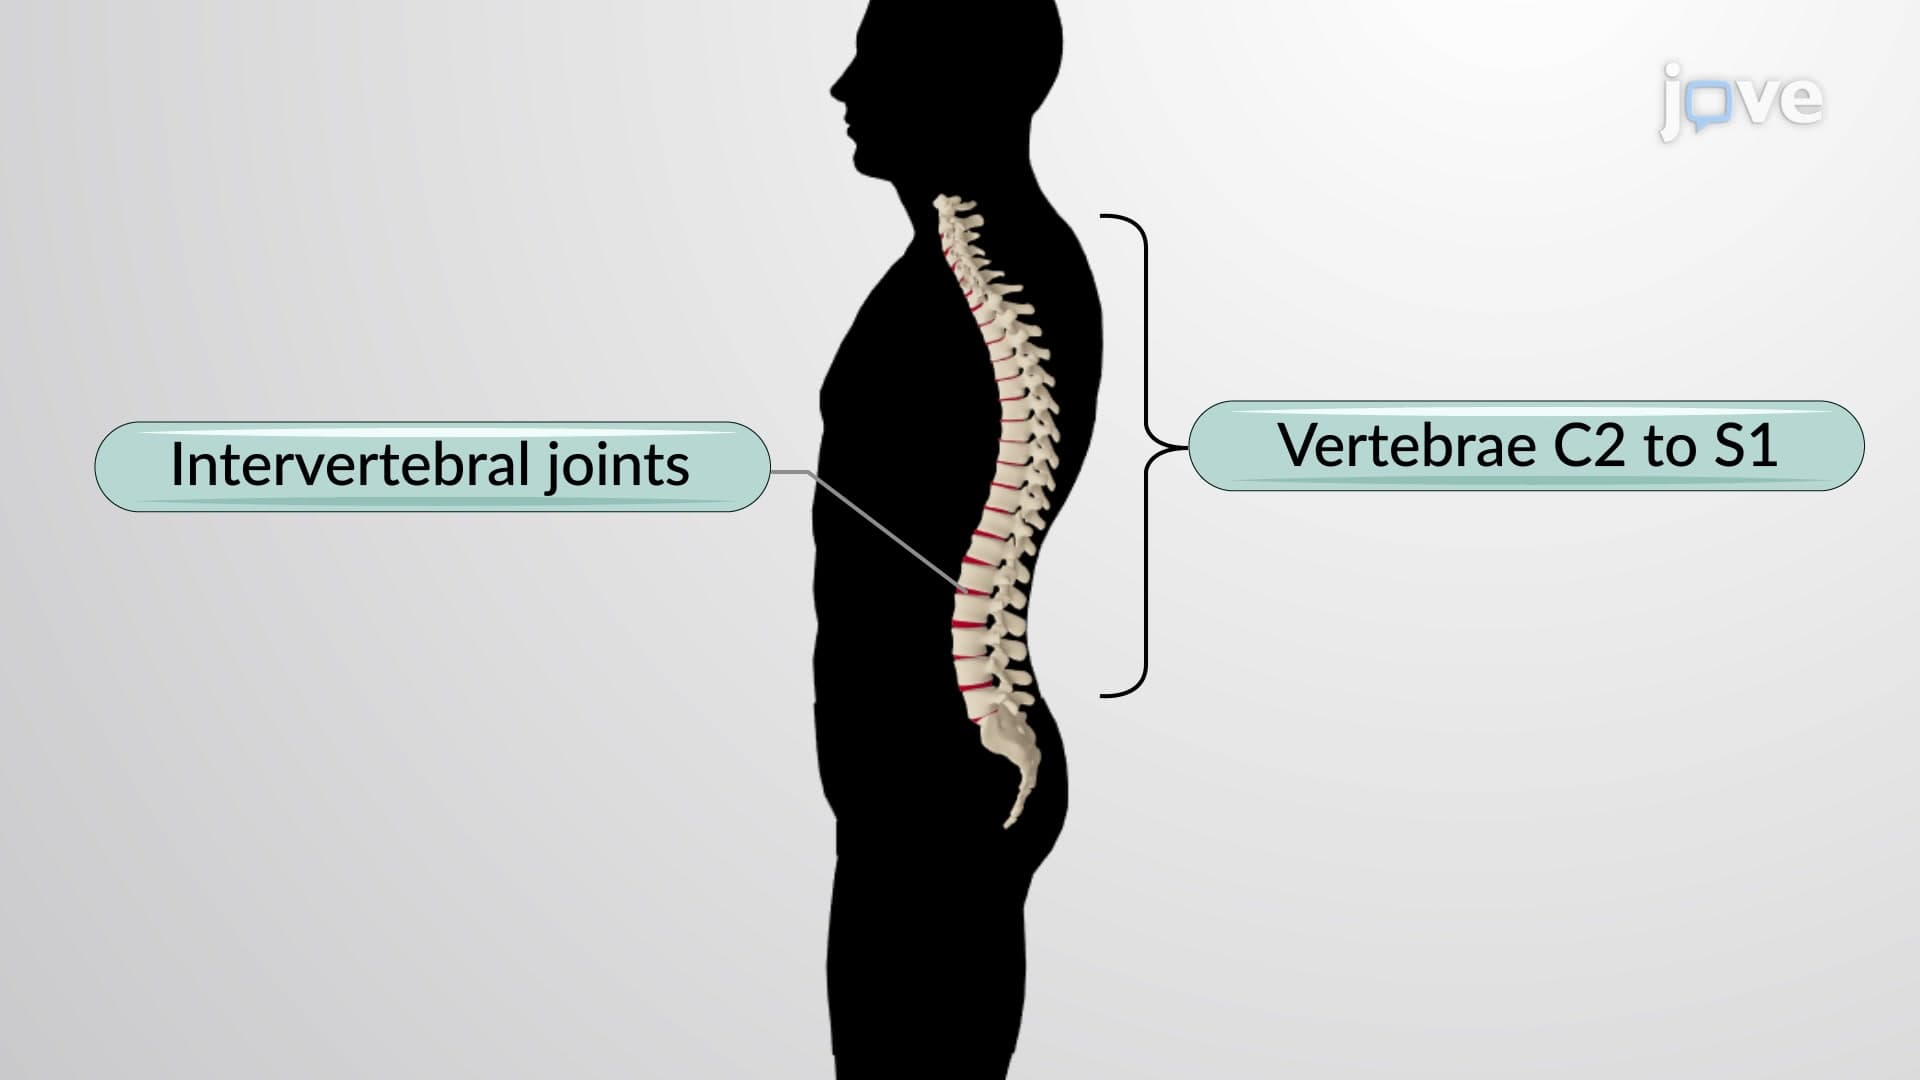
Articulations of the Vertebral Column
 01:09
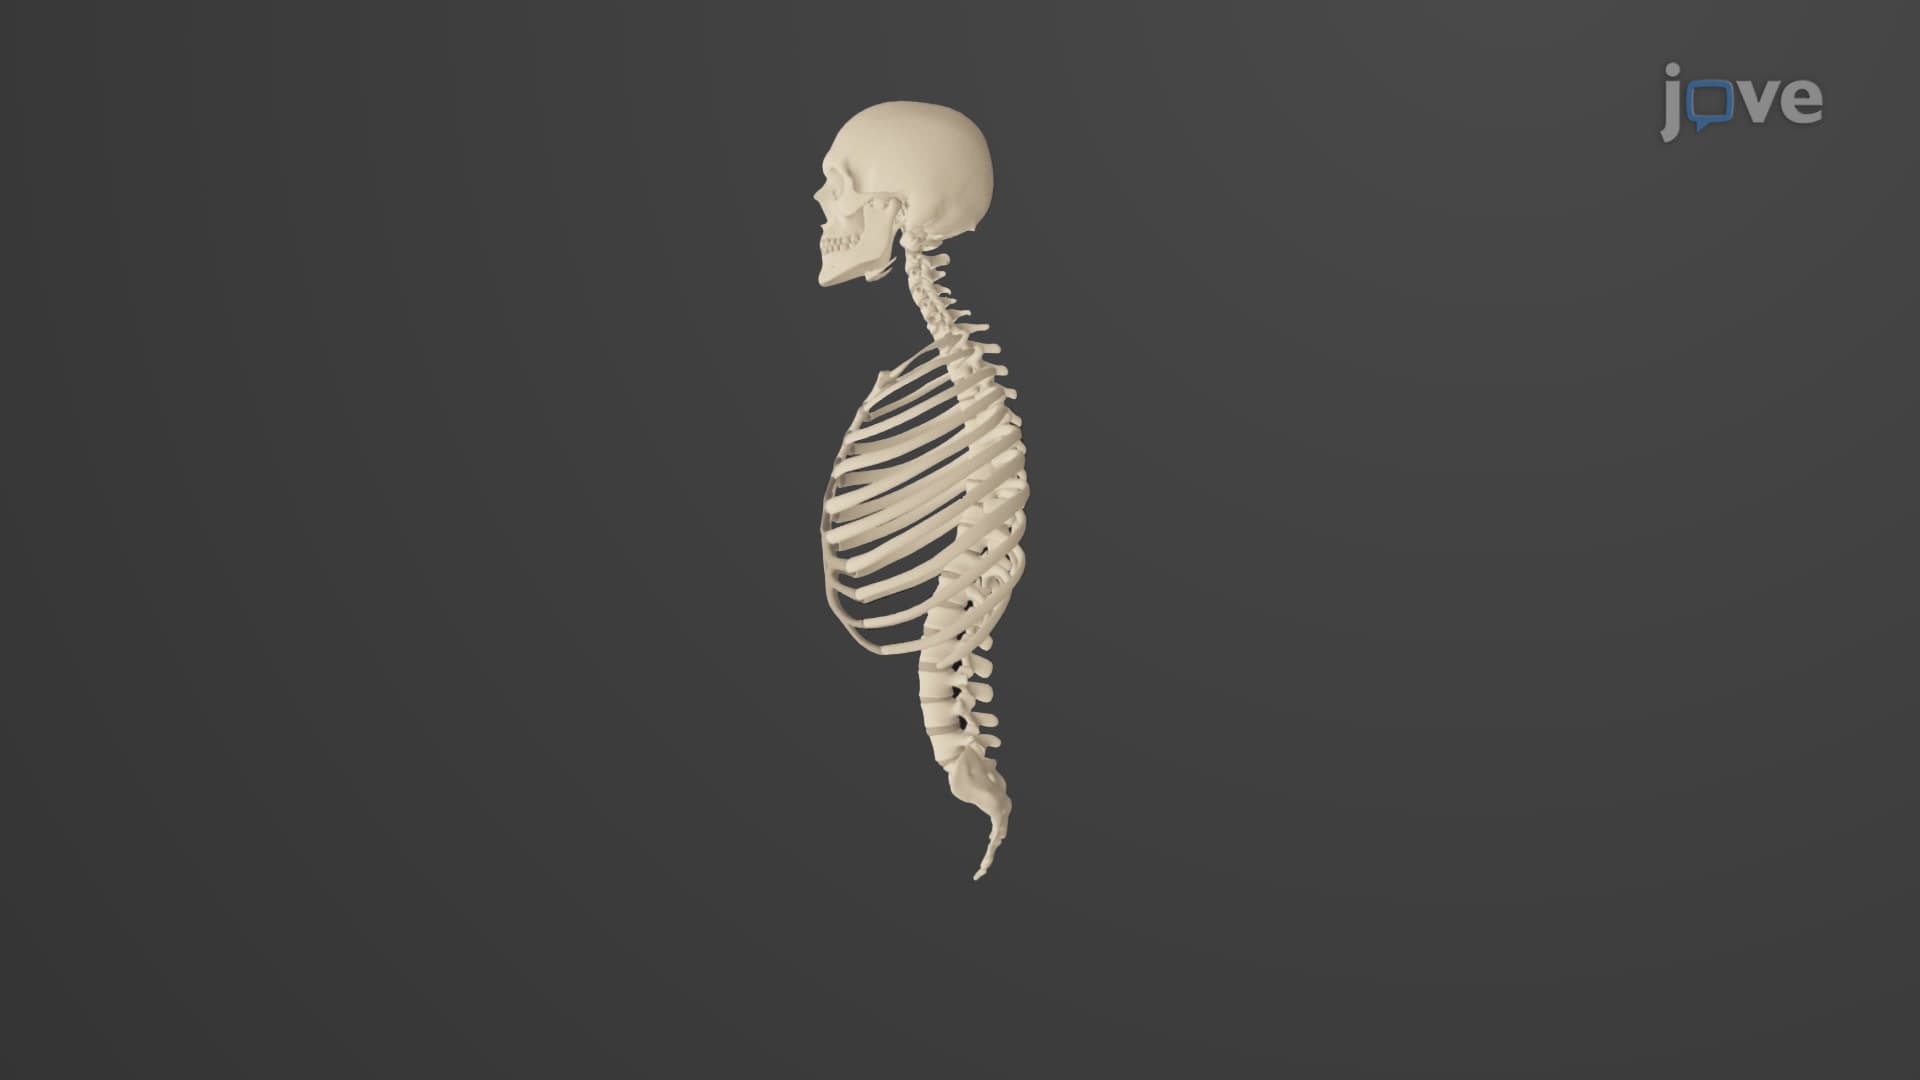
Overview of the Axial Skeleton
The axial skeleton of the...