Related Experiment Video
Updated: Sep 26, 2025
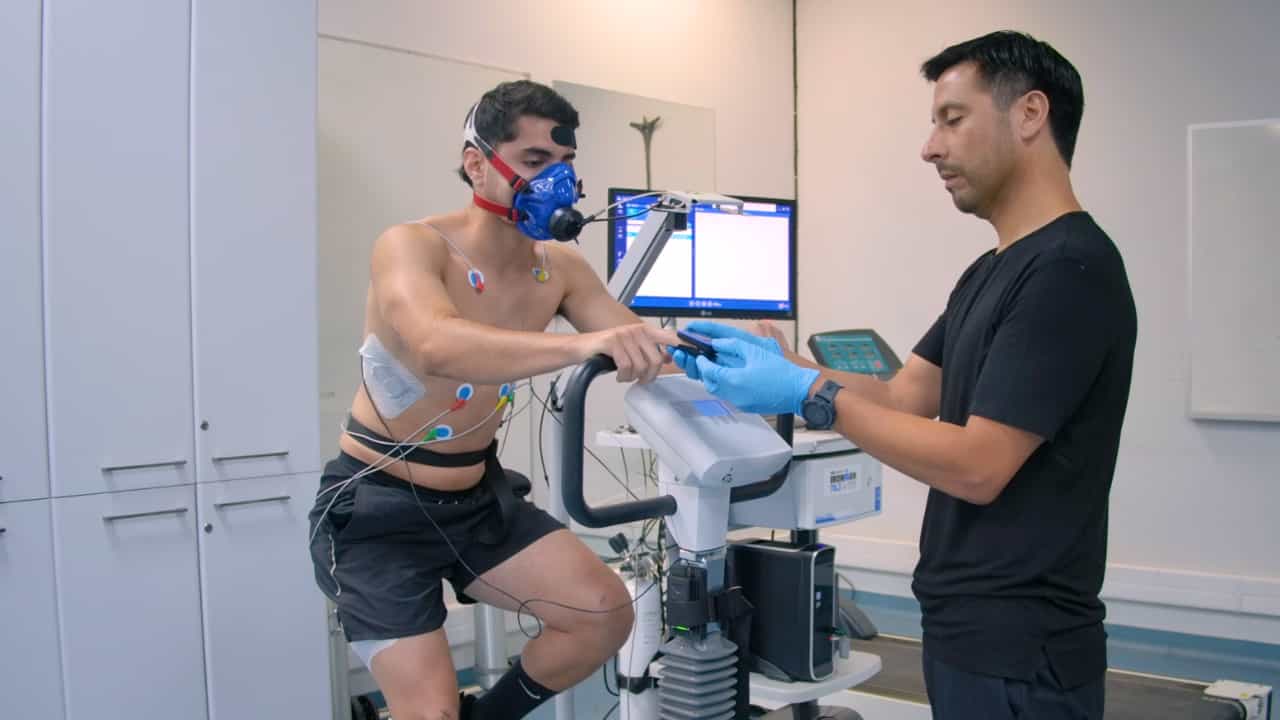

Using Near-Infrared Spectroscopy Wearable Devices to Identify Central Versus Peripheral Limitations During Exercise
Published on: December 19, 2024
Impaired ventilation during 6-min walk test in congenital central hypoventilation syndrome
Radhika N Ghosh1, Lokesh Guglani1, Adrianna L Westbrook2
1Department of Pediatrics, Division of Pediatric Pulmonology, Children's Healthcare of Atlanta, Emory University, Atlanta, Georgia, USA.

Background:
Patients with congenital central hypoventilation syndrome (CCHS) can develop hypoxemia and hypercapnia during exercise. However, there is limited literature on cardiorespiratory responses during submaximal exercise and their correlation with paired-like homeobox 2B (PHOX2B) genotype.
Objectives:
To assess oxygen saturation (SpO2 ), end-tidal carbon dioxide (ETCO2 ), heart rate (HR), and 6-min walk distance (6MWD) during a 6-min walk test (6MWT) in CCHS subjects and to correlate them with PHOX2B genotypes and assisted ventilation (AV) via tracheostomy.
Methods:
In this cross-sectional study, subjects with CCHS performed 6MWT with continuous pulse oximetry, HR, and capnography recorded before and during the 6MWT. Medical records were reviewed for PHOX2B genotype and phenotype data. Patients were categorized based on PHOX2B genotype and AV via tracheostomy.
Results:
Fifteen subjects aged 10.5 (interquartile range 7.9-16.2) years completed the 6MWT. Nine subjects used AV via tracheostomy. Seven (47%) subjects developed hypoxemia (SpO2 ≤ 90%, n = 7) and hypoventilation (ETCO2 ≥ 50 mmHg, n = 3) during the 6MWT. There was a significant decline from baseline SpO2 , increase from baseline ETCO2 , and increase in HR during the 6MWT (all p < 0.05). Subjects had decreased median percent predicted 6MWD (59.7% [50.6%-62.5%]). Nadir SpO2 (p = 0.029) and peak ETCO2 (p = 0.046) differed significantly between PHOX2B genotype groups but 6MWD did not (p = 0.8).
Conclusion:
Despite normal oxygenation and ventilation at rest and during sleep on AV, patients with CCHS can develop hypoxemia and hypercapnia during submaximal exercise. Our study highlights the importance of assessing ventilatory responses during submaximal exercise in patients with CCHS regardless of their PHOX2B genotype.
More Related Videos


Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes...
 01:25
Hyperpnea and Hyperventilation
 01:30
Acute Respiratory Failure-III
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...