Related Experiment Video
Updated: Sep 25, 2025
Author Spotlight: Enhancing Success of Ultrasound-Guided Neuraxial Anesthesia in Cases with Difficult Anatomy
Published on: January 31, 2025
Perioperative analgesic efficacy and safety of erector spinae plane block in posterior cervical spine surgery-a
Rishi M Kanna1, Karthik Ramachandran1, J Balavenkat Subramanian1
1Department of Orthopaedics and Spine Surgery, Ganga Hospital, Coimbatore, Tamil Nadu, India.

Background Content:
Posterior cervical spine surgery (PCSS) are typically open surgeries and entail significant postoperative pain. Current perioperative pain management in PCSS is reliant on multimodal analgesia. While perioperative epidural anesthetic infusion can be used in lumbar surgeries, this is not an option in the cervical spine. Pre-emptive regional analgesia through erector spinae plane block (ESPB) has shown significant perioperative analgesic benefits in lumbar spine surgeries. There are no such clinical studies in PCSS.
Purpose:
To assess the safety and efficacy of ultrasound-guided ESPB for perioperative analgesia in PCSS.
Study Design:
Prospective, randomized controlled, double-blinded study.
Patient Sample:
Eighty-six patients requiring sub-axial PCSS with or without instrumentation were randomized into two groups, those who underwent ESPB with multimodal analgesia (case) and those with only multimodal analgesia (control).
Outcome Measures:
Demographic and surgical data (blood loss, duration of surgery, perioperative total opioid consumption, muscle relaxants used) were assessed. Postoperatively, the surgical site pain, alertness scale, satisfaction score, time to mobilization and complications were recorded.
Methods:
After anesthesia and prone position, case patients received ultrasound-guided ESPB at the T1 level using 15 ml of 0.25% bupivacaine and 8 mg Dexamethasone bilaterally while the control patients received only standard postoperative multimodal analgesia.
Results:
There were 43 patients in each group; the two groups were identical in demographic and surgical profile. The intraoperative opioid consumption (119.53±40.35 vs. 308.6±189.78; p<.001) in mcg), muscle relaxant usage (50.00±0.00 mg vs. 59.53±3.75 mg, p<.001), surgical duration (124.77±26.63/ 156.74±37.01 min; p<.01) and intraoperative blood loss (310.47±130.73 ml vs. 429.77±148.50 ml; p<.05) were significantly less in the ESPB group. In the postoperative period, the control group's pain score was significantly higher (p<.001). The Modified Observer Alertness/Sedation Score (MOASS) score and satisfaction scores also showed significant differences between the case and control groups (p<.001). The mean time required to ambulate (sitting/walking) was statistically less in cases (15.81±6.15/20.72±4.02 h) when compared to controls (16.86±6.18/ 23.05±8.88 h; p<.001).
Conclusion:
In patients undergoing PCSS, ESPB is a safe and effective technique with better outcomes than standard multimodal analgesia alone, in terms of reduced intraoperative opioid requirements and blood loss, better postoperative analgesia and early mobilization.
More Related Videos

Related Concept Videos
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:29
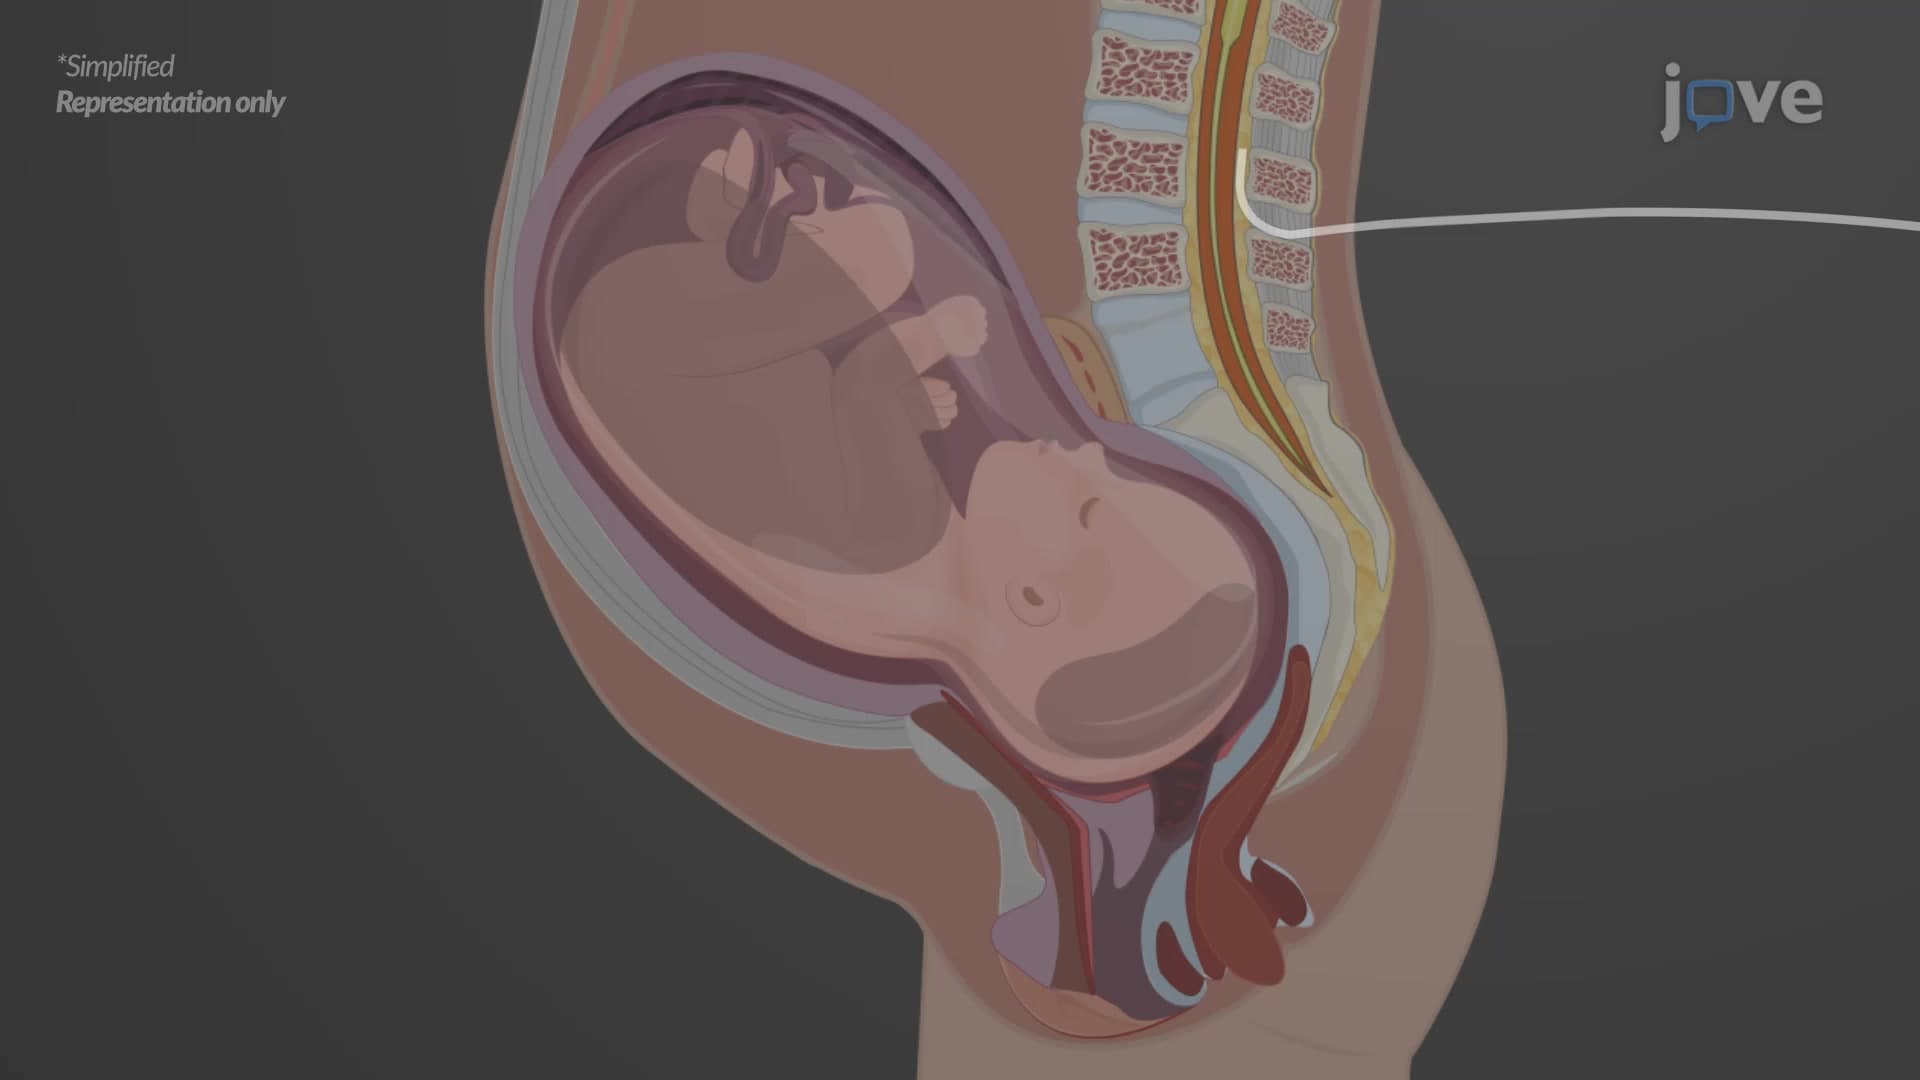
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses