Related Experiment Video
Updated: Jul 22, 2026

Technical Detail for Robot Assisted Pancreaticoduodenectomy
Published on: September 28, 2019
Robot-assisted laparoscopic augmentation ileocystoplasty and Mitrofanoff appendicovesicostomy in children:
Brittany Adamic1, Lakshmi Kirkire2, Ciro Andolfi1
1Pediatric Urology Section of Urology Department of Surgery Comer Children's Hospital The University of Chicago Pritzker School of Medicine Chicago IL USA.

Insights
Robot-assisted augmentation ileocystoplasty with Mitrofanoff appendicovesicostomy (RALIMA) offers effective urinary continence and upper tract protection for pediatric neurogenic bladder. This minimally invasive technique shows comparable outcomes to open surgery, with potential for reduced operative time.
Area of Science:
- Urology
- Minimally Invasive Surgery
- Pediatric Surgery
Background:
- Refractory neurogenic bladder in children often requires complex surgical reconstruction.
- Robot-assisted laparoscopic augmentation ileocystoplasty with Mitrofanoff appendicovesicostomy (RALIMA) aims to improve continence and protect upper urinary tracts.
- Robotic assistance may mitigate challenges associated with pure laparoscopy in these intricate procedures.
Purpose of the Study:
- To detail the techniques and modifications for robot-assisted augmentation ileocystoplasty and Mitrofanoff appendicovesicostomy in pediatric patients.
- To present updated institutional outcomes for robot-assisted augmentation ileocystoplasty (RALI) and concomitant procedures.
Main Methods:
- Retrospective review of a robotic surgical database from 2008-2017.
- Analysis of 24 pediatric patients who underwent attempted robot-assisted laparoscopic augmentation ileocystoplasty (RALI) by a single surgeon.
- Data collected included operative time, hospitalization, complications, and changes in bladder capacity using the da Vinci® surgical system.
Main Results:
- Twenty of 24 patients successfully underwent RALI, with high rates of concomitant appendicovesicostomy (80%) and antegrade continence enema channel formation (40%).
- Mean operative time was 573 minutes (most recent RALIMA: 360 minutes), with an average length of stay of 6.9 days.
- Postoperative bladder capacity increased by 244%, with 30-day complication rates of 35% (Clavian grades I-IIIb). Long-term follow-up showed incidences of bladder/upper tract stones and bladder rupture, with no need for re-augmentation.
Conclusions:
- Robot-assisted laparoscopic augmentation ileocystoplasty (RALI) demonstrates functional outcomes and complication profiles comparable to open augmentation ileocystoplasty.
- RALI offers benefits of minimally invasive surgery, including improved pain control and shorter hospital stays.
- Modifications are discussed to address and reduce operative time, a key consideration for the robotic approach.
Objective:
To describe the step-by-step techniques and modifications for robot-assisted augmentation ileocystoplasty and Mitrofanoff appendicovesicostomy in a pediatric population with updated institutional results.
Introduction:
Robot-assisted laparoscopic augmentation ileocystoplasty with Mitrofanoff appendicovesicostomy (RALIMA) protects the upper urinary tract and reestablishes continence in patients with refractory neurogenic bladder. Robotic assistance could provide the benefits of minimally invasive surgery without the challenges of pure laparoscopy. Here, we focus on the outcomes of RALIMA with salient tips and modifications of the technique.
Methods:
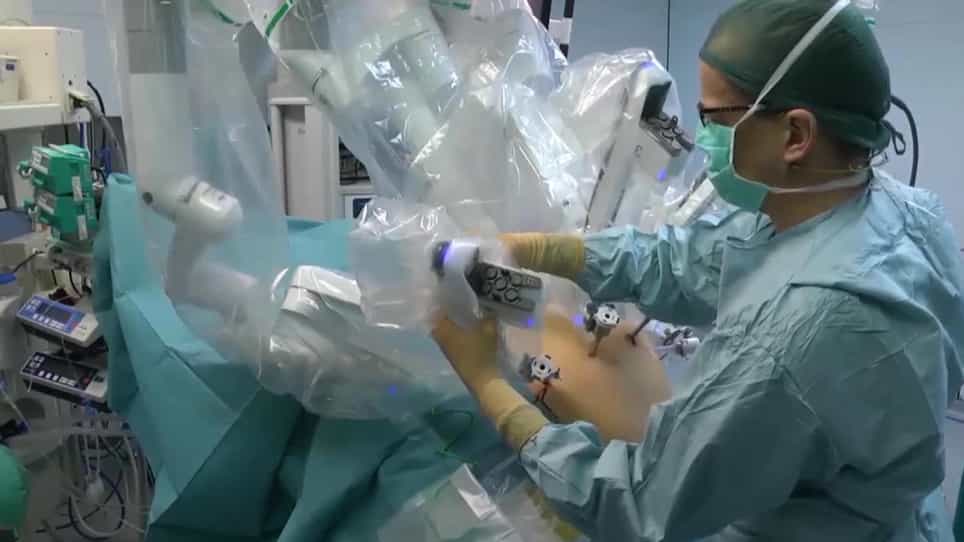
We performed a retrospective review of our robotic database and identified 24 patients who underwent attempted robot-assisted laparoscopic augmentation ileocystoplasty (RALI) between 2008 and 2017 by a single surgeon at an academic center. Outcomes of interest included operative time, hospitalization time, postoperative complications, and change in bladder capacity. RALI and all concomitant procedures were performed using the da Vinci® surgical system (Intuitive Surgical, Sunnyvale, CA, USA).
Results:
Of 24 patients, 20 successfully underwent RALI. Eighty percent underwent concomitant appendicovesicostomy (APV), 40% underwent antegrade continence enema channel formation (ACE), and 30% underwent a bladder neck procedure. Mean operative time was 573 minutes and the most recent RALIMA was 360 minutes. The average return to regular diet was 3.9 days and length of stay was 6.9 days. Mean change in bladder capacity was 244% postoperatively. Thirty-day complications were noted in 35% of patients; one Clavian grade I (5%) complication, five grade II (25%) complications, and one grade IIIb (5%) complication. With a median follow-up of 83.1 months we note a 25% incidence of bladder stones, 15% upper tract stones, 5% incidence of bladder rupture, and 5% small bowel obstruction. No patients required re-augmentation in the follow-up period.
Conclusions:
RALI has similar functional outcomes and complications when compared with the open augmentation ileocystoplasty literature. RALI is desirable due to favorable pain control with decreased length of stay. Long-term outcomes after RALI are similar to the open approach. As the operative time is currently the largest point of criticism with the robotic approach, we discuss modifications to decrease the operative time.