Related Experiment Video
Updated: Sep 25, 2025


A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Characteristics of aldosterone-producing adenomas in patients without plasma renin activity suppression
Haremaru Kubo1, Yuya Tsurutani1, Kosuke Inoue1,2
1Endocrinology and Diabetes Center, Yokohama Rosai Hospital, Yokohama, Kanagawa, Japan.

Abstract:
Primary aldosteronism (PA) usually accompanies suppressed plasma renin activity (PRA) through a negative feedback mechanism. While some cases of PA with unsuppressed PRA were reported, there have been no studies about the characteristics of PA with unsuppressed PRA; thus, these characteristics were examined herein. Nine patients with unsuppressed PRA and 86 patients with suppressed PRA were examined. All patients underwent segmental adrenal venous sampling (sAVS) and adrenalectomy, and were pathologically confirmed to have cytochrome P450 11B2 (CYP11B2)-positive aldosterone-producing adenoma according to international histopathology consensus criteria. Unsuppressed and suppressed PRA were defined as PRA levels of > 1.0 and ≤ 1.0 ng/mL/hr, respectively, in multiple blood samples obtained in the resting position. The unsuppressed PRA group had higher morning cortisol levels (12.6 [8.5, 13.5] vs. 8.5 [7.1, 11.0] μg/dL, P = 0.03) and higher cortisol levels after a 1 mg dexamethasone suppression test (DST) (2.2 [1.6, 2.5] vs. 1.3 [1.0, 1.9] μ g/dL, P = 0.004) than the suppressed PRA group. The unsuppressed PRA group also showed higher aldosterone levels on the non-surgical side during sAVS (P = 0.02 before adrenocorticotropic hormone (ACTH) stimulation, P = 0.002 after ACTH stimulation), a higher intensity of CYP17 expression in the resected adrenal gland (P = 0.02), and a lower clinical complete success rate 1 year after surgery (P = 0.04) compared with those in the suppressed PRA group. These findings suggest that PA should not be ruled out by unsuppressed PRA among patients with hypertension, particularly when their cortisol levels remain unsuppressed in the 1 mg DST. Meanwhile, it should be acknowledged that patients with unsuppressed PRA have higher aldosterone levels on the non-surgical side, and a lower likelihood of postoperative complete clinical success is to be expected.
More Related Videos
 07:43
Endoscopic Endonasal Trans-sphenoidal Approach: Minimally Invasive Surgery for Pituitary Adenomas
Published on: January 17, 2018
 07:36
Induction of Atherosclerotic Plaques Through Activation of Mineralocorticoid Receptors in Apolipoprotein E-deficient Mice
Published on: September 26, 2018
Related Concept Videos
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally,...
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:30
Antihypertensive Drugs: Angiotensin II Receptor Blockers
 01:31
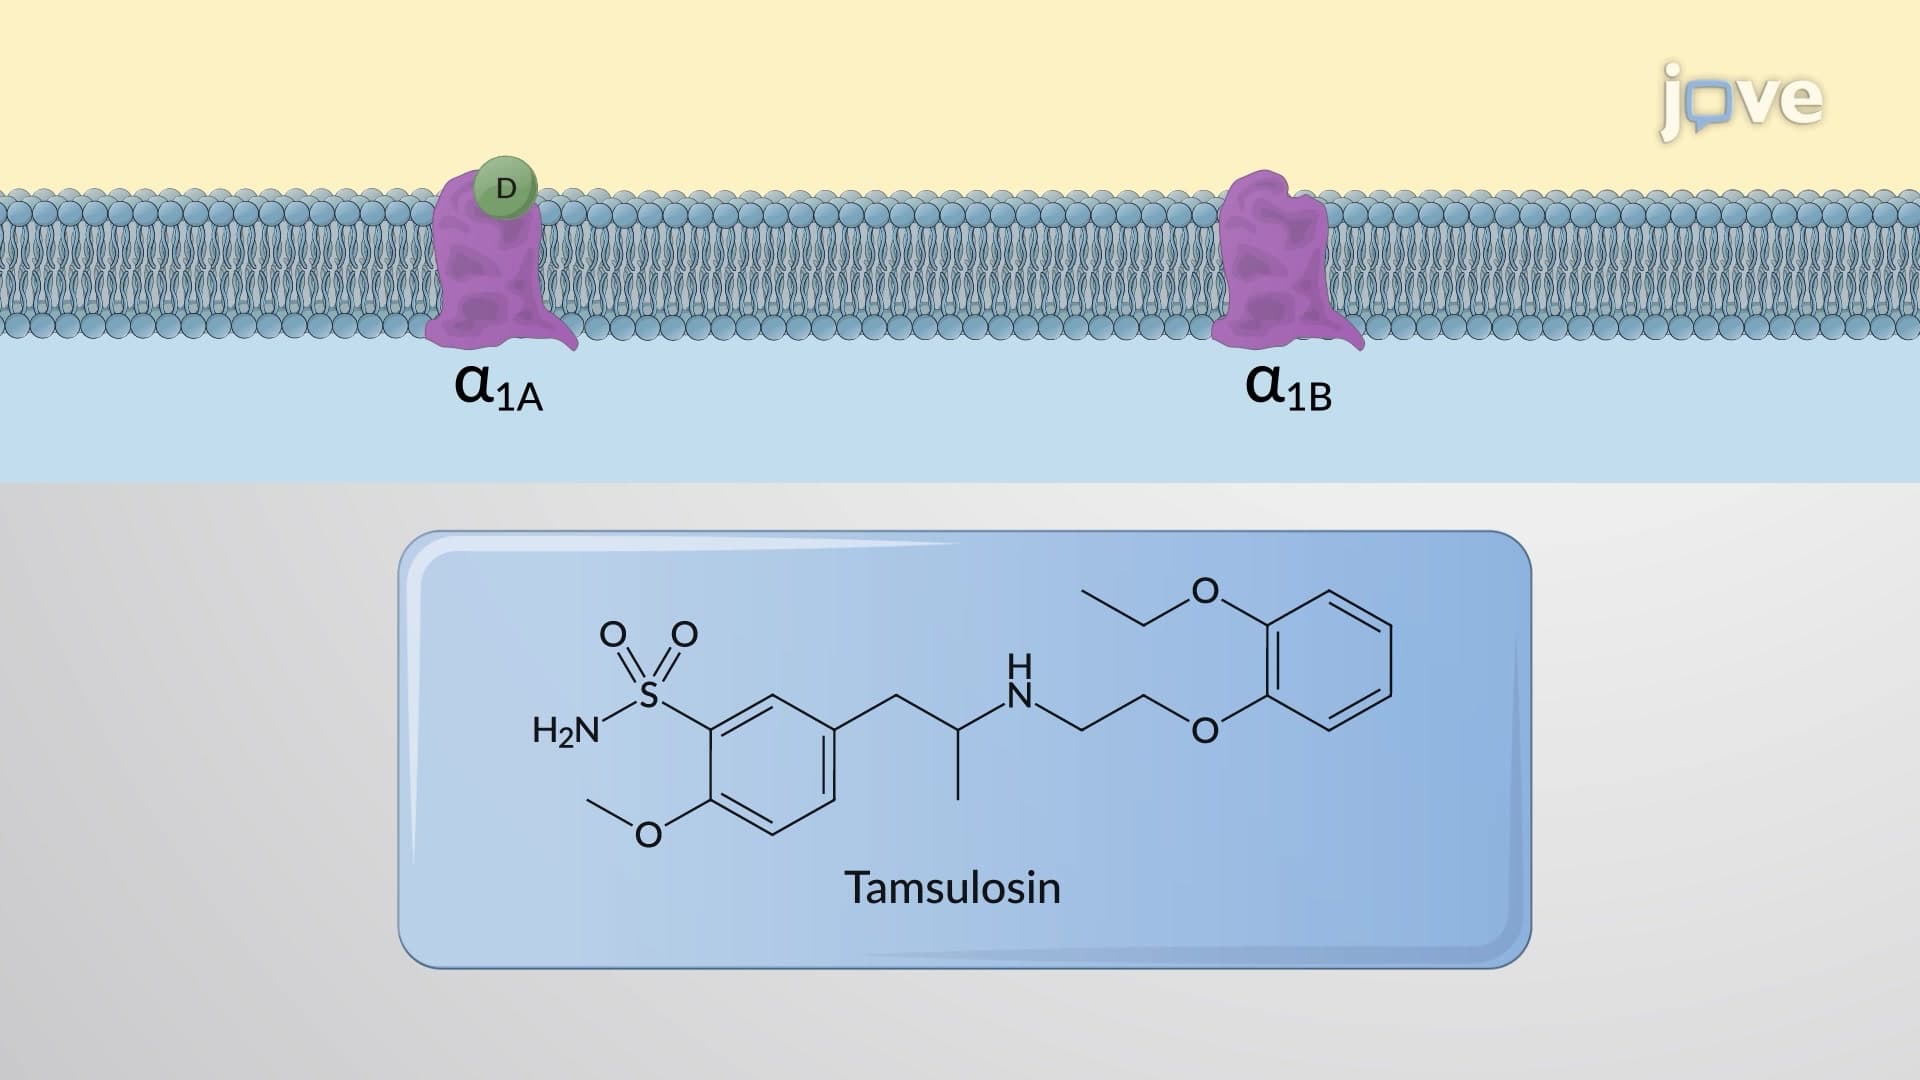
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...