Related Experiment Video
Updated: Sep 3, 2026
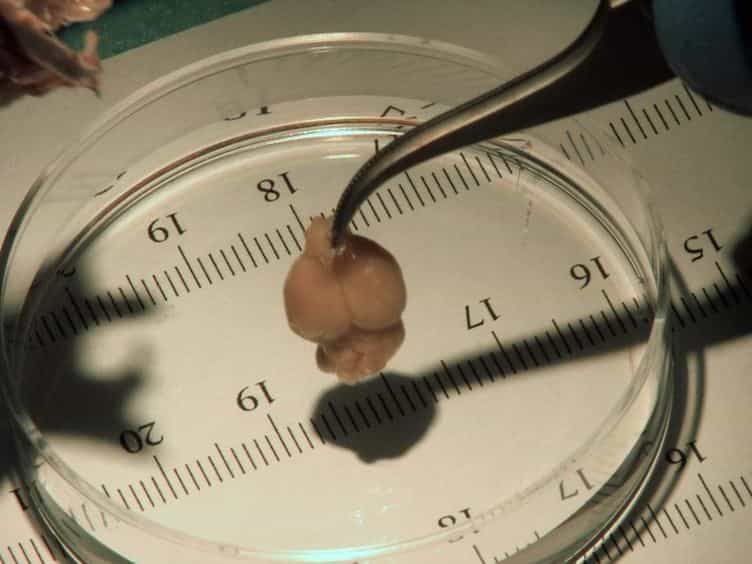

Intravascular Perfusion of Carbon Black Ink Allows Reliable Visualization of Cerebral Vessels
Published on: January 4, 2013
The Cerebral Collateral Cascade: Comprehensive Blood Flow in Ischemic Stroke
Tobias Djamsched Faizy1, Michael Mlynash1, Reza Kabiri1
1From the Departments of Radiology (T.D.F., R.K., G.M.K., M.P.M., M.W., J.J.H.) and Neurology and Neurological Sciences (M.M., S.C., M.G.L., G.W.A.), Stanford University School of Medicine, CA; and Departments of Neuroradiology (T.D.F., R.K., F.F., G.B., J.F.) and Neurosurgery (M.M.M.), University Medical Center Hamburg-Eppendorf, Germany.

Background And Objectives:
Robust cerebral collaterals are associated with favorable outcomes in patients with acute ischemic stroke due to large vessel occlusion treated by thrombectomy. However, collateral status assessment mostly relies on single imaging biomarkers and a more comprehensive holistic approach may provide deeper insights into the biology of collateral perfusion on medical imaging. Comprehensive collateralization is defined as blood flow of cerebral arteries through the brain tissue and into draining veins. We hypothesized that a comprehensive analysis of the cerebral collateral cascade (CCC) on an arterial, tissue, and venous level would predict clinical and radiologic outcomes.
Methods:
This was a multicenter retrospective cohort study of patients with acute stroke undergoing thrombectomy triage. CCC was determined by quantifying pial arterial collaterals, tissue-level collaterals, and venous outflow (VO). Pial arterial collaterals were determined by CT angiography; tissue-level collaterals were assessed on CT perfusion. VO was assessed on CT angiography using the cortical vein opacification score. Three groups were defined: CCC+ (good pial collaterals, tissue-level collaterals, and VO), CCC- (poor pial collaterals, tissue-level collaterals, and VO), and CCCmixed (the remainder of the patients). Primary outcome was functional independence (modified Rankin Scale score 0-2) at 90 days. Secondary outcome was final infarct volume.
Results:
A total of 647 patients met inclusion criteria: 176 CCC+, 345 CCCmixed, and 126 CCC-. Multivariable ordinal logistic regression showed that CCC+ predicted good functional outcomes (odds ratio [OR] 18.9 [95% CI 8-44.5]; p < 0.001) compared with CCC- and CCCmixed. CCCmixed patients likely had better functional outcomes compared with CCC- patients (OR 2.5 [95% CI 1.2-5.4]; p = 0.014). Quantile regression analysis (50th percentile) showed that CCC+ (β -78.5, 95% CI -96.0 to -61.1; p < 0.001) and CCCmixed (β -64.0, 95% CI -82.4 to -45.6; p < 0.001) profiles were associated with considerably lower final infarct volumes compared with CCC- profiles.
Discussion:
Comprehensive assessment of the collateral blood flow cascade in patients with acute stroke is a strong predictor of clinical and radiologic outcomes in patients treated by thrombectomy.

Related Concept Videos
 01:29
Stroke: Introduction and Types
 01:15
Ischemic Stroke l: Introduction
 01:15
Ischemic Stroke ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:22
Cerebral Edema ll: Pathophysiology