Related Experiment Video
Updated: Sep 25, 2025
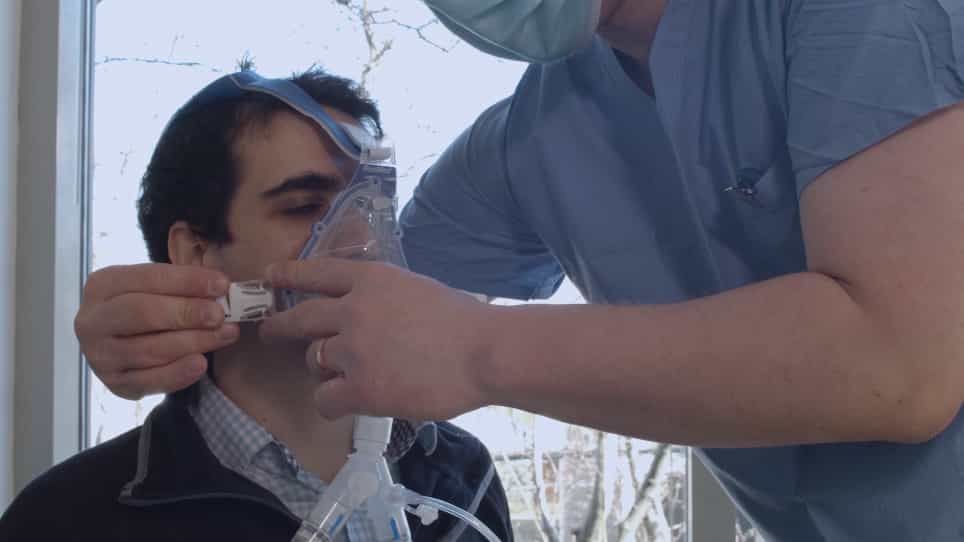
A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
Effects of non-invasive respiratory supports on inspiratory effort in moderate-severe COVID-19 patients. A randomized
Gioacchino Schifino1, Maria L Vega1, Lara Pisani1
1IRCCS Azienda Ospedaliero Universitaria di Bologna, University Hospital Sant´Orsola-Malpighi- Respiratory and Critical Care Unit- Bologna, Italy; Alma Mater Studiorum, University of Bologna, Department of Clinical Integrated and Experimental Medicine (DIMES), Bologna, Italy.

Rationale And Objective:
Various forms of Non-invasive respiratory support (NRS) have been used during COVID-19, to treat Hypoxemic Acute Respiratory Failure (HARF), but it has been suggested that the occurrence of strenuous inspiratory efforts may cause Self Induced Lung Injury(P-SILI). The aim of this investigation was to record esophageal pressure, when starting NRS application, so as to better understand the potential risk of the patients in terms of P-SILI and ventilator induced lung injury (VILI).
Methods And Measurements:
21 patients with early de-novo respiratory failure due to COVID-19, underwent three 30 min trials applied in random order: high-flow nasal cannula (HFNC), continuous positive airway pressure (CPAP), and non-invasive ventilation (NIV). After each trial, standard oxygen therapy was reinstituted using a Venturi mask (VM). 15 patients accepted a nasogastric tube placement. Esophageal Pressure (ΔPes) and dynamic transpulmonary driving pressure (ΔPLDyn), together with the breathing pattern using a bioelectrical impedance monitor were recorded. Arterial blood gases were collected in all patients.
Main Results:
No statistically significant differences in breathing pattern and PaCO2 were found. PaO2/FiO2 ratio improved significantly during NIV and CPAP vs VM. NIV was the only NRS to reduce significantly ΔPes vs. VM (-10,2 ±5 cmH20 vs -3,9 ±3,4). No differences were found in ΔPLDyn between NRS (10,2±5; 9,9±3,8; 7,6±4,3; 8,8±3,6 during VM, HFNC, CPAP and NIV respectively). Minute ventilation (Ve) was directly dependent on the patient's inspiratory effort, irrespective of the NRS applied. 14% of patients were intubated, none of them showing a reduction in ΔPes during NRS.
Conclusions:
In the early phase of HARF due to COVID-19, the inspiratory effort may not be markedly elevated and the application of NIV and CPAP ameliorates oxygenation vs VM. NIV was superior in reducing ΔPes, maintaining ΔPLDyn within a range of potential safety.


Related Concept Videos
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:23
Acute Respiratory Failure-IV
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History