Related Experiment Video
Updated: Sep 25, 2025

Isolation and Characterization of Satellite Cells from Rat Head Branchiomeric Muscles
Published on: July 20, 2015
Differences in craniofacial morphology between platybasic and nonplatybasic patients with velopharyngeal dysfunction
Ariela Nachmani1, Muhamed Masalha2, Ameen Biadsee3
1Faculty of Communication Disorders, Hadassah Academic College, Jerusalem, Israel; Department of Communication Disorders, Sackler Faculty of Medicine, Tel Aviv University, Tel Aviv, Israel.

Introduction:
This study aimed to identify the characteristics of cranial-base morphology in platybasic and nonplatybasic patients with palatal anomalies and velopharyngeal dysfunction (VPD) compared with control subjects to investigate structural factors related to craniofacial morphology that affect the nasopharyngeal space and may influence velopharyngeal function, and to develop precise treatments for specific patients with VPD.
Methods:
Three hundred eighty-six patients with VPD and various palatal anomalies were studied retrospectively. The control group included 126 healthy patients with normal speech. Lateral cephalometric images assessed craniofacial morphology.
Results:
Nonplatybasic patients and control subjects had larger SNA, S-Ba-Ptm, and N-Ba-PP angles (in the craniomaxillary complex), and platybasic patients had larger nasopharyngeal ANS-Ptm-Ve and Ba-S-Ptm angles and longer Ve-T and Ve-Ba distances than the nonplatybasic patients. All study patients had larger ANB, Gn-Go-Ar, and PP-MP angles (in the craniomandibular complex). Nonplatybasic patients had smaller Ba-SN angles than platybasic patients and controls because of more acute N-S-Ptm angle. Among the nonplatybasic patients, Ve-T length tended to be shorter (with no significant difference between groups) and located more inferiorly (because of the smallest ANS-Ptm-Ve angle) in relation to the maxilla. Thus, the nasopharynx was narrower horizontally but longer vertically than in patients with platybasia.
Conclusions:
Cranial-base flexure influences the shape of the skull base and facial-skeletal structure and may alter the pharyngeal space between them. This finding should help improve preoperative planning regarding the effect of the pharyngeal flap height relative to the nasopharynx and oropharynx ratio that affects surgical outcomes, such as resonance and residual VPD. In patients with Class III malocclusion and maxillary constriction, careful planning of presurgical orthodontic treatment is needed in maxillary advancement procedures. Orthodontic and surgical collaboration can help prevent postoperative VPD, especially in platybasic patients.
Related Concept Videos
 01:25
Deglutition
Swallowing can be divided into three stages: the voluntary phase, the pharyngeal phase, and the esophageal phase. Although the...
 01:24
Facial Feedback Hypothesis
 01:20
Pharynx
Nasopharynx
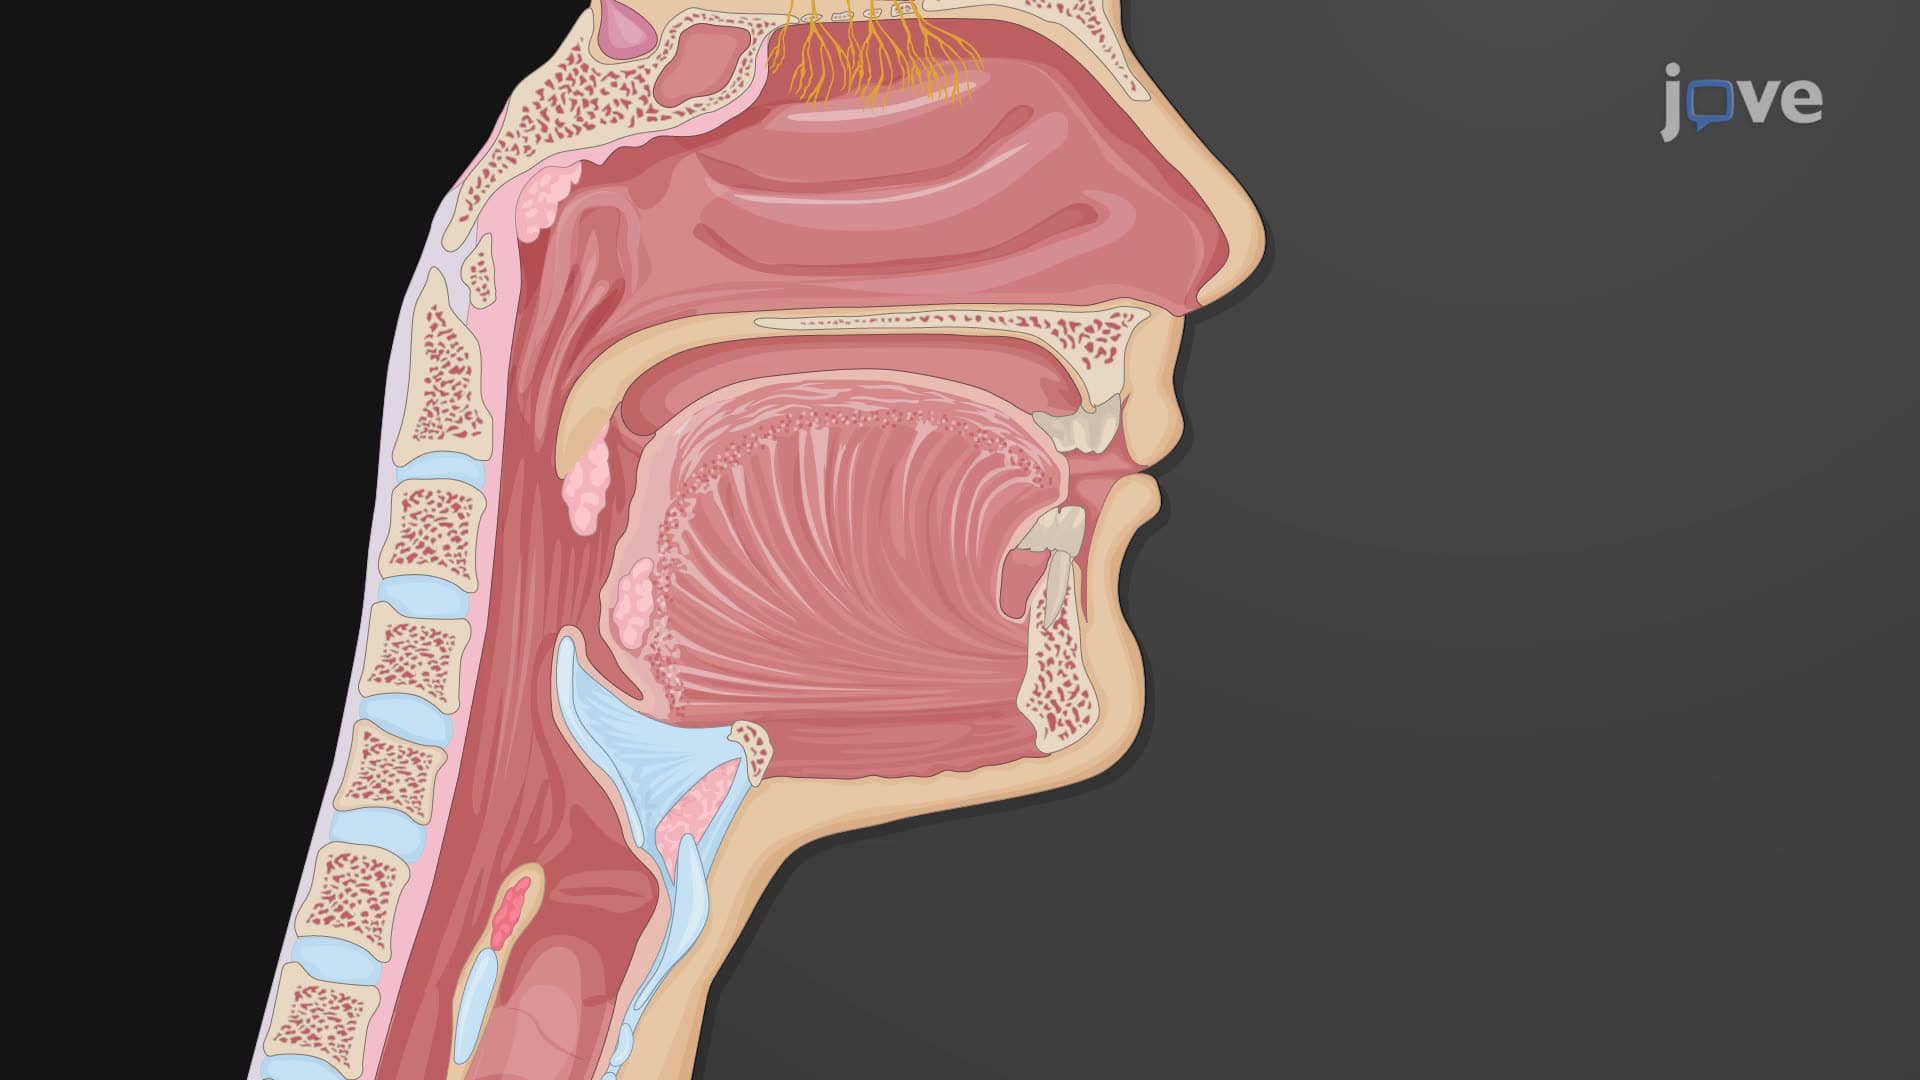
The nasopharynx, bordered by the conchae of the nasal cavity, serves exclusively as an air conduit. In its superior region, the pharyngeal tonsils or adenoids are located. These tonsils are clusters of lymphoid reticular tissue akin to a lymph node. The precise...
 01:19
Cranial Nerves: Overview and Anatomy
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:09
Cytoskeletal Linker Proteins - Plakins