Related Experiment Video
Updated: Sep 24, 2025

Esophageal Heat Transfer for Patient Temperature Control and Targeted Temperature Management
Published on: November 21, 2017
Discrepancies Between the Management of Fever in Young Infants Admitted From Urban General Emergency Departments and
Priya Narayanan Jain, Rikah Lerer, Jaeun Choi1
1Albert Einstein College of Medicine, Bronx, NY.

Insights
Management of febrile infants in general emergency departments (GEDs) significantly deviates from pediatric emergency departments (PEDs) and expert guidelines. This inconsistency in testing and treatment may risk young infants missing bacterial infections.
Area of Science:
- Pediatric Emergency Medicine
- Infectious Disease Management
- Healthcare Quality Improvement
Background:
- Most pediatric emergency visits occur in general emergency departments (GEDs).
- Management of febrile infants requires adherence to specific guidelines to ensure timely diagnosis and treatment of potential bacterial infections.
- Variations in care between GEDs and pediatric emergency departments (PEDs) may impact patient outcomes.
Purpose of the Study:
- To assess if medical decision-making for febrile infants differs between GEDs and PEDs.
- To determine if management in GEDs deviates from established pediatric expert consensus guidelines.
- To identify potential risks to young infants due to inconsistent care practices.
Main Methods:
- Retrospective chart review of 176 febrile infants (<60 days old) admitted over 3 years.
- Comparison of care in 13 GEDs versus 1 PED.
- Assessment of adherence to critical management components including blood cultures, urine cultures, lumbar puncture, and antibiotic administration based on age (<29 days vs. 29-60 days).
Main Results:
- Infants <29 days managed in GEDs received all critical interventions in 65.6% of cases, compared to 96.9% in the PED (P=0.003).
- Infants 29-60 days managed in GEDs received all critical interventions in 64.3% of cases, versus 91.1% in the PED (P<0.001).
- Significant differences were observed in testing and treatment practices between GEDs and the PED.
Conclusions:
- Management of febrile infants in the studied GEDs significantly differs from PEDs and expert consensus.
- Inconsistent testing and treatment practices in GEDs may pose a risk for undetected bacterial infections in young infants.
- Highlights the need for improved adherence to pediatric guidelines in general emergency settings.
Introduction/Objective:
Most pediatric emergency visits occur in general emergency departments (GED). Our study aims to assess whether medical decision making regarding the management of febrile infants differs in GEDs from pediatric EDs (PED) and deviates from pediatric expert consensus.
Methods:
We conducted a retrospective chart review on patients younger than 60 days with fever admitted from 13 GEDs versus 1 PED to a children's hospital over a 3-year period. Adherence to consensus guidelines was measured by frequency of performing critical components of initial management, including blood culture, urine culture, attempted lumbar puncture, and antibiotic administration (<29 days old), or complete blood count and/or C-reactive protein, blood culture, and urine culture (29-60 days old). Additional outcomes included lumbar puncture, collecting urine specimens via catheterization, and timing of antibiotics.
Results:
A total of 176 patient charts were included. Sixty-four (36%) patients were younger than 29 days, and 112 (64%) were 29 to 60 days old. Eighty-eight (50%) patients were admitted from GEDs.In infants younger than 29 days managed in the GEDs (n = 32), 65.6% (n = 21) of patients underwent all 4 critical items compared with 96.9% (n = 31, P = 0.003) in the PED. In infants 29 to 60 days old managed in GEDs (n = 56), 64.3% (n = 36) patients underwent all 3 critical items compared with 91.1% (n = 51, P < 0.001) in the PED.
Conclusions:
This retrospective study suggests that providers managing young infants with fever in 13 GEDs differ significantly from providers in the PED examined and literature consensus. Inconsistent testing and treatment practices may put young infants at risk for undetected bacterial infection.
Related Concept Videos
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever:
 01:26
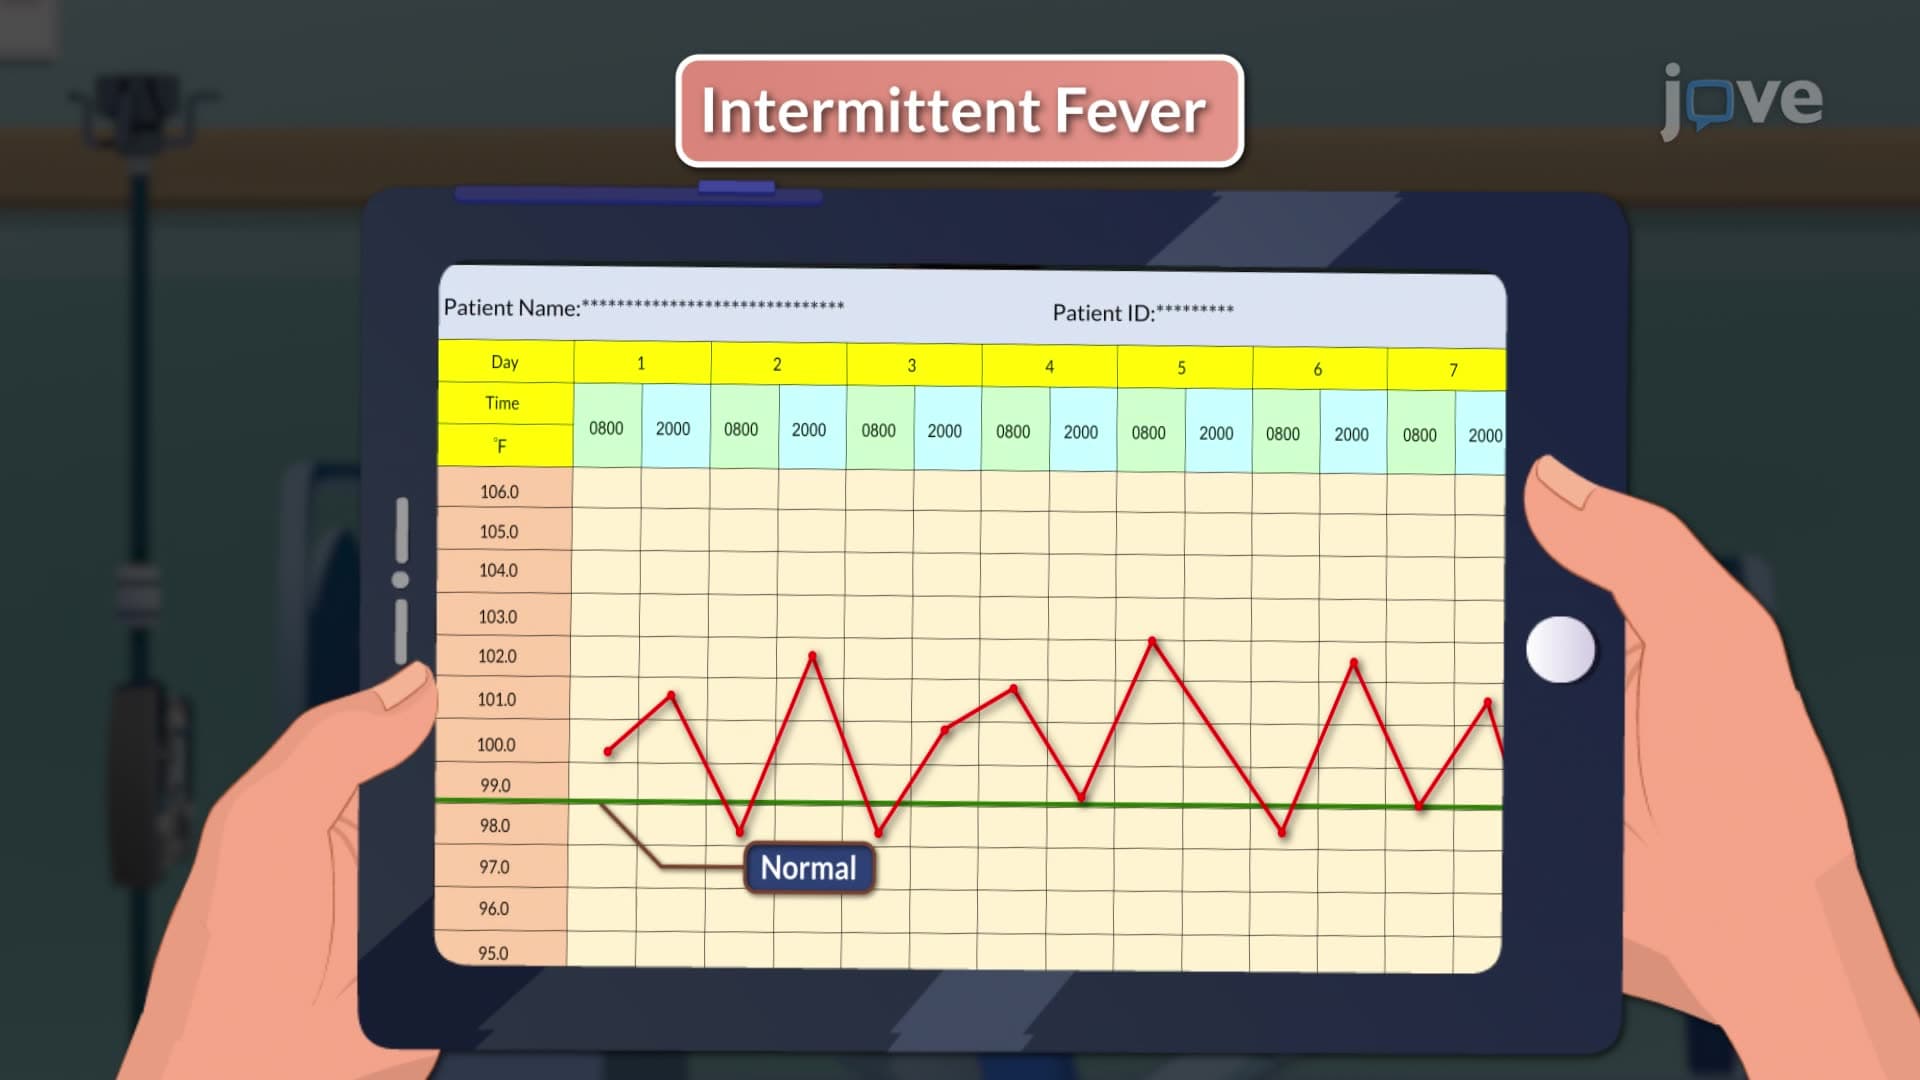
Patterns of Fever
 01:25
Increased Body Temperature
 01:25
Types of Fever
Here are the different types of fever:
 01:28
Factors Affecting Body Temperature
Factors may include:
 01:14
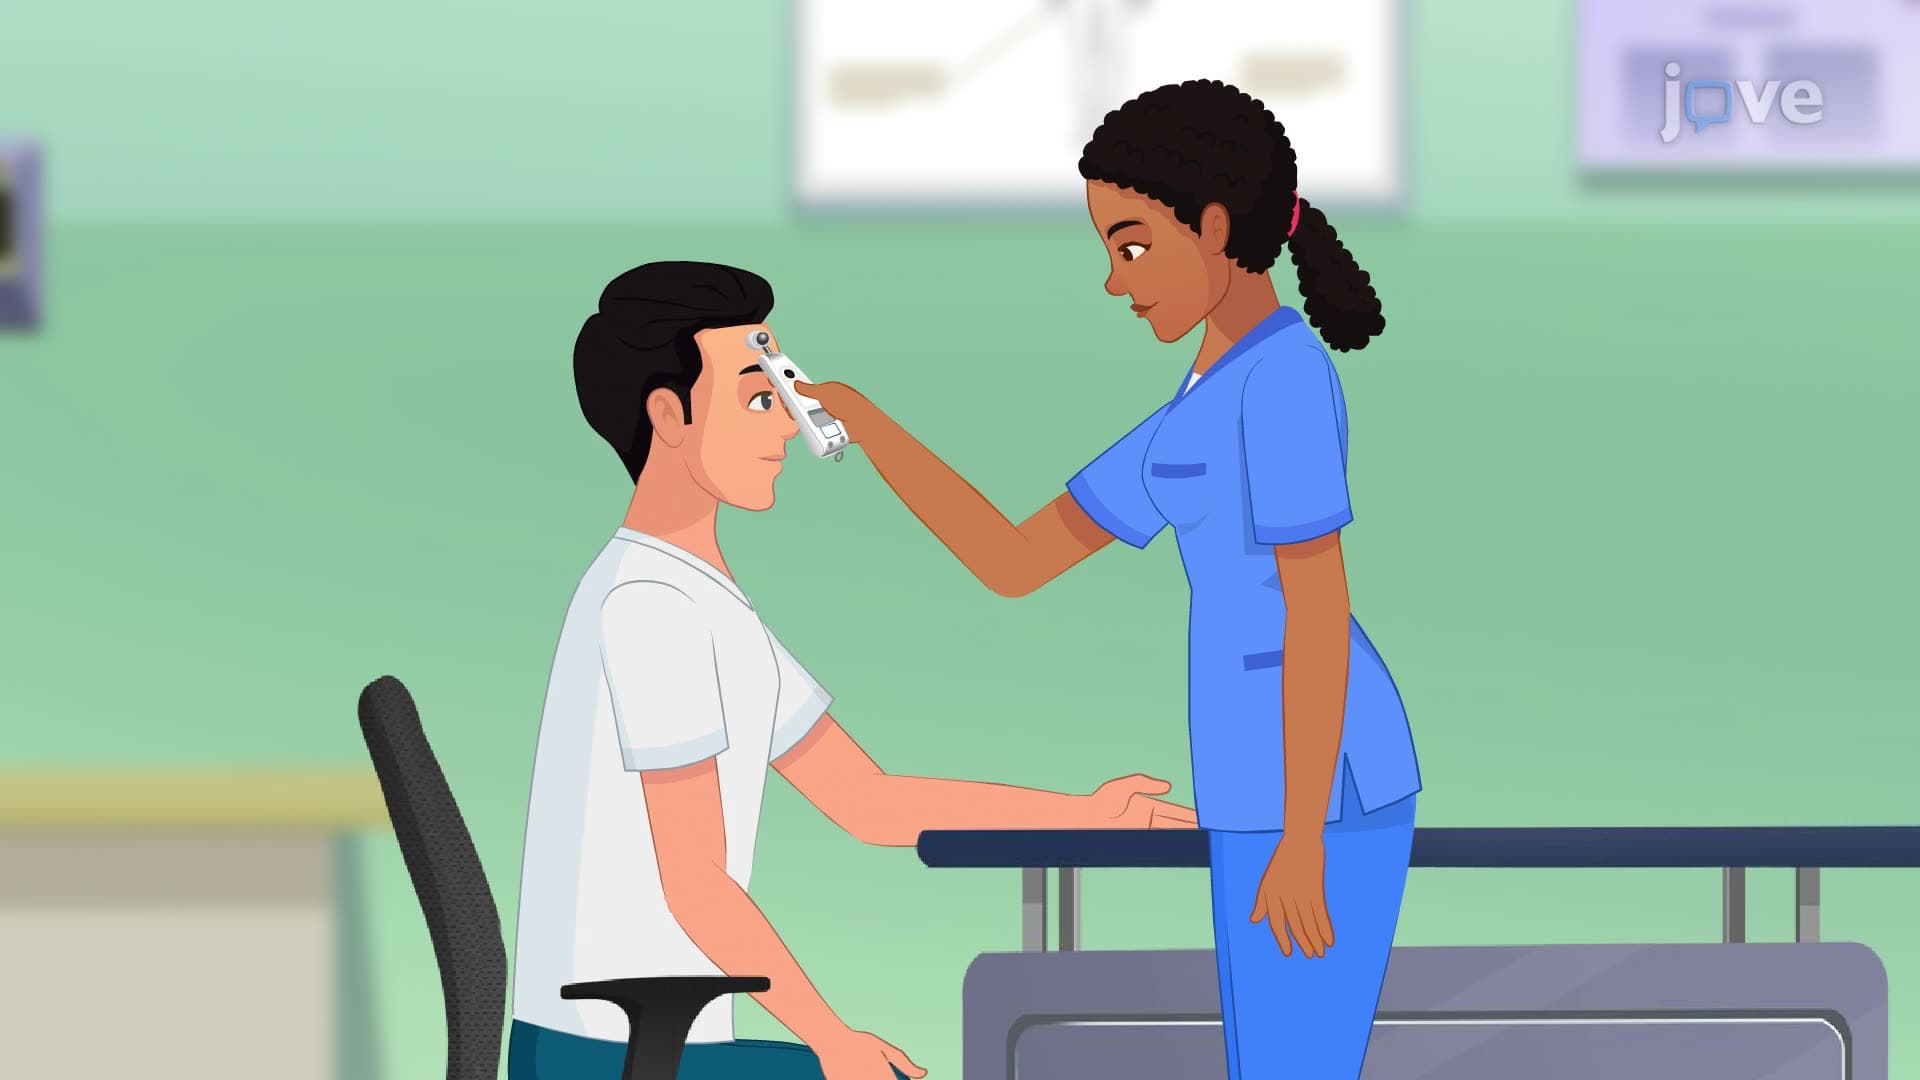
Temperature Measurement Sites
Oral: When assessing oral temperature, the thermometer tip should be placed under the tongue in the posterior sublingual pocket. It offers accurate readings and can be...