Related Experiment Video
Updated: Sep 24, 2025


Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Retrospective Review of Transpulmonary Pressure Guided Positive End-Expiratory Pressure Titration for Mechanical
Jesse Liou1, Daniel Doherty1, Tom Gillin2
1Department of Emergency/Internal Medicine, Christiana Care, Newark, DE.

Objectives:
Acute respiratory distress syndrome is treated by utilizing a lung protective ventilation strategy. Obesity presents with additional physiologic considerations, and optimizing ventilator settings may be limited with traditional means. Transpulmonary pressure (PL) obtained via esophageal manometry may be more beneficial to titrating positive end-expiratory pressure (PEEP) in this population. We sought to determine the feasibility and impact of implementation of a protocol for use of esophageal balloon to set PEEP in obese patients in a community ICU.
Design:
Retrospective cohort study of obese (body mass index [BMI] ≥ 35 kg/m2) patients undergoing individualized PEEP titration with esophageal manometry. Data were extracted from electronic health record, and Wilcoxon signed rank test was performed to determine whether there were differences in the ventilatory parameters over time.
Setting:
Intensive care unit in a community based hospital system in Newark, Delaware.
Patients:
Twenty-nine mechanically ventilated adult patients with a median BMI of 45.8 kg/m2 with acute respiratory distress syndrome (ARDS).
Intervention:
Individualized titration of PEEP via esophageal catheter obtained transpulmonary pressures.
Measurements And Main Results:
Outcomes measured include PEEP, oxygenation, and driving pressure (DP) before and after esophageal manometry at 4 and 24 hr. Clinical outcomes including adverse events (pneumothorax and pneumomediastinum), increased vasopressor use, rescue therapies (inhaled pulmonary vasodilators, extracorporeal membrane oxygenation, and new prone position), continuous renal replacement therapy, and tracheostomy were also analyzed. Four hours after PEEP titration, median PEEP increased from 12 to 20 cm H2O (p < 0.0001) with a corresponding decrease in median DP from 15 to 13 cm H2O (p = 0.002). Subsequently, oxygenation improved as median Fio2 decreased from 0.8 to 0.6 (p < 0.0001), and median oxygen saturation/Fio2 (S/F) ratio improved from 120 to 165 (p < 0.0001). One patient developed pneumomediastinum. No pneumothoraces were identified. Improvements in oxygenation continued to be seen at 24 hr, compared with the prior 4 hr mark, Fio2 (0.6-0.45; p < 0.004), and S/F ratio (165-211.11; p < 0.001). Seven patients required an increase in vasopressor support after 4 hours. Norepinephrine and epinephrine were increased by 0.05 (± 0.04) µg/kg/min and 0.02 (± 0.01) µg/kg/min on average, respectively.
Conclusions:
PL-guided PEEP titration in obese patients can be used to safely titrate PEEP and decrease DP, resulting in improved oxygenation.

Related Concept Videos
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:14
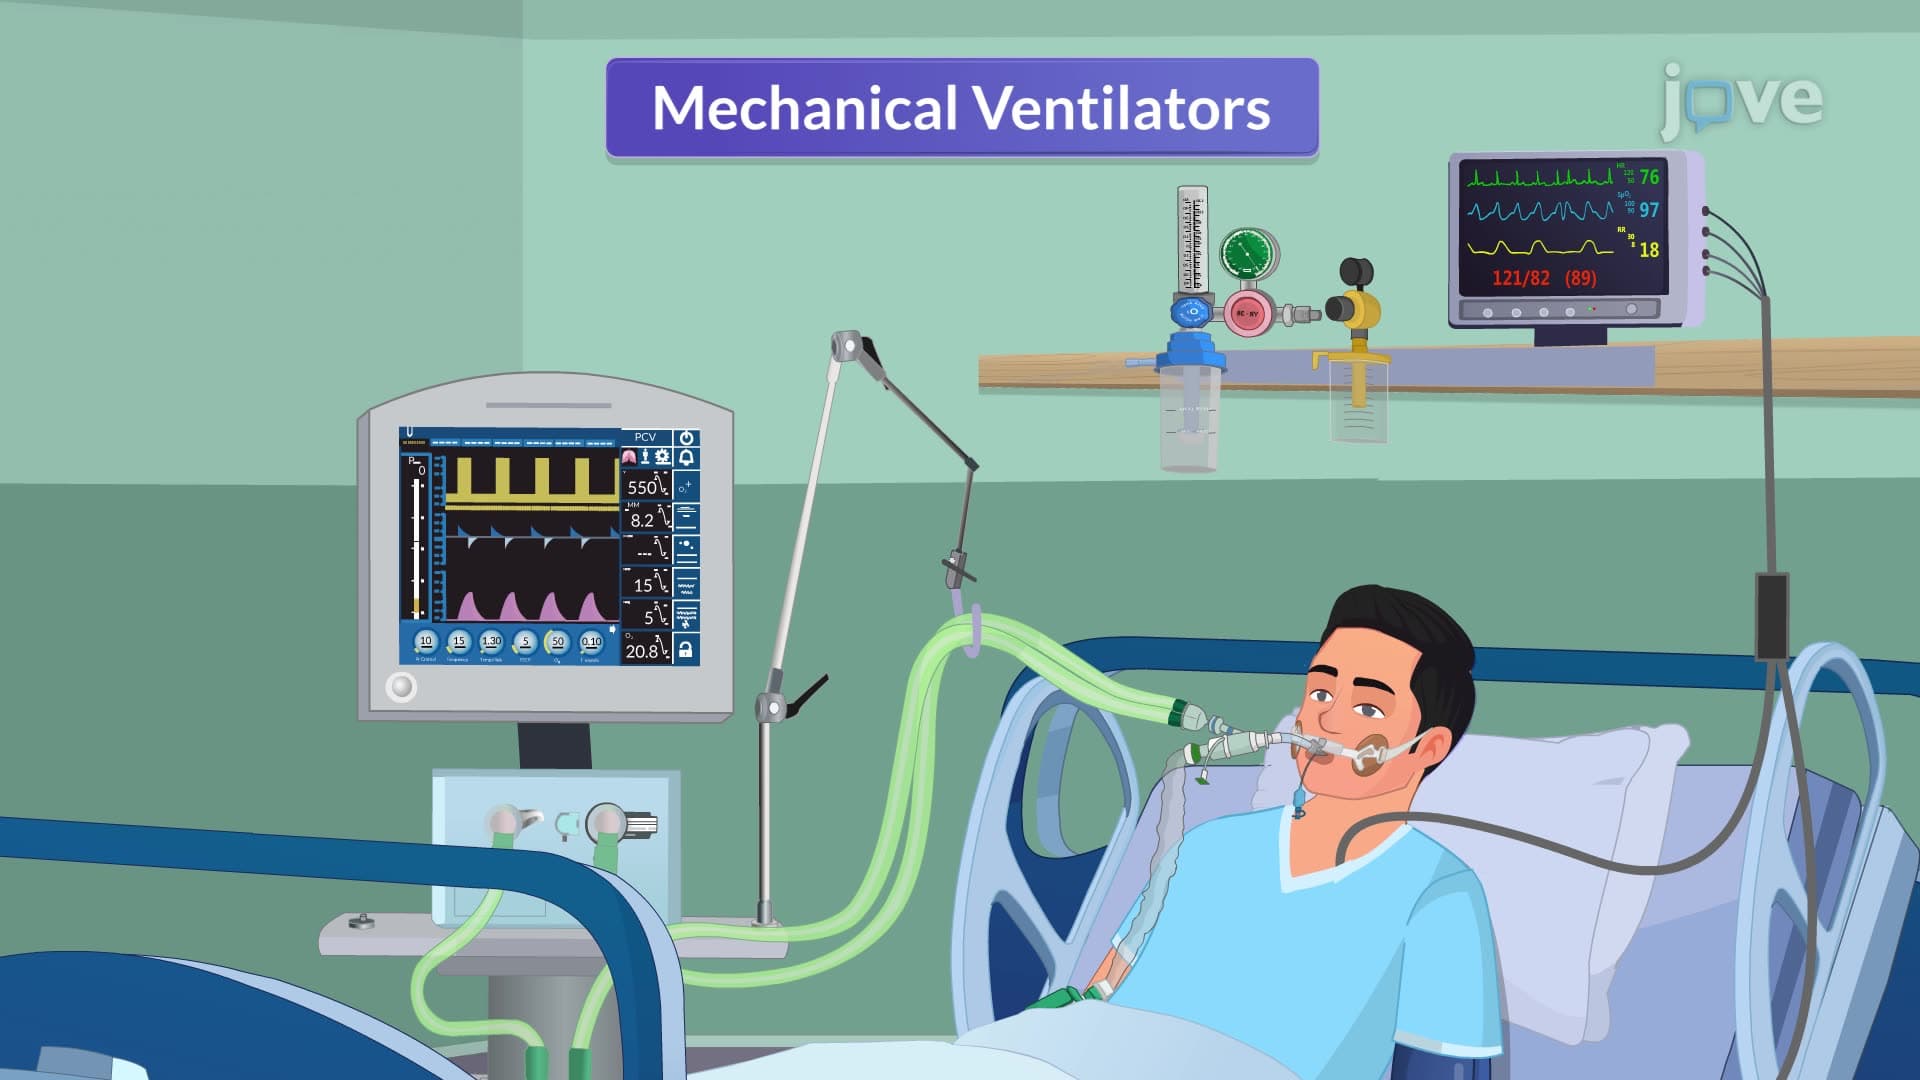
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:30
Acute Respiratory Failure-III
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include: