Mini Temporal Craniotomy Using Anatomical Surface Landmarks for Temporal Lobe Epilepsy: Technical Note and Clinical Outcomes
Related Experiment Video
Updated: Sep 24, 2025
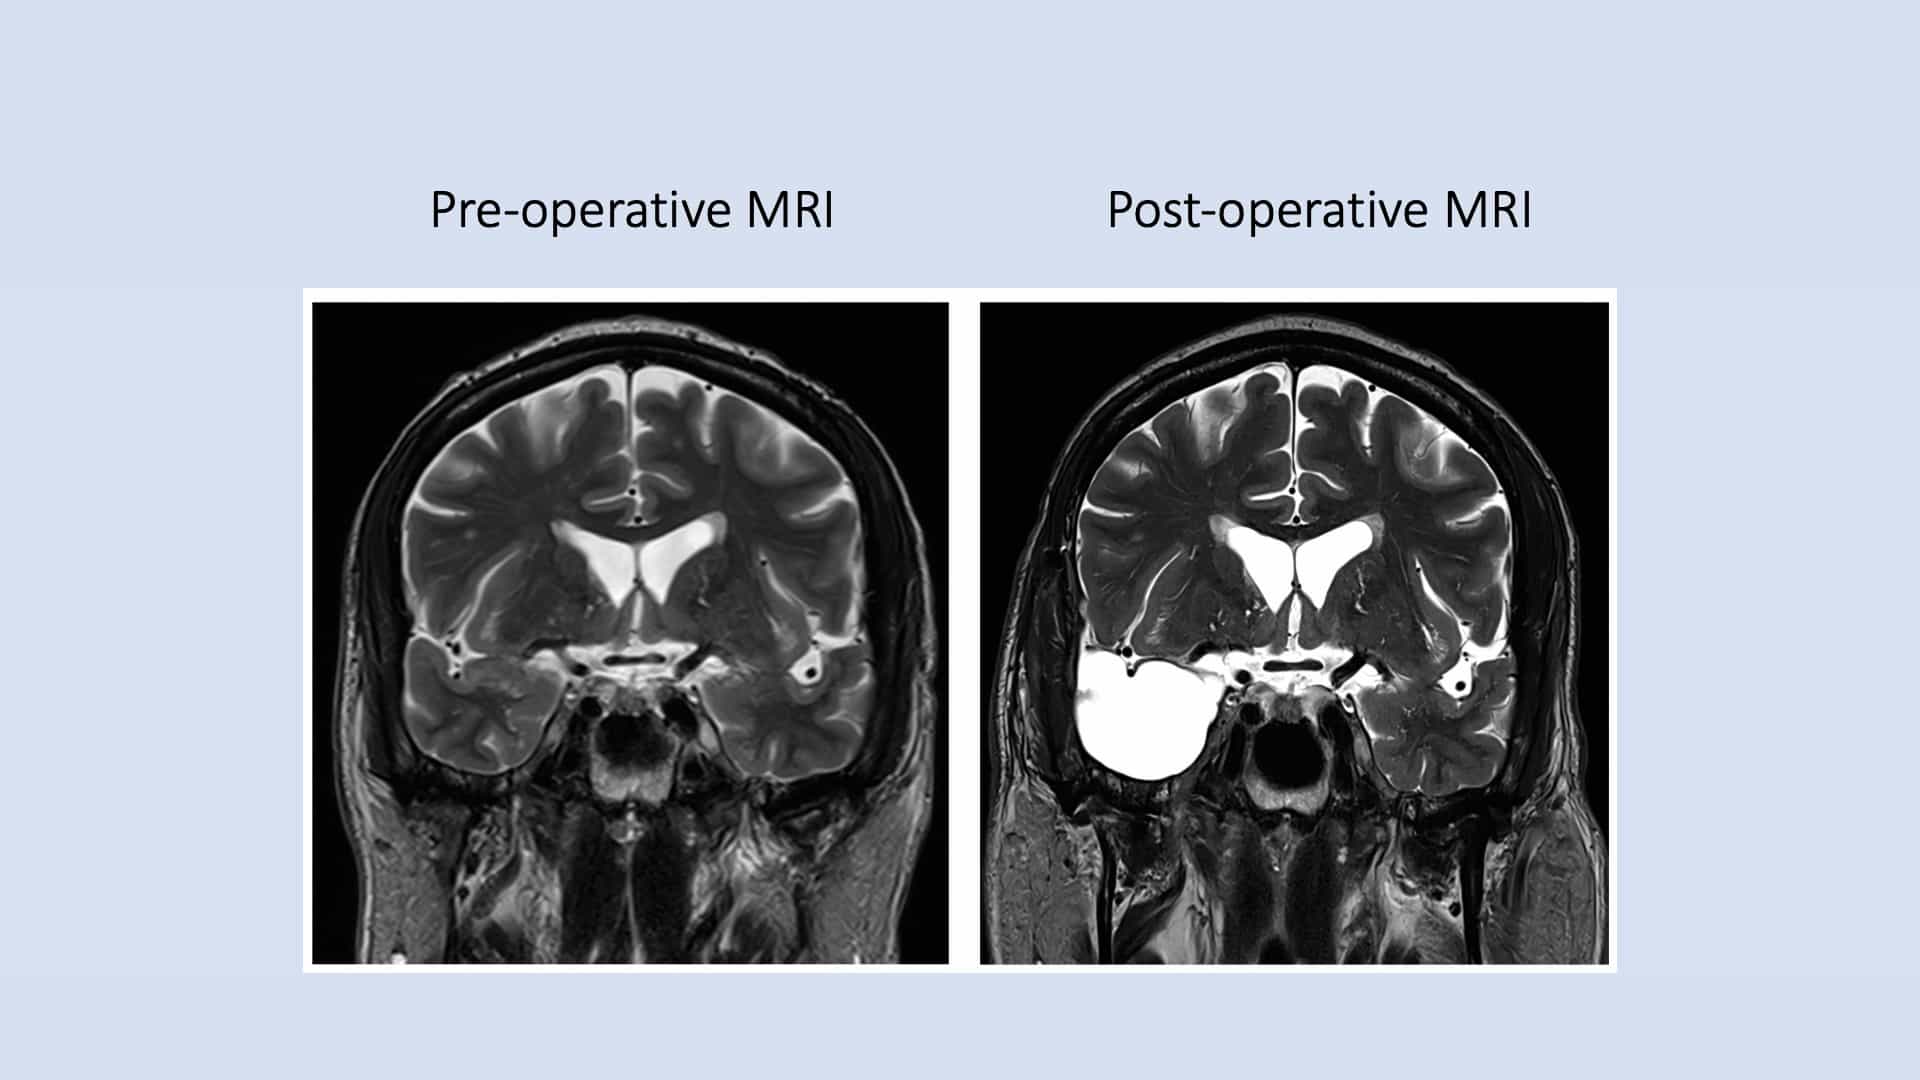
Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Ramesh Sharanappa Doddamani1, Heri Subianto2, Jitin Bajaj3
1Department of Neurosurgery, All India Institute of Medical Sciences, Jabalpur, India.

Background:
Patients with temporal lobe epilepsy are subjected to standard temporal lobectomy wherever indicated. This is performed using a reverse question mark flap and a standard frontotemporal craniotomy. We describe the technique of minitemporal craniotomy (3 × 3cms) for temporal lobe epilepsy (TLE) and analyze the clinical outcomes of patients operated using this approach.
Objectives:
To describe the technique of minitemporal craniotomy for TLE without navigation guidance and to analyze the clinical outcomes of patients operated using this approach.
Materials And Method:
This was a retrospective analysis of all consecutive TLE cases operated at our institute from 2014 to 2019, via minitemporal craniotomy, using surface landmarks only without navigation guidance. The surgical technique, indications for surgery, and their clinical outcomes were analyzed.
Results:
A total number of 48 patients underwent surgery for TLE. There were no complications except three patients who had transient hemiparesis. The average duration of hospital stay was 4 days following surgery. Out of 28 patients with mesial temporal sclerosis, 22 (82%) had international league against epilepsy, Class I seizure outcome, 4 (12.5%) had Class II outcome and 2 (5.5%) had Class III outcome. 9 patients with dysembryoplastic neurectodermal tumor (DNET), 4 gangliogliomas, 2 neurocystecercosis (NCC), all had Class I outcome. Out of the five patients with MTS and associated anterior temporal focal cortical dysplasia (FCD), four (80%) had a Class I outcome, whereas one (20%) had Class II outcome.
Conclusion:
Utilizing surface anatomical landmarks, minitemporal craniotomy can be performed in even peripheral centers without neuronavigation, with good cosmesis, seizure outcomes.
More Related Videos
 09:32
Network Analysis of Foramen Ovale Electrode Recordings in Drug-resistant Temporal Lobe Epilepsy Patients
Published on: December 18, 2016
 11:58
Minimally Invasive Thumb-sized Pterional Craniotomy for Surgical Clip Ligation of Unruptured Anterior Circulation Aneurysms
Published on: August 11, 2015