Related Experiment Video
Updated: Sep 24, 2025
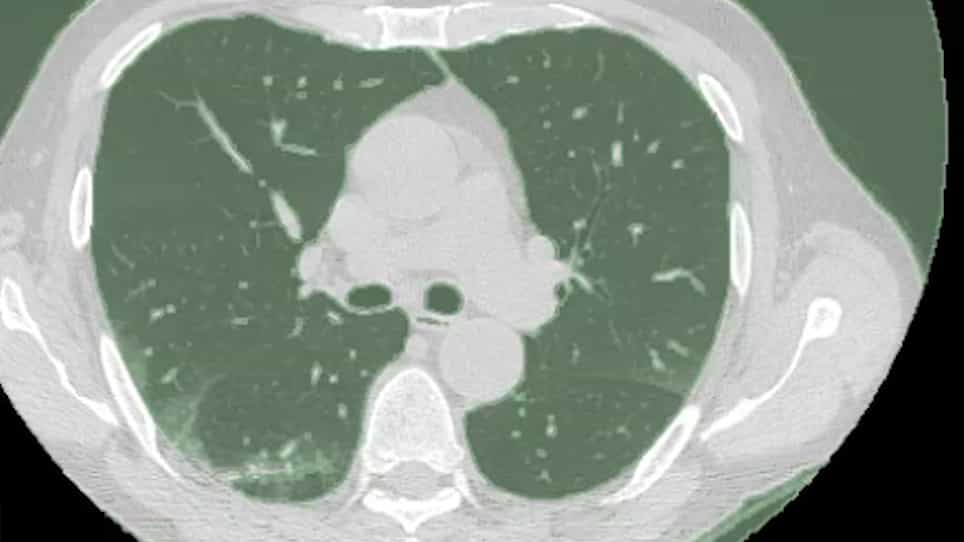

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Chest CT-based Assessment of 1-year Outcomes after Moderate COVID-19 Pneumonia
Marialuisa Bocchino1, Roberta Lieto1, Federica Romano1
1From the Respiratory Medicine Section, Department of Clinical Medicine and Surgery, Federico II University of Naples, Via S Pansini 5, 80131 Naples, Italy (M.B., L.C., D.S.); and Department of Radiology (R.L., F.R., G.S., G.B., E.M., T.V., G.R.) and Pathophysiology and Respiratory Rehabilitation Department of Critical Area (G.F.), Monaldi Hospital, AO dei Colli, Naples, Italy.

Background:
COVID-19 pneumonia may lead to pulmonary fibrosis in the long term. Chest CT is useful to evaluate changes in the lung parenchyma over time.
Purpose:
To illustrate the temporal change of lung abnormalities on chest CT scans associated with COVID-19 pneumonia over 1 year.
Materials And Methods:
In this prospective study, patients previously hospitalized due to COVID-19 pneumonia who visited the radiology department of a tertiary care center for imaging follow-up were consecutively enrolled between March 2020 and July 2021. Exclusion criteria were acute respiratory distress syndrome, requirement of intubation and/or mechanical ventilation, pulmonary embolism, and any interstitial lung disease. High-resolution volumetric noncontrast chest CT scans were acquired at 3, 6, and 12 months from the first diagnosis and were compared with baseline CT scans. The imaging features analyzed were ground-glass opacity (GGO), consolidation, pleuroparenchymal band, linear atelectasis, bronchiectasis and/or bronchiolectasis, reticulation, traction bronchiectasis and/or bronchiolectasis, and honeycombing. The prevalence distribution of lung abnormalities was recorded at all time points.
Results:
Eighty-four participants (56 men; mean age, 61 years ± 11 [SD]) were studied. GGOs and consolidations represented the main baseline lung abnormalities, accounting for a median severity score of 9 (IQR, 7-12.7; maximum possible score, 20), which indicates moderate lung involvement. The baseline prevalence of GGOs decreased from 100% to 2% of participants at 1 year, and that of consolidations decreased from 71% to 0% at 6 months. Fibrotic-like abnormalities (pleuroparenchymal bands, linear atelectasis, bronchiectasis and/or bronchiolectasis) were detected at 3 months (50% of participants), 6 months (42% of participants), and 1 year (5% of participants). Among these, pleuroparenchymal bands were the most represented finding. Fibrotic changes (reticulation and traction bronchiectasis and/or bronchiolectasis) were detected at 3-6 months (2%) and remained stable at 1 year, with no evidence of honeycombing. At 1 year, lung abnormalities due to COVID-19 pneumonia were completely resolved in 78 of 84 (93%) participants.
Conclusion:
Residual lung abnormalities in individuals hospitalized with moderate COVID-19 pneumonia were infrequent, with no evidence of fibrosis at 1-year chest CT. © RSNA, 2022.
More Related Videos
 07:10
Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
 05:39
Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
Related Concept Videos
 01:30
Pneumonia III: Complications and Assessment
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...