Related Experiment Video
Updated: Sep 23, 2025


Observational Study Protocol for Repeated Clinical Examination and Critical Care Ultrasonography Within the Simple Intensive Care Studies
Published on: January 16, 2019
Relationship Between Initial Urine Output and Mortality in Patients Hospitalized in Cardiovascular Intensive Care
Le Li1, Zhenhao Zhang1, Yulong Xiong1
1National Center for Cardiovascular Diseases, Fu Wai Hospital, Peking Union Medical College, Chinese Academy of Medical Sciences, Beijing, China.

Insights
Both low and very high urine output (UO) in cardiovascular intensive care unit (CICU) patients are linked to increased mortality. This U-shaped relationship highlights UO as a critical prognostic indicator.
Area of Science:
- Cardiology
- Intensive Care Medicine
- Nephrology
Background:
- Decreased urine output (UO) is linked to adverse outcomes in some patient groups, but its impact on cardiovascular disease patients is not well-established.
- The prognostic significance of both decreased and increased UO in cardiovascular intensive care unit (CICU) patients remains unclear.
Purpose of the Study:
- To investigate the association between abnormal urine output (UO) levels and patient outcomes within the CICU.
- To determine if both decreased and increased UO are risk factors for mortality and other adverse events in CICU patients.
Main Methods:
- Retrospective cohort analysis utilizing the Medical Information Mart for Intensive Care III (MIMIC-III) database.
- Included 13,279 CICU patients, categorizing initial 24-hour UO relative to a reference range (0.5-1.0 ml/kg/h).
- Assessed 30-day mortality, 90-day mortality, ICU mortality, hospital mortality, and need for mechanical ventilation or vasopressors using multivariable logistic regression.
Main Results:
- Low UO (< 0.5 ml/kg/h) and very high UO (≥ 2.0 ml/kg/h) were both significantly associated with increased 30-day mortality compared to the reference group.
- Adjusted analyses confirmed these associations, with low UO (aOR=2.023) and very high UO (aOR=1.771) remaining significant risk factors.
- Both decreased and increased UO were identified as risk factors for 90-day mortality, ICU/hospital mortality, and the use of mechanical ventilation and vasopressors.
Conclusions:
- Both decreased and increased urine output are significantly associated with short-term mortality in CICU patients.
- The relationship between urine output and mortality in this population follows a U-shaped curve, rather than a linear pattern.
- Urine output serves as a crucial indicator for predicting prognosis in cardiovascular intensive care.
Backgrounds:
Decreased urine output (UO) is associated with adverse outcomes in certain patients, but this effect in patients admitted for cardiovascular diseases is still unproven. Moreover, the relationship between increased UO and prognosis is also unclear.
Objective:
To investigate the relationship between decreased or increased UO and outcomes in patients with the cardiovascular intensive care unit (CICU).
Methods:
This study was a retrospective cohort analysis based on the medical information mart for intensive care III (MIMIC-III) database. The patients' data were extracted from the Beth Israel Deaconess Medical Center (Boston, MA) between 2001 and 2012. With the initial 24-h UO range from 0.5 to 1.0 ml/kg/h as the reference, participants were divided into the several groups. The primary outcome was 30-day mortality. The secondary outcomes were 90-day mortality, ICU mortality, hospital mortality, use of mechanical ventilation (MV), and vasopressor agents in the first 24-h of ICU. The association between UO and mortality was assessed by multivariable logistic regression.
Results:
A total of 13,279 patients admitted to CICU were included. Low UO (< 0.5 ml/kg/h) was strongly associated with 30-day mortality (unadjusted OR = 3.993, 95% CI: 3.447-4.625, p < 0.001), and very high UO (≥ 2.0 ml/kg/h) was also a significantly risk factor for 30-day mortality (Unadjusted OR = 2.069, 95% CI: 1.701-2.516, p < 0.001) compared with the reference. The same effects also were shown in the multivariable logistic regression, adjusted by age, gender, vital signs, common comorbidities, and use of diuretics, with an adjusted OR of 2.023 (95% CI: 1.693-2.417, p < 0.001) for low UO and 1.771 (95% CI: 1.389-2.256, p < 0.001) for very high UO. Moreover, both decreased UO and increased UO were risk factors for 90-day mortality, ICU mortality, hospital mortality, use of MV and vasopressor agents.
Conclusion:
The decreased and increased UO both were significantly associated with short-term mortality, the relationship between UO and mortality was U-shape rather than linear.


Related Concept Videos
 01:22
Acute Kidney Injury I: Introduction
 01:22
Acute Kidney Injury VI: Nursing Management
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
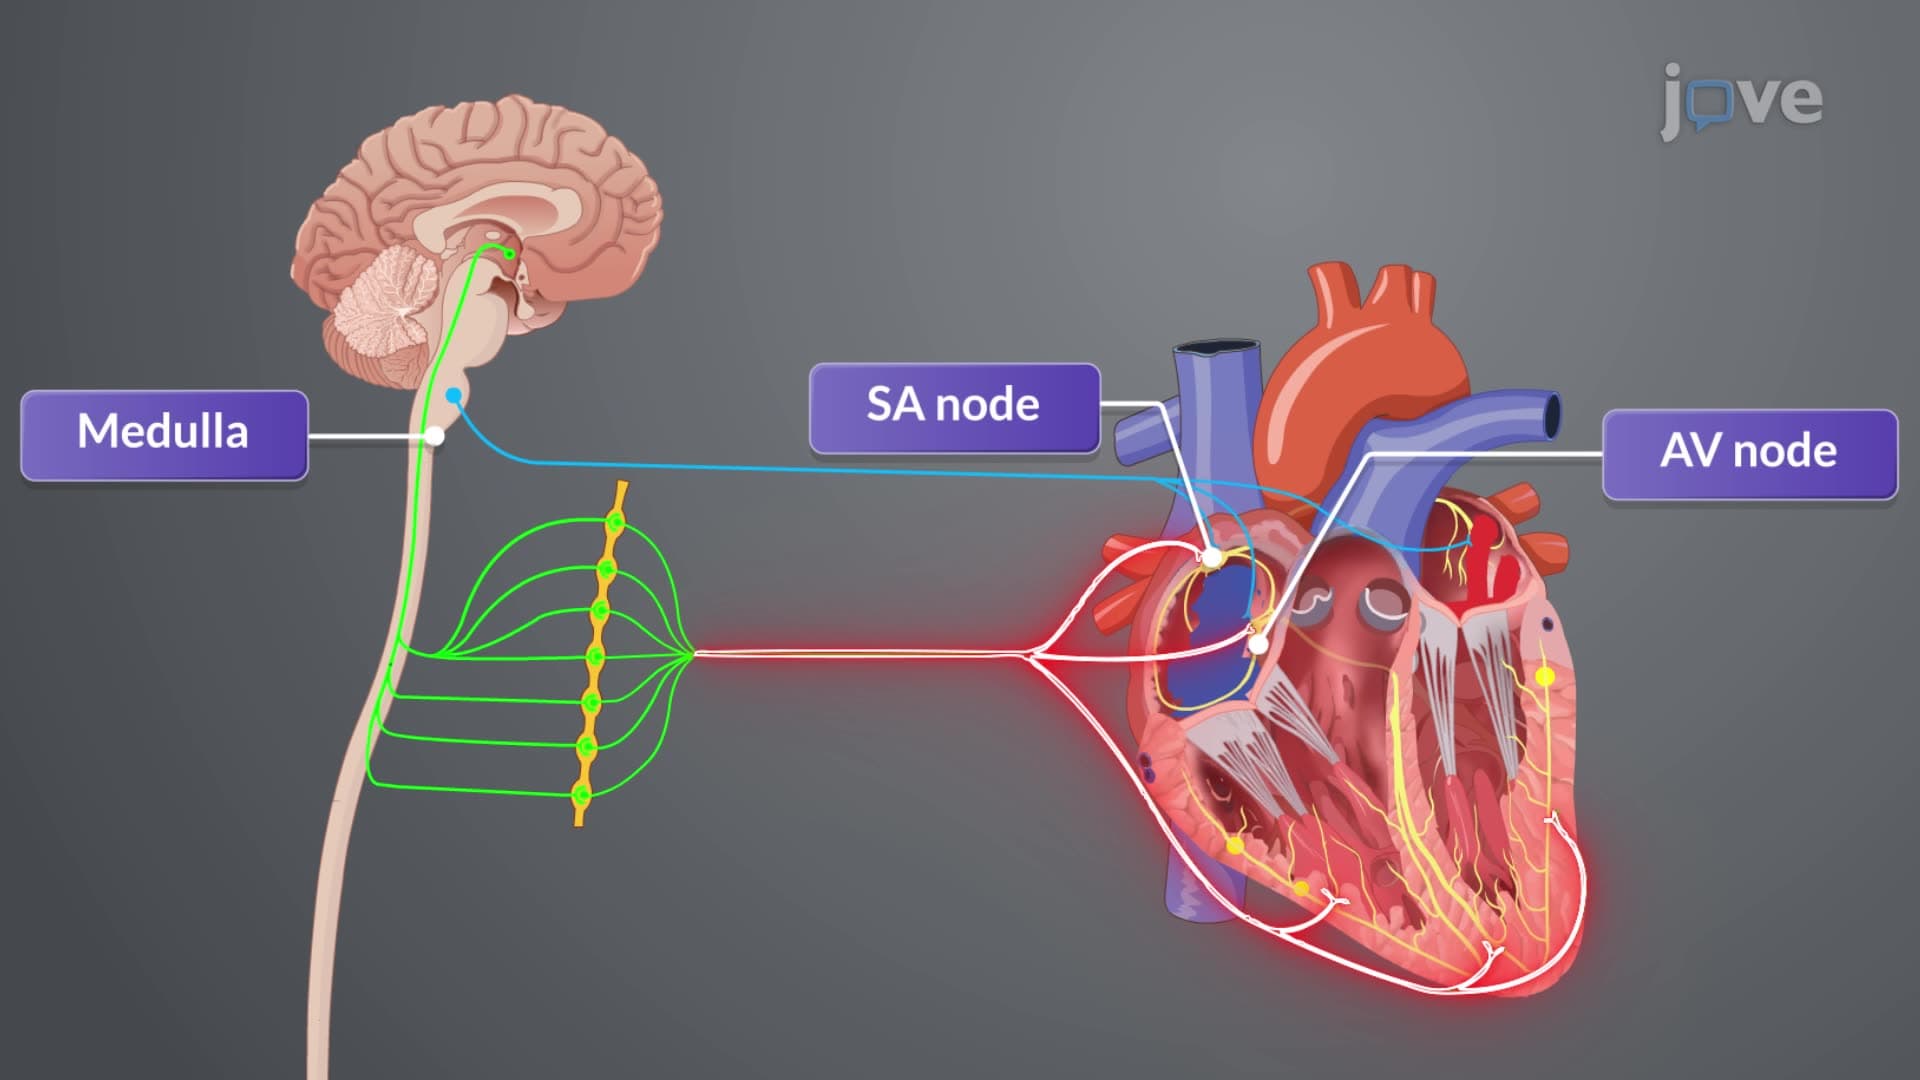
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention