Related Experiment Video
Updated: Sep 23, 2025


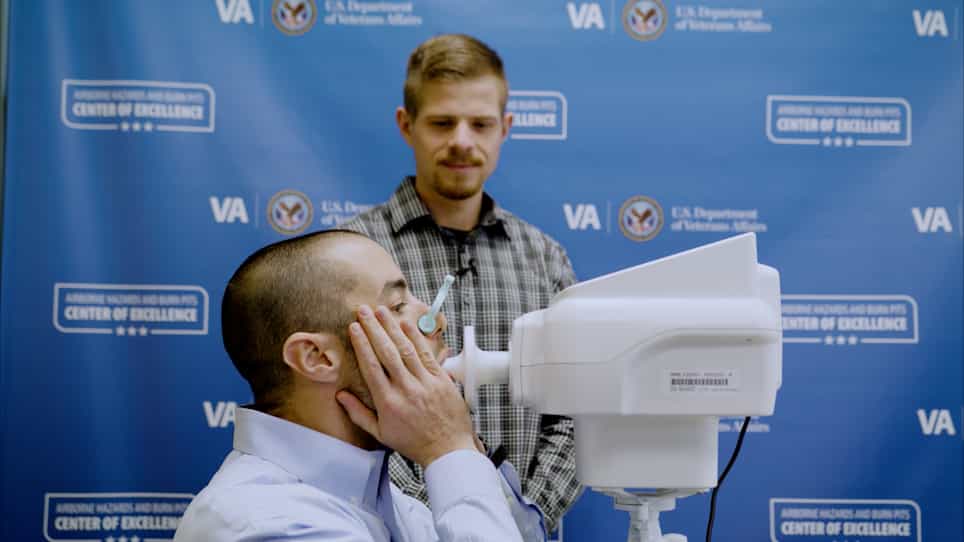
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Reference values for respiratory sinusoidal oscillometry in children aged 3 to 17 years
Francine M Ducharme1,2,3, Anna Smyrnova3, Christiane C Lawson3
1Department of Pediatrics, Faculty of Medicine, University of Montreal, Montreal, Québec, Canada.

Insights
New oscillometry devices can now measure respiratory function in children. This study developed device-specific reference equations for the multiethnic Canadian pediatric population, improving diagnostic accuracy for respiratory diseases.
Area of Science:
- Pediatric Pulmonology
- Respiratory Physiology
- Medical Devices
Background:
- Commercially available oscillometry devices can quantify respiratory function during tidal breathing.
- Reference equations are currently lacking for the multiethnic Canadian pediatric population.
Purpose of the Study:
- To develop reference equations for respiratory system resistance (Rrs) and reactance (Xrs), area under the reactance curve (AX), and resonant frequency (Fres) in healthy Canadian children.
- To assess the feasibility of obtaining valid and reproducible oscillometry measurements in children.
- To derive device-specific reference equations due to observed differences between devices.
Main Methods:
- Prospective cross-sectional study of 299 healthy children aged 3-17 years.
- Measurements of Rrs, Xrs, AX, and Fres using Resmon Pro and tremoflo C-100 devices.
- Data analyzed using linear regression and Generalized Additive Models to derive prediction equations and confidence intervals.
Main Results:
- Valid and reproducible oscillometry measurements were obtained in 98% of children.
- Standing height was the strongest predictor of respiratory function parameters; sex, age, BMI, and ethnicity had no significant effect.
- Significant differences were observed between the two devices, necessitating device-specific equations.
Conclusions:
- Oscillometry measurements are feasible and reproducible in children aged 3 years and older.
- Device-specific reference equations were successfully derived for the multiethnic Canadian pediatric population.
- These equations will aid in the accurate assessment of pediatric respiratory function.
Background:
New oscillometry devices allowing quantification of respiratory function using tidal breathing are commercially available, but reference equations are lacking for the multiethnic Canadian pediatric population.
Methods:
We conducted a prospective cross-sectional study of healthy children carefully selected for absence of asthma, atopy, tobacco smoke, obesity, prematurity, and recent respiratory infection. Triplicate measures were obtained of respiratory system resistance (Rrs) and reactance (Xrs), area under the reactance curve (AX) and resonant frequency (Fres) on four signals, whose testing order was randomized: two signals on the Resmon Pro Full (8 Hz and 5-11-19 Hz) and two signals on the tremoflo C-100 (5-37 Hz and 7-41 Hz). Feasibility was defined as the ability to obtain valid reproducible results. Prediction equations and 95% confidence intervals were derived for whole- and within-breath Rrs and Xrs and for AX and Fres, using linear regression or Generalized Additive Models for Location, Scale and Shape.
Results:
Of 306 children randomized, valid and reproducible results on ≥1 signal were obtained in 299 (98%) multiethnic (69% Caucasians: 8% Black: 23% Others) children aged 3-17 years, 91-189 cm tall. Standing height was the strongest predictor with no significant effect of sex, age, body mass index or ethnicity. Significant within-patient differences were observed between Resmon Pro and tremoflo C-100 measurements, justifying the derivation of device-specific reference equations.
Conclusion:
Valid reproducible oscillometry measurements are highly feasible in children aged 3 years and older. Device-specific reference equations, valid for our multiethnic population, are derived.
Related Concept Videos
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:22
Respiratory Volumes and Capacities
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...