

Stabilization of unstable reentrant atrial tachycardias via fractionated continuous electrical activity ablation
Eduardo Franco1, Cristina Lozano Granero2, Roberto Matía2
1Arrhythmia Unit, Cardiology Department, University Hospital Ramón y Cajal, Madrid, Spain. efranco@academiamir.com.

Background:
Unstable reentrant atrial tachycardias (ATs) (i.e., those with frequent circuit modification or conversion to atrial fibrillation) are challenging to ablate. We tested a strategy to achieve arrhythmia stabilization into mappable stable ATs based on the detection and ablation of rotors.
Methods:
All consecutive patients from May 2017 to December 2019 were included. Mapping was performed using conventional high-density mapping catheters (IntellaMap ORION, PentaRay NAV, or Advisor HD Grid). Rotors were subjectively identified as fractionated continuous (or quasi-continuous) electrograms on 1-2 adjacent bipoles, without dedicated software. In patients without detectable rotors, sites with spatiotemporal dispersion (i.e., all the cycle length comprised within the mapping catheter) plus non-continuous fractionation on single bipoles were targeted. Ablation success was defined as conversion to a stable AT or sinus rhythm.
Results:
Ninety-seven patients with reentrant ATs were ablated. Of these, 18 (18.6%) presented unstable circuits. Thirteen (72%) patients had detectable rotors (median 2 [1-3] rotors per patient); focal ablation was successful in 12 (92%). In the other 5 patients, 17 sites with spatiotemporal dispersion were identified and targeted. Globally, and excluding 1 patient with spontaneous AT stabilization, ablation success was achieved in 16/17 patients (94.1%). One-year freedom from atrial arrhythmias was similar between patients with unstable and stable ATs (66.7% vs. 65.8%, p = 0.946).
Conclusions:
Most unstable reentrant ATs show detectable rotors, identified as sites with single-bipole fractionated quasi-continuous signals, or spatiotemporal dispersion plus non-continuous fractionation. Ablation of these sites is highly effective to stabilize the AT or convert it into sinus rhythm.
More Related Videos
 10:46
Non-fluoroscopic Catheter Tracking for Fluoroscopy Reduction in Interventional Electrophysiology
Published on: May 26, 2015
 12:45
Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
Related Concept Videos
 01:25
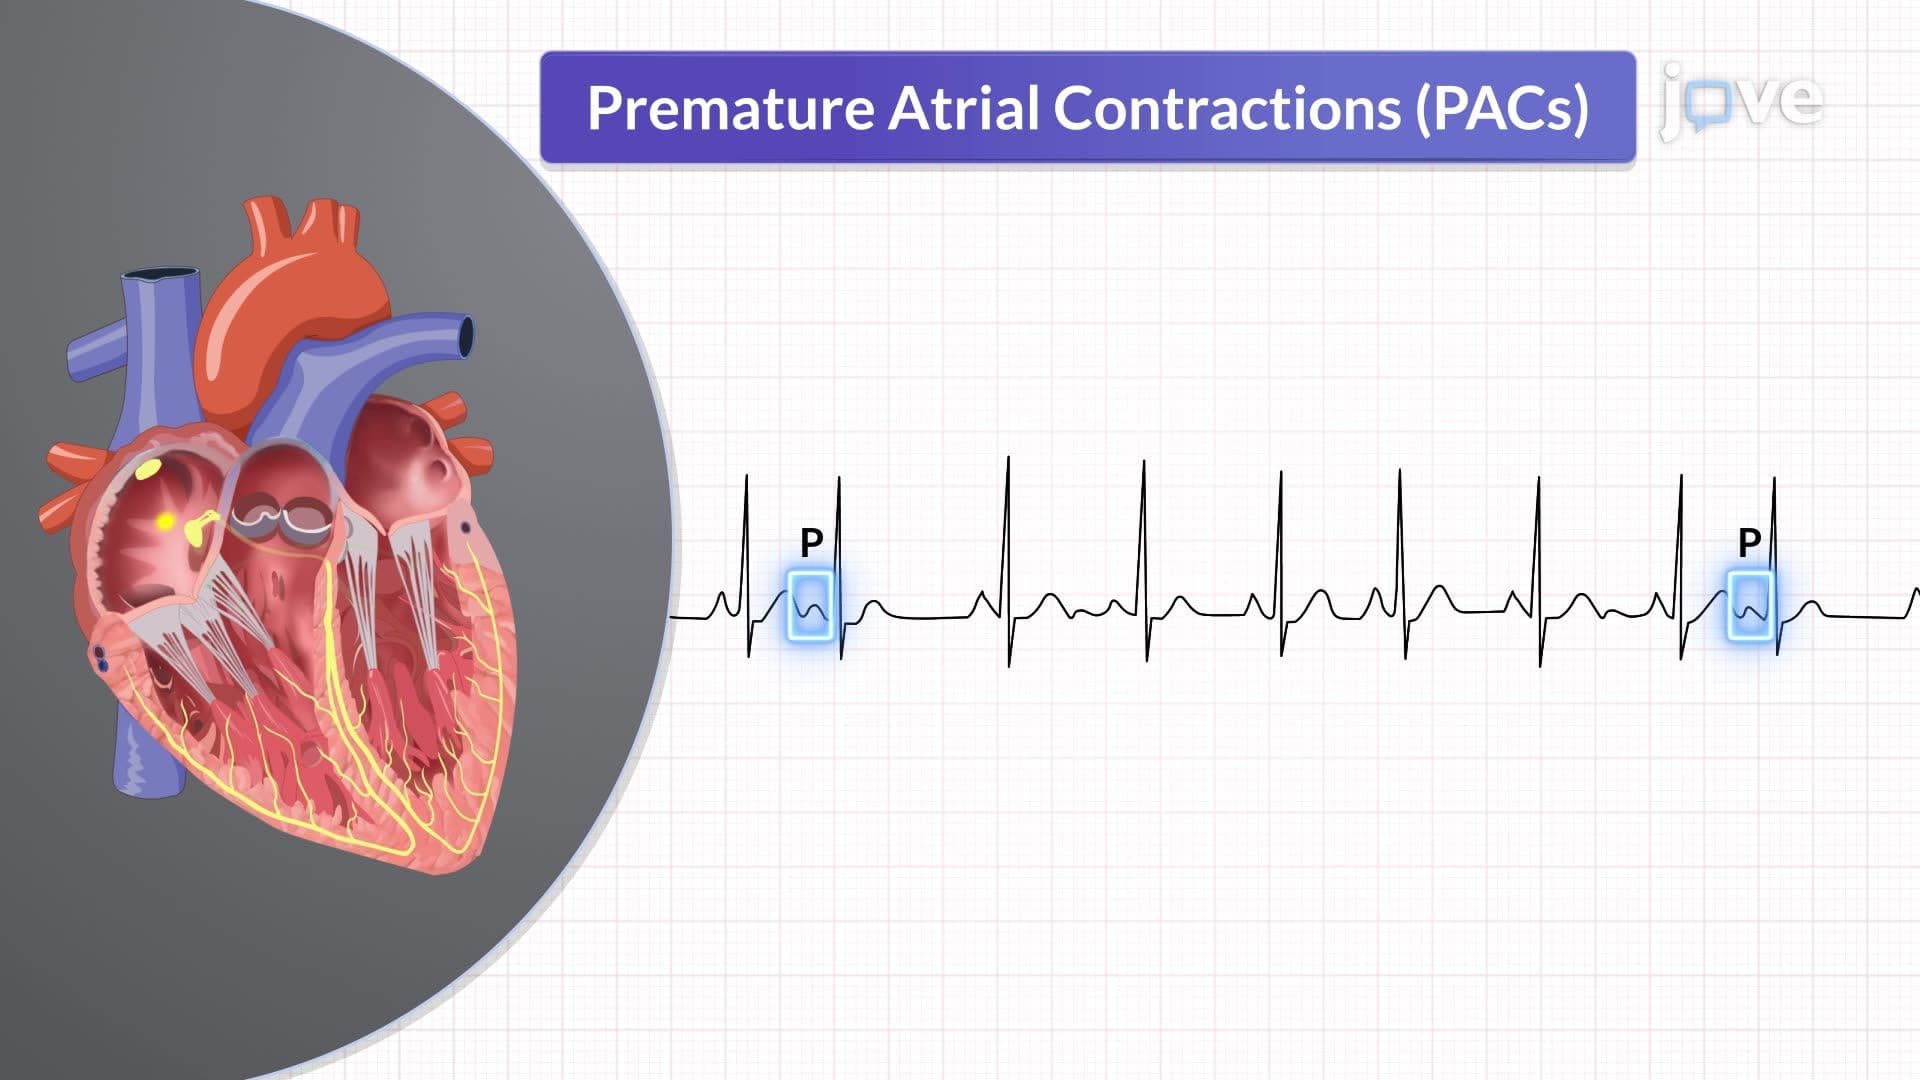
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:25
Dysrhythmias VI: Management of Dysrhythmias
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:29
Dysrhythmias III: Characteristics of Dysrhythmias
 01:28
Mechanism of Cardiac Arrhythmias