Related Experiment Video
Updated: Sep 22, 2025


Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Impact of Stress Hyperglycemia on No-Reflow Phenomenon in Patients with ST Elevation Myocardial Infarction Undergoing
Mohamed Khalfallah1, Dina A Maria1, Amany Allaithy1
1Cardiovascular department, Tanta University, EG.

Insights
Stress hyperglycemia significantly increases the risk of no-reflow after primary percutaneous coronary intervention (PPCI). This finding is crucial for identifying patients with acute myocardial infarction who may experience poorer outcomes.
Area of Science:
- Cardiology
- Endocrinology
- Interventional Cardiology
Background:
- Stress hyperglycemia is common in acute myocardial infarction (AMI) and linked to adverse prognosis.
- Identifying prognostic factors for no-reflow before primary percutaneous coronary intervention (PPCI) is critical.
Purpose of the Study:
- To investigate the impact of stress hyperglycemia on the no-reflow phenomenon.
- To compare the incidence of stress hyperglycemia and no-reflow in diabetic versus non-diabetic patients undergoing PPCI for ST-elevation myocardial infarction (STEMI).
Main Methods:
- A study of 480 patients with STEMI undergoing PPCI.
- Patients were categorized into normal flow (TIMI 3) and no-reflow (TIMI 0-2) groups.
- Clinical outcomes, including mortality and major adverse cardiac events, were analyzed.
Main Results:
- Stress hyperglycemia occurred in 14.8% of non-diabetic and 22.2% of diabetic patients.
- The incidence of no-reflow was significantly higher in patients with stress hyperglycemia (13.5%).
- Independent predictors of no-reflow included stress hyperglycemia (OR 3.247), Killip class >1 (OR 1.893), and cardiogenic shock (OR 3.778).
Conclusions:
- Stress hyperglycemia is associated with an increased incidence of the no-reflow phenomenon post-PPCI.
- Stress hyperglycemia, elevated Killip class, and cardiogenic shock are independent predictors of no-reflow.
Background:
Stress hyperglycemia is a common finding during acute myocardial infarction and associated with poor prognosis. To reduce the occurrence of no-reflow, prognostic factors must be identified before primary percutaneous coronary intervention (PPCI). Our objective was to investigate the impact of stress hyperglycemia in non-diabetic and diabetic patients on no-reflow phenomenon after PPCI.
Methods:
The study comprised 480 patients with ST elevation myocardial infarction (STEMI) who were managed by PPCI. Patients were classified into two groups according to thrombolysis in myocardial infarction (TIMI) flow grade: Group I (Patients with normal flow, TIMI 3 flow) and Group II (Patients with no-reflow, TIMI 0-2 flow). Patients were analyzed for clinical outcomes including mortality and major adverse cardiac events.
Results:
Incidence of stress hyperglycemia was 14.8% in non-diabetic patients and 22.2% in diabetic patients; the incidence of no-reflow phenomenon was 13.5% and no-reflow was significantly higher in patients with stress hyperglycemia. Multivariate regression analysis identified the independent predictors of no-reflow phenomenon: stress hyperglycemia OR 3.247 (CI95% 1.656-6.368, P = 0.001), Killip class >1 OR 1.893 (CI95% 1.004-3.570, P = 0.049) and cardiogenic shock OR 3.778 (CI95% 1.458-9.790, P = 0.006).
Conclusion:
Stress hyperglycemia was associated with higher incidence of no-reflow phenomenon. The independent predictors of no-reflow were stress hyperglycemia, Killip class >1 and cardiogenic shock.
More Related Videos
 05:41
Left Anterior Descending Coronary Artery Ligation for Ischemia-Reperfusion Research: Model Improvement via Technical Modifications and Quality Control
Published on: December 16, 2022
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
Related Concept Videos
 01:30
Acute Coronary Syndrome I: Introduction
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:27
Psychoneuroimmunology: Cardiovascular Disease
A key area of focus in PNI is the relationship between stress and coronary...
 01:26
Exercise Stress Test
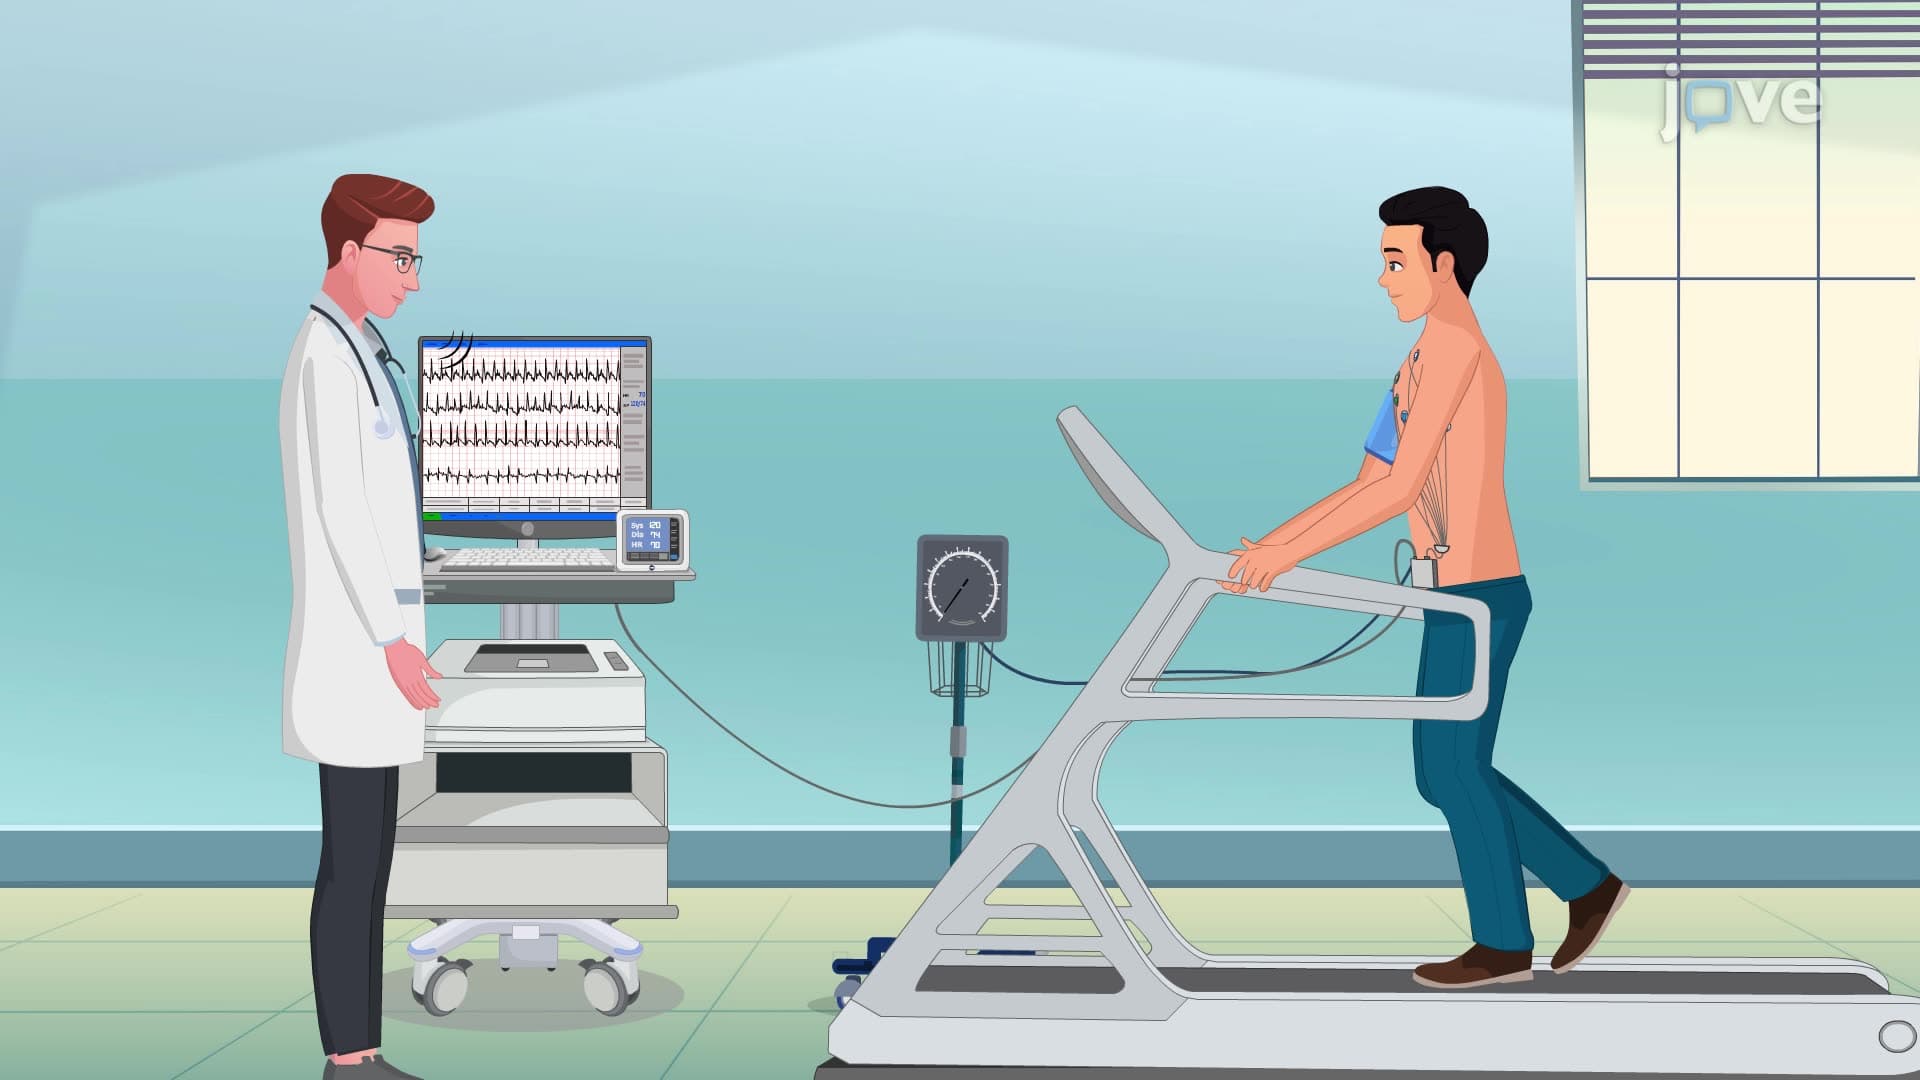
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes