Related Experiment Video
Updated: Sep 22, 2025


Quantification of Levator Ani Hiatus Enlargement by Magnetic Resonance Imaging in Males and Females with Pelvic Organ Prolapse
Published on: April 17, 2019
Relationships between pelvic nerves and levator ani muscle for posterior sacrocolpopexy: an anatomic study
Grégoire Rocher1,2, Henri Azaïs1,2, Amélia Favier1,2
1Assistance Publique des Hôpitaux de Paris (AP-HP), Department of Gynecological and Breast Surgery and Oncology, Pitié-Salpêtrière University Hospital, 75013, Paris, France.

Background:
The placement of posterior mesh during pelvic organ prolapse laparoscopic surgery has been incriminated as responsible for postoperative adverse outcomes such as digestive symptoms, chronic pelvic pain, and sexual dysfunction. These complications may be related to neural injuries that occur during the fixation of the posterior mesh on the levator ani muscle.
Objectives:
The aim of our study was to describe the course of the autonomic nerves of the pararectal space and their anatomical relationship with the posterior mesh fixation zone on the levator ani muscle.
Study Design:
Twenty hemi-pelvis specimens from 10 fresh female cadavers were dissected. We measured the distance between the posterior mesh fixation zone on the levator ani, and the nearest point of adjacent structures: the hypogastric nerve, inferior hypogastric plexus, uterosacral ligament, uterine artery, and ureter. Measurements were repeated starting from the inferior hypogastric plexus.
Results:
Nerve fibers of the inferior hypogastric plexus spread out systematically above the superior aspect of the levator ani muscle. Median distance from the posterior mesh fixation zone and the inferior hypogastric plexus was around 2.8 (range 2.1-3.5) cm.
Conclusions:
The inferior hypogastric plexus lies above the superior aspect of the levator ani muscle. A short distance between the posterior mesh fixation zone on the levator ani muscle and inferior hypogastric plexus could explain in part postoperative digestive symptoms. These observations support the development of nerve-sparing procedures for posterior mesh placement in the context of pelvic organ prolapse repair and suggest that postoperative complications could be improved by changing the fixation zone.


Related Concept Videos
 01:26
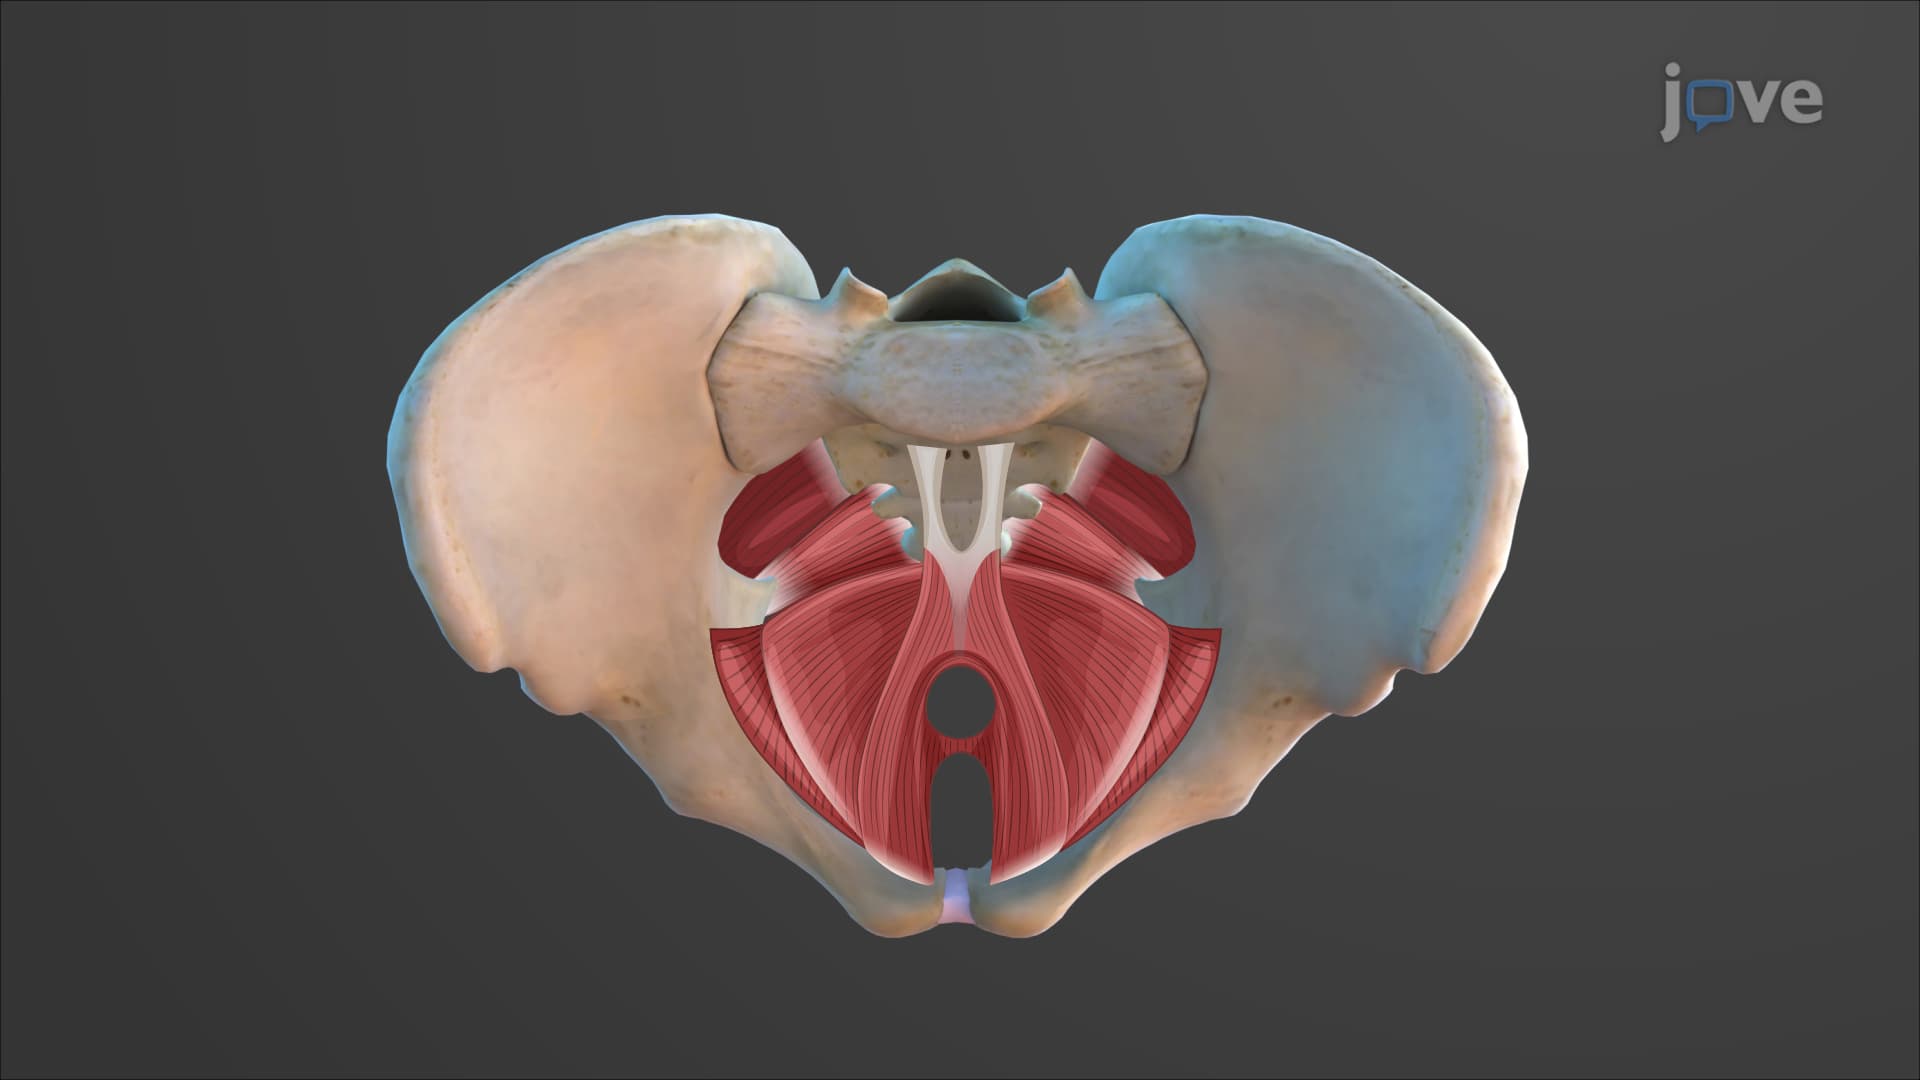
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:21
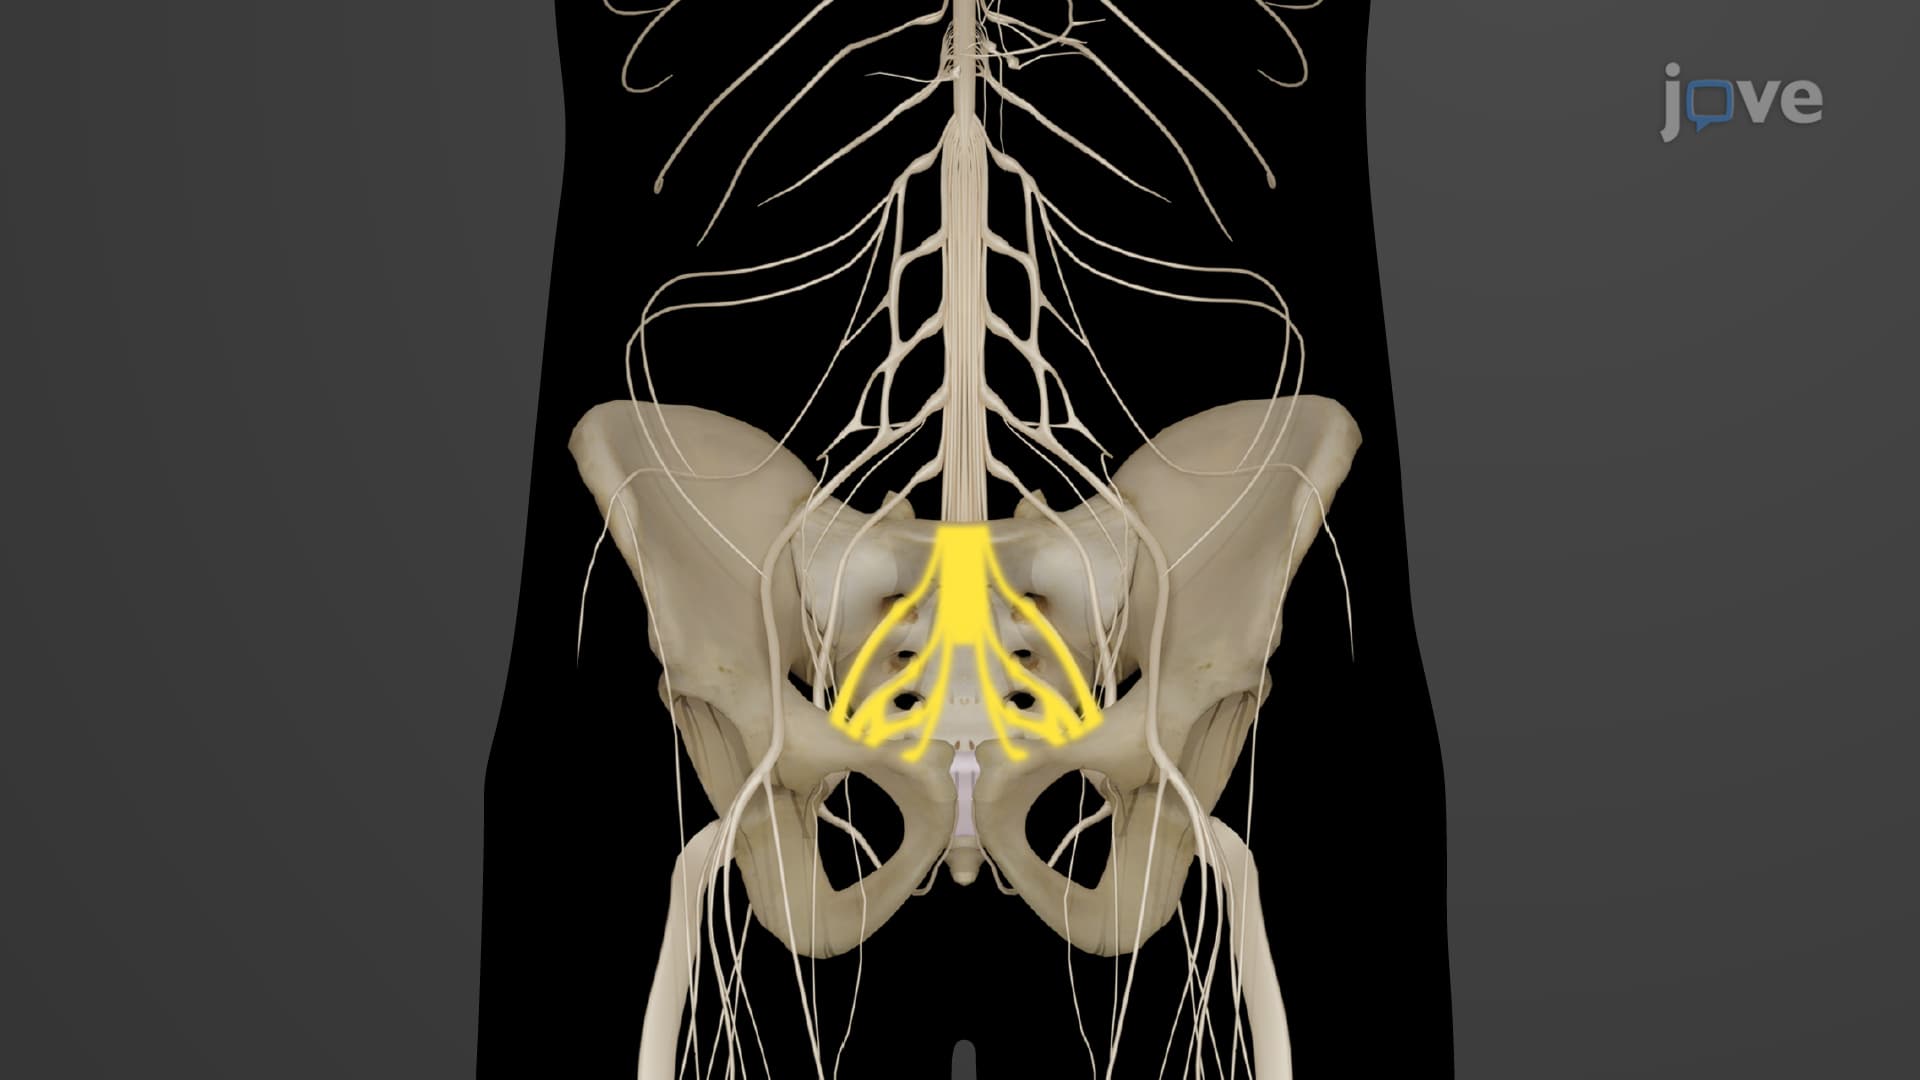
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:23
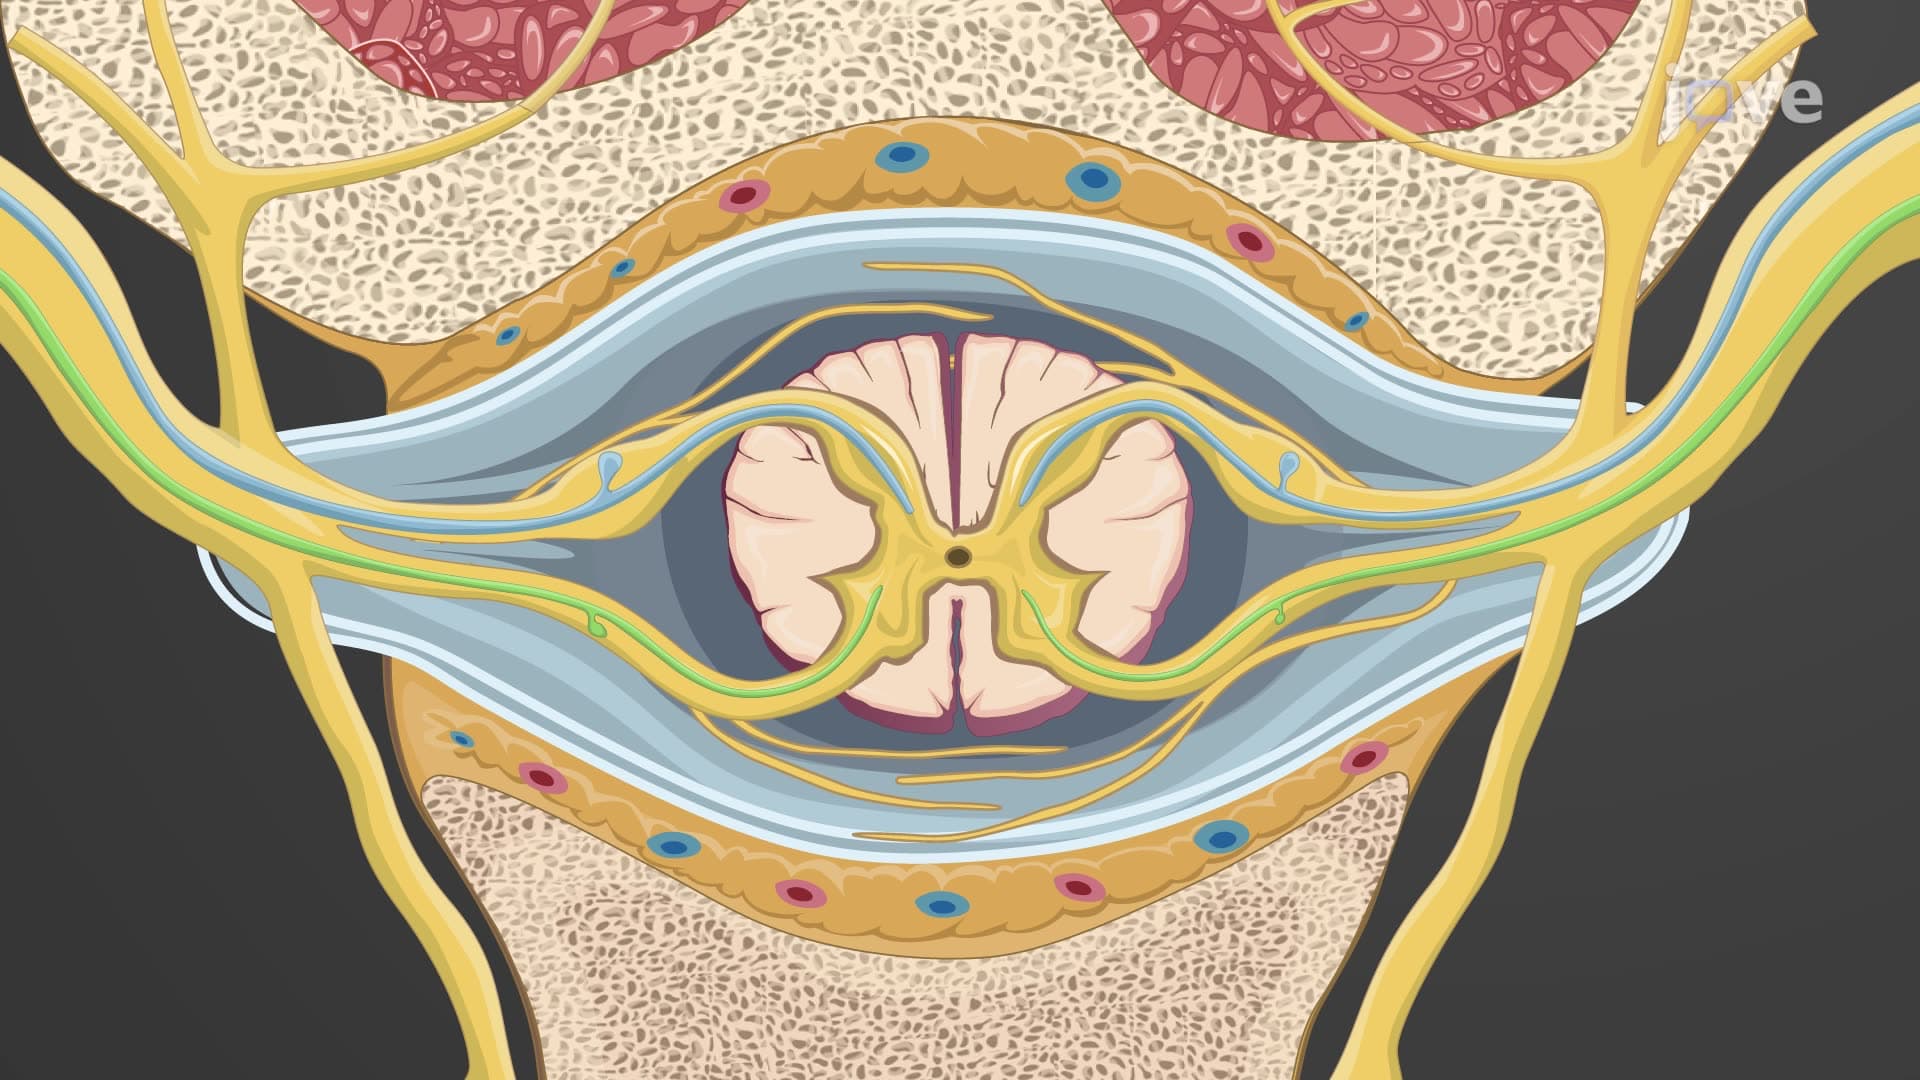
Spinal Nerves: Anatomy
There are 31 bilateral pairs of spinal nerves, each emerging from the spinal cord through the intervertebral foramina—openings between adjacent vertebrae. These nerves are...
 01:19
Abdominal Regions and Quadrants
The simpler quadrants approach, which is more commonly used in medicine, subdivides the cavity with one horizontal and one vertical line that intersects at the patient's umbilicus (navel). The four...