Related Experiment Video
Updated: Sep 22, 2025

Assessment and Evaluation of the High Risk Neonate: The NICU Network Neurobehavioral Scale
Published on: August 25, 2014
Payer-Related Sources of Variation in Febrile Infant Management Before and After a National Practice Standardization
Adrienne G DePorre1,2,3, Troy Richardson1,4, Russell McCulloh5
1Division of Hospital Medicine, Department of Pediatrics, Children's Mercy Kansas City, Kansas City, Missouri.

Objectives:
Sources of variation within febrile infant management are incompletely described. In 2016, a national standardization quality improvement initiative, Reducing Excessive Variation in Infant Sepsis Evaluations (REVISE) was implemented. We sought to: (1) describe sociodemographic factors influencing laboratory obtainment and hospitalization among febrile infants and (2) examine the association of REVISE on any identified sources of practice variation.
Methods:
We included febrile infants ≤60 days of age evaluated between December 1, 2015 and November 30, 2018 at Pediatric Health Information System-reporting hospitals. Patient demographics and hospital characteristics, including participation in REVISE, were identified. Factors associated with variation in febrile infant management were described in relation to the timing of the REVISE initiative.
Results:
We identified 32 572 febrile infants in our study period. Pre-REVISE, payer-type was associated with variation in laboratory obtainment and hospitalization. Compared with those with private insurance, infants with self-pay (adjusted odds ratio [aOR] 0.43, 95% confidence interval [95% CI] 0.22-0.5) or government insurance (aOR 0.67, 95% CI 0.60-0.75) had lower odds of receiving laboratories, and self-pay infants had lower odds of hospitalization (aOR 0.38, 95% CI 0.28-0.51). Post-REVISE, payer-related disparities in care remained. Disparities in care were not associated with REVISE participation, as the interaction of time and payer was not statistically different between non-REVISE and REVISE centers for either laboratory obtainment (P = .09) or hospitalization (P = .67).
Conclusions:
Payer-related care inequalities exist for febrile infants. Patterns in disparities were similar over time for both non-REVISE and REVISE-participating hospitals. Further work is needed to better understand the role of standardization projects in reducing health disparities.

Related Concept Videos
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever:
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:26
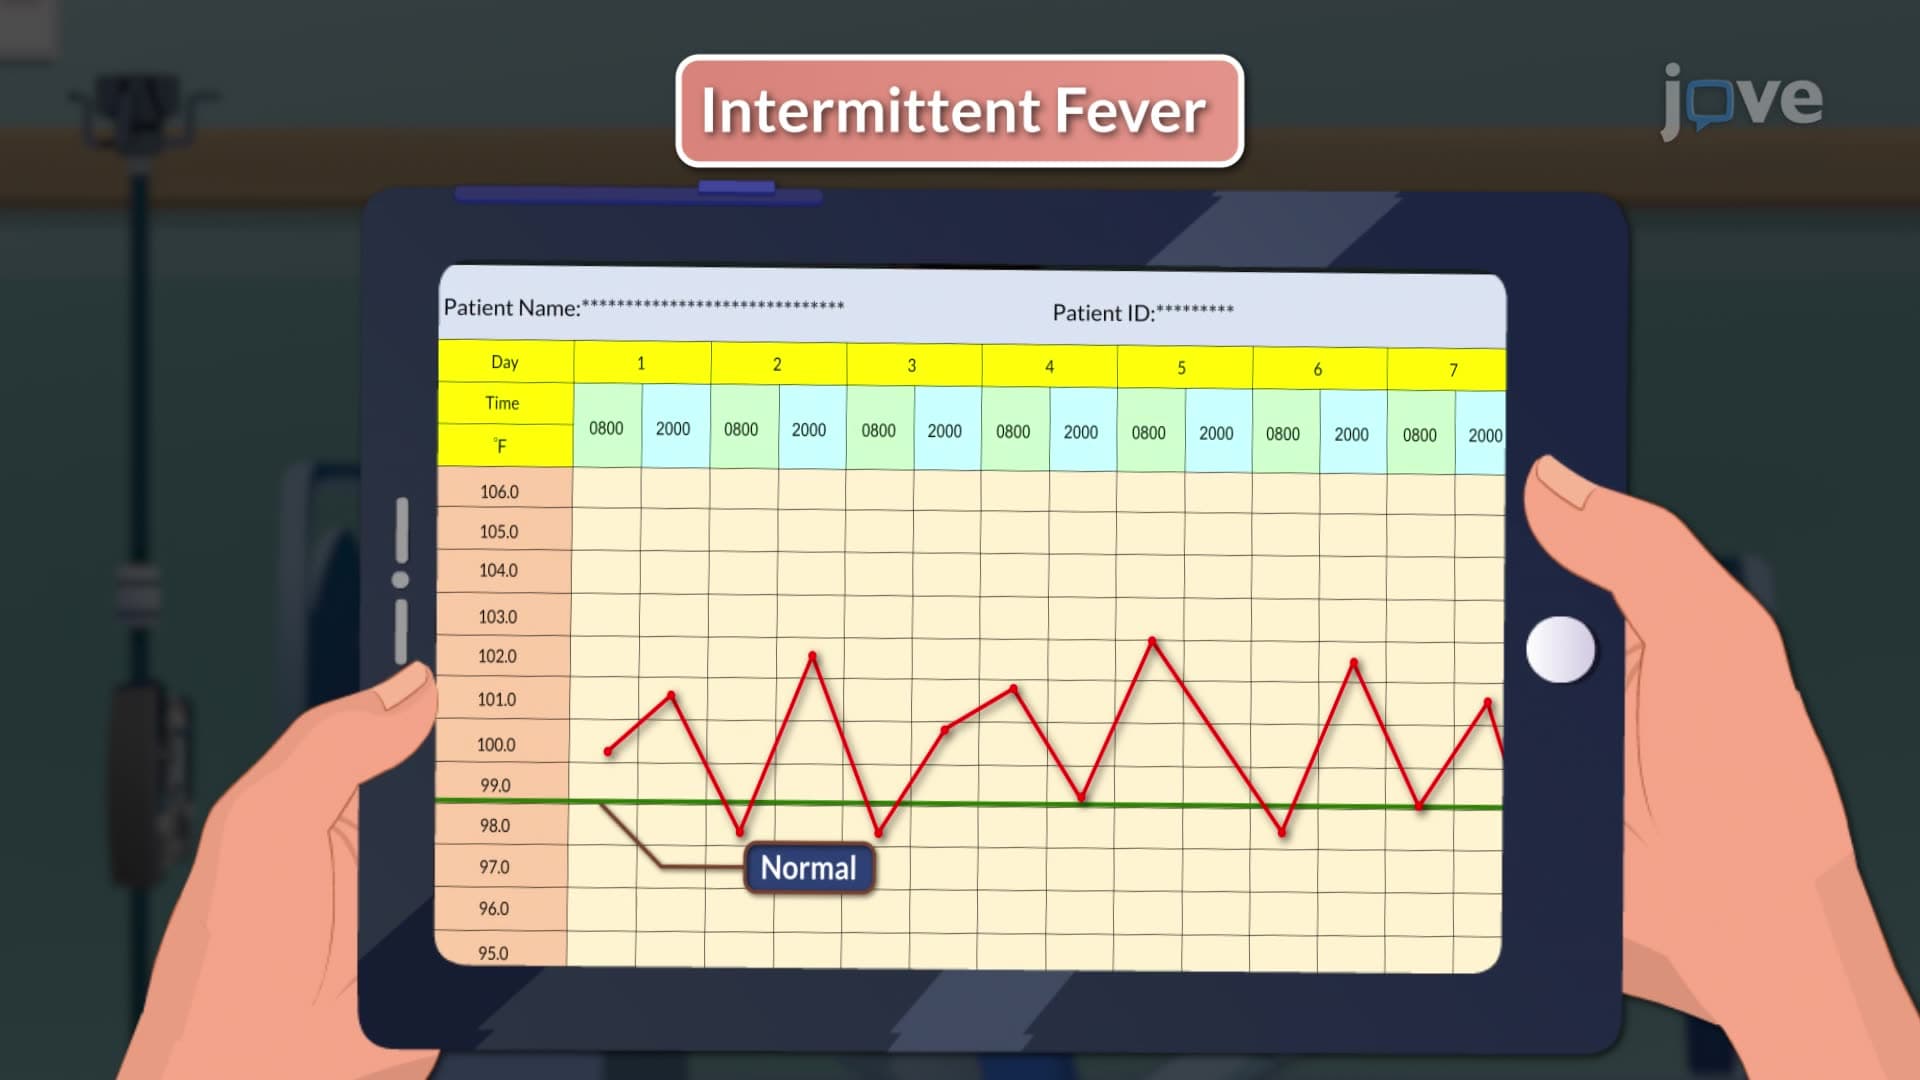
Patterns of Fever
 01:14
Temperature Measurement Sites
Oral: When assessing oral temperature, the thermometer tip should be placed under the tongue in the posterior sublingual pocket. It offers accurate readings and can be...
 01:19
Guidelines For Measuring Vital Signs
Before taking a patient's vital signs, a nurse would consider and assess the patient's comfort level and ensure appropriate equipment is available.
 01:19
Standards of Care II