Related Experiment Video
Updated: Sep 22, 2025
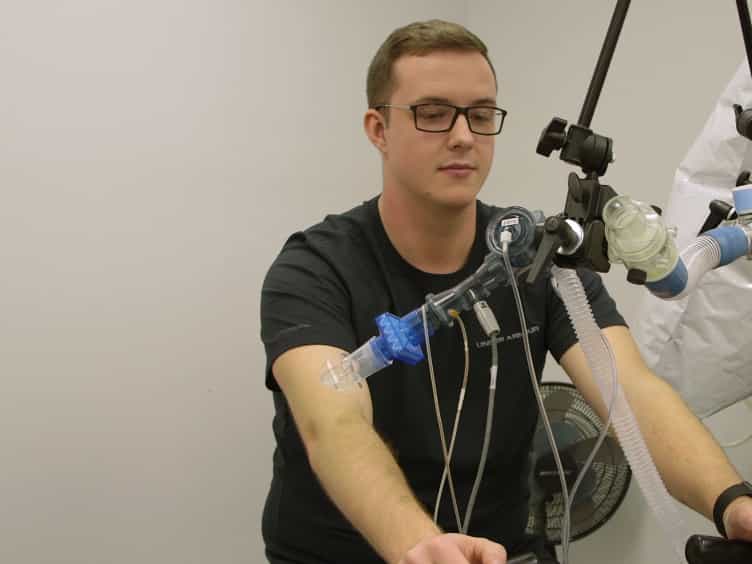

Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Excess ventilation and exertional dyspnoea in heart failure and pulmonary hypertension
J Alberto Neder1, Devin B Phillips2, Denis E O'Donnell2
1Clinical Exercise Physiology and Respiratory Investigation Unit, Division of Respiratory and Critical Care Medicine, Dept of Medicine, Queen's University and Kingston Health Sciences Centre, Kingston, ON, Canada alberto.neder@queensu.ca.

Abstract:
Increased ventilation relative to metabolic demands, indicating alveolar hyperventilation and/or increased physiological dead space (excess ventilation), is a key cause of exertional dyspnoea. Excess ventilation has assumed a prominent role in the functional assessment of patients with heart failure (HF) with reduced (HFrEF) or preserved (HFpEF) ejection fraction, pulmonary arterial hypertension (PAH) and chronic thromboembolic pulmonary hypertension (CTEPH). We herein provide the key pieces of information to the caring physician to 1) gain unique insights into the seeds of patients' shortness of breath and 2) develop a rationale for therapeutically lessening excess ventilation to mitigate this distressing symptom. Reduced bulk oxygen transfer induced by cardiac output limitation and/or right ventricle-pulmonary arterial uncoupling increase neurochemical afferent stimulation and (largely chemo-) receptor sensitivity, leading to alveolar hyperventilation in HFrEF, PAH and small-vessel, distal CTEPH. As such, interventions geared to improve central haemodynamics and/or reduce chemosensitivity have been particularly effective in lessening their excess ventilation. In contrast, 1) high filling pressures in HFpEF and 2) impaired lung perfusion leading to ventilation/perfusion mismatch in proximal CTEPH conspire to increase physiological dead space. Accordingly, 1) decreasing pulmonary capillary pressures and 2) mechanically unclogging larger pulmonary vessels (pulmonary endarterectomy and balloon pulmonary angioplasty) have been associated with larger decrements in excess ventilation. Exercise training has a strong beneficial effect across diseases. Addressing some major unanswered questions on the link of excess ventilation with exertional dyspnoea under the modulating influence of pharmacological and nonpharmacological interventions might prove instrumental to alleviate the devastating consequences of these prevalent diseases.
More Related Videos
Related Concept Videos
 01:25
Hyperpnea and Hyperventilation
 01:26
Heart Failure III: Clinical Manifestations
 01:17
Pulmonary Cycle: Exhalation
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:17
Pathophysiology of Heart Failure