Related Experiment Video
Updated: Sep 21, 2025
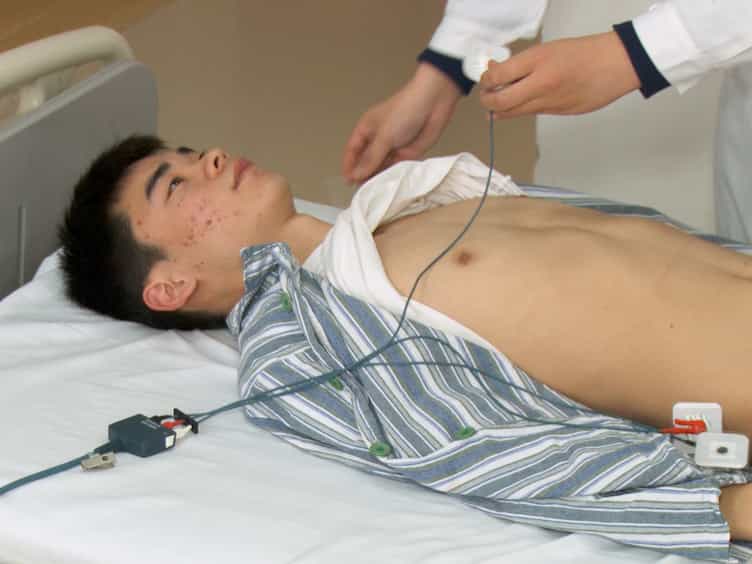

Measuring the Carotid to Femoral Pulse Wave Velocity Cf-PWV to Evaluate Arterial Stiffness
Published on: May 3, 2018
Comparing self-reported and measured hypertension and hypercholesterolaemia at standard and more stringent diagnostic
Angela J Burvill1, Kevin Murray2, Matthew W Knuiman2
1Medical School, University of Western Australia, Crawley, WA, Australia. angela.burvill@health.wa.gov.au.

Background:
Population health behaviour and risk factor surveys most often rely on self-report but there is a lack of studies assessing the validity of self-report using Australian data. This study investigates the sensitivity, specificity and agreement of self-reported hypertension and hypercholesterolaemia with objective measures at standard and more stringent diagnostic thresholds; and factors associated with sensitivity and specificity of self-report at different thresholds.
Methods:
This study was a secondary analysis of a representative community-based cross-sectional sample of 5,092 adults, aged 45-69 years, residing in Busselton, Western Australia, surveyed in 2010-2015. Participants completed a self-administered questionnaire. Blood pressure and serum cholesterol levels were measured.
Results:
At currently accepted diagnostic thresholds, sensitivities of self-reported hypertension and hypercholesterolaemia were 58.5% and 39.6%, respectively and specificities were >90% for both. Agreement using Cohen's kappa coefficient was 0.562 and 0.223, respectively. At two higher diagnostic thresholds, sensitivities of self-reported hypertension and hypercholesterolaemia improved by an absolute 14-23% and 15-25%, respectively and specificities remained >85%. Agreement was substantial for hypertension (kappa = 0.682-0.717) and moderate for hypercholesterolaemia (kappa = 0.458-0.533). Variables that were independently associated with higher sensitivity and lower specificity of self-report were largely consistent across thresholds and included increasing age, body mass index, worse self-rated health, diabetes and family history of hypertension.
Conclusions:
Self-reported hypertension and hypercholesterolaemia often misclassify individuals' objective status and underestimate objective prevalences, at standard diagnostic thresholds, which has implications for surveillance studies that rely on self-reported data. Self-reports of hypertension, however, may be reasonable indicators of those with blood pressures ≥160/100 mmHg or those taking anti-hypertensive medications. Self-reported hypercholesterolaemia data should be used with caution at all thresholds.
More Related Videos

Related Concept Videos
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:28
Hypertension I: Introduction
 01:15
Assessment of blood pressure in brachial artery(one-step method)
Prepare for the Procedure:
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:23
Assessment of blood pressure in brachial artery(two-step method)
 01:18
Hypertension and Regulation of Blood Pressure