Related Experiment Video
Updated: Sep 21, 2025
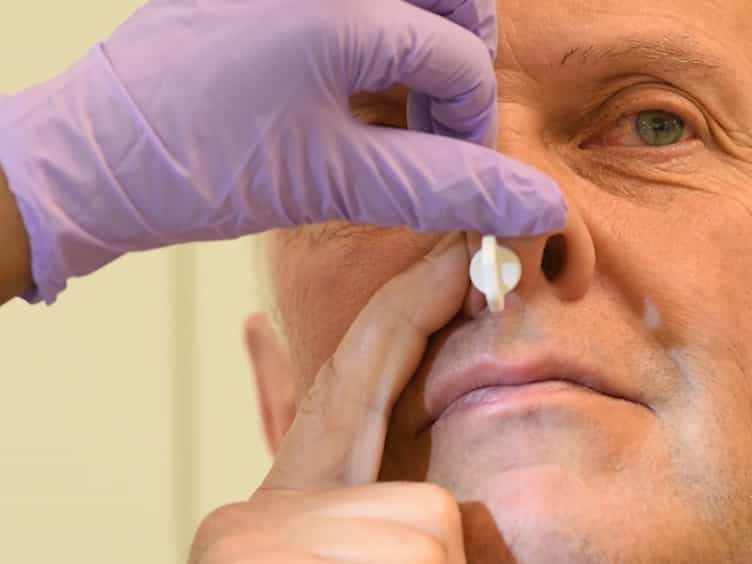
Absorption of Nasal and Bronchial Fluids: Precision Sampling of the Human Respiratory Mucosa and Laboratory Processing of Samples
Published on: January 21, 2018
C-Reactive Protein Levels in Children with Acute Bronchiolitis
Hasan M Isa1, Abdulrahman D Mohroofi2, Fatema N Alkhan3
1Consultant Pediatric Gastroenterologist, Pediatric Department, Salmaniya Medical Complex, Arabian Gulf University, Manama, Bahrain.

Insights
Most children with acute bronchiolitis have elevated C-reactive protein (CRP) levels, but this does not indicate bacterial coinfection. High CRP in bronchiolitis is linked to older age, fever, cough, and lower hemoglobin, not bacterial presence.
Area of Science:
- Pediatrics
- Infectious Diseases
- Clinical Chemistry
Background:
- Acute bronchiolitis is a common pediatric respiratory infection.
- Elevated C-reactive protein (CRP) is often observed, but its correlation with bacterial coinfection is unclear.
- Understanding factors associated with high CRP can aid clinical decision-making.
Purpose of the Study:
- To investigate the relationship between CRP levels and bacterial coinfection in children with acute bronchiolitis.
- To identify clinical and laboratory factors associated with elevated CRP in this population.
- To assess antibiotic prescription patterns in acute bronchiolitis.
Main Methods:
- Retrospective analysis of 229 pediatric patients diagnosed with acute bronchiolitis.
- Measurement of CRP levels, detection of respiratory syncytial virus (RSV) and other viral pathogens.
- Assessment for bacterial coinfection, chest X-ray findings, and antibiotic use.
- Statistical analysis to correlate CRP levels with clinical factors and outcomes.
Main Results:
- A high proportion of patients (72.9%) had elevated CRP levels.
- Bacterial coinfection was confirmed in 17.6% of patients.
- Mean CRP was higher in RSV-negative patients compared to RSV-positive patients (P=0.042).
- High CRP was associated with older age (P<0.0001), fever (P<0.0001), cough (P=0.002), and lower hemoglobin (P<0.0001).
- Fever and hemoglobin level were independent factors associated with high CRP (P=0.016 and P=0.002, respectively).
- Antibiotics were prescribed to 78.1% of patients, despite a predominantly viral etiology.
Conclusions:
- Elevated CRP in acute bronchiolitis is common but does not reliably indicate bacterial coinfection.
- Clinical factors like fever and hemoglobin levels, rather than bacterial coinfection, are associated with high CRP.
- High rates of antibiotic prescription for viral bronchiolitis warrant review and potential de-escalation strategies.
Results:
Of 287 patients, 229 (79.2%) were included. 132 (57.6%) were males. Median presentation age was 3.7 (interquartile range (IQR), 1.27-12.33) months. Median CRP level was 10.4 (IQR, 2.8-35.1) mg/L. CRP was high in 167 (72.9%) patients. 17.6% (33/187 patients) had confirmed bacterial coinfection. Respiratory syncytial virus (RSV) was detected in 84 (36.7%) patients. Mean CRP level was higher in RSV-negative compared to RSV-positive patients, 31.3 ± 44.3 versus 21.5 ± 27.7 mg/L, respectively (P = 0.042). Respiratory viral serology profile was positive in 34.7% (17/49 patients). 66.9% (107/160 patients) had positive chest X-ray. Antibiotics were used in 78.1% (179/227 patients). Thirteen (5.7%) patients required intensive care, five (2.2%) had surgical intervention, four (1.8%) required endotracheal intubation, and four (1.8%) died. Patients with high CRP were older at presentation (P < 0.0001) and had more fever (P < 0.0001) and cough (P = 0.002), but lower hemoglobin level (P < 0.0001) compared to those with normal CRP. Fever (P = 0.016) and hemoglobin level (P = 0.002) were independent factors.
Conclusion:
Most children with acute bronchiolitis had high rate of elevated CRP values that did not correlate with the rate of bacterial coinfection. High CRP levels were found in older children, those presented with more fever and cough, and had a lower hemoglobin level despite that those factors were previously reported to be associated with disease severity and bacterial coinfection. This study also showed a high overall rate of antibiotic prescriptions in mostly viral disease.
More Related Videos
 05:31
Noninvasive Sampling of Mucosal Lining Fluid for the Quantification of In Vivo Upper Airway Immune-mediator Levels
Published on: August 7, 2017
 09:01
An In vitro Model to Study Immune Responses of Human Peripheral Blood Mononuclear Cells to Human Respiratory Syncytial Virus Infection
Published on: December 10, 2013
Related Concept Videos
 01:30
Pneumonia III: Complications and Assessment
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...
 01:17
Pulmonary Cycle: Exhalation
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:23
Acute Respiratory Failure-IV
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies