Related Experiment Video
Updated: Sep 20, 2025


Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Clinical Spectrum of Hereditary Hypophosphatemic Rickets With Hypercalciuria (HHRH)
Julian Stürznickel1,2, Fiona Heider1, Alena Delsmann1
1Department of Osteology and Biomechanics, University Medical Center Hamburg-Eppendorf, Hamburg, Germany.

Hereditary hypophosphatemic rickets with hypercalciuria (HHRH) represents an FGF23-independent disease caused by biallelic variants in the solute carrier family 34-member 3 (SLC34A3) gene. HHRH is characterized by chronic hypophosphatemia and an increased risk for nephrocalcinosis and rickets/osteomalacia, muscular weakness, and secondary limb deformity. Biochemical changes, but no relevant skeletal changes, have been reported for heterozygous SLC34A3 carriers. Therefore, we assessed the characteristics of individuals with biallelic and monoallelic SLC34A3 variants. In 8 index patients and 5 family members, genetic analysis was performed using a custom gene panel. The skeletal assessment comprised biochemical parameters, areal bone mineral density (aBMD), and bone microarchitecture. Pathogenic SLC34A3 variants were revealed in 7 of 13 individuals (2 homozygous, 5 heterozygous), whereas 3 of 13 carried monoallelic variants of unknown significance. Whereas both homozygous individuals had nephrocalcinosis, only one displayed a skeletal phenotype consistent with HHRH. Reduced to low-normal phosphate levels, decreased tubular reabsorption of phosphate (TRP), and high-normal to elevated values of 1,25-OH2 -D3 accompanied by normal cFGF23 levels were revealed independently of mutational status. Interestingly, individuals with nephrocalcinosis showed significantly increased calcium excretion and 1,25-OH2 -D3 levels but normal phosphate reabsorption. Furthermore, aBMD Z-score <-2.0 was revealed in 4 of 8 heterozygous carriers, and HR-pQCT analysis showed a moderate decrease in structural parameters. Our findings highlight the clinical relevance also of monoallelic SLC34A3 variants, including their potential skeletal impairment. Calcium excretion and 1,25-OH2 -D3 levels, but not TRP, were associated with nephrocalcinosis. Future studies should investigate the effects of distinct SLC34A3 variants and optimize treatment and monitoring regimens to prevent nephrocalcinosis and skeletal deterioration. © 2022 The Authors. Journal of Bone and Mineral Research published by Wiley Periodicals LLC on behalf of American Society for Bone and Mineral Research (ASBMR).
Hereditary hypophosphatemic rickets with hypercalciuria (HHRH) represents an FGF23-independent disease caused by biallelic variants in the solute carrier family 34-member 3 (SLC34A3) gene. HHRH is characterized by chronic hypophosphatemia and an increased risk for nephrocalcinosis and rickets/osteomalacia, muscular weakness, and secondary limb deformity. Biochemical changes, but no relevant skeletal changes, have been reported for heterozygous SLC34A3 carriers. Therefore, we assessed the characteristics of individuals with biallelic and monoallelic SLC34A3 variants. In 8 index patients and 5 family members, genetic analysis was performed using a custom gene panel. The skeletal assessment comprised biochemical parameters, areal bone mineral density (aBMD), and bone microarchitecture. Pathogenic SLC34A3 variants were revealed in 7 of 13 individuals (2 homozygous, 5 heterozygous), whereas 3 of 13 carried monoallelic variants of unknown significance. Whereas both homozygous individuals had nephrocalcinosis, only one displayed a skeletal phenotype consistent with HHRH. Reduced to low-normal phosphate levels, decreased tubular reabsorption of phosphate (TRP), and high-normal to elevated values of 1,25-OH2 -D3 accompanied by normal cFGF23 levels were revealed independently of mutational status. Interestingly, individuals with nephrocalcinosis showed significantly increased calcium excretion and 1,25-OH2 -D3 levels but normal phosphate reabsorption. Furthermore, aBMD Z-score <-2.0 was revealed in 4 of 8 heterozygous carriers, and HR-pQCT analysis showed a moderate decrease in structural parameters. Our findings highlight the clinical relevance also of monoallelic SLC34A3 variants, including their potential skeletal impairment. Calcium excretion and 1,25-OH2 -D3 levels, but not TRP, were associated with nephrocalcinosis. Future studies should investigate the effects of distinct SLC34A3 variants and optimize treatment and monitoring regimens to prevent nephrocalcinosis and skeletal deterioration. © 2022 The Authors. Journal of Bone and Mineral Research published by Wiley Periodicals LLC on behalf of American Society for Bone and Mineral Research (ASBMR).
More Related Videos
 07:13
Two Techniques to Create Hypoparathyroid Mice: Parathyroidectomy Using GFP Glands and Diphtheria-Toxin-Mediated Parathyroid Ablation
Published on: March 14, 2017
 12:47
Spectral Karyotyping to Study Chromosome Abnormalities in Humans and Mice with Polycystic Kidney Disease
Published on: February 3, 2012
Related Concept Videos
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:21
Skeleton and Calcium Homeostasis
 01:28
Urinary Tract Calculi I: Introduction
 01:33
Introduction to Electrolytes
Role of Sodium
One...
 00:59
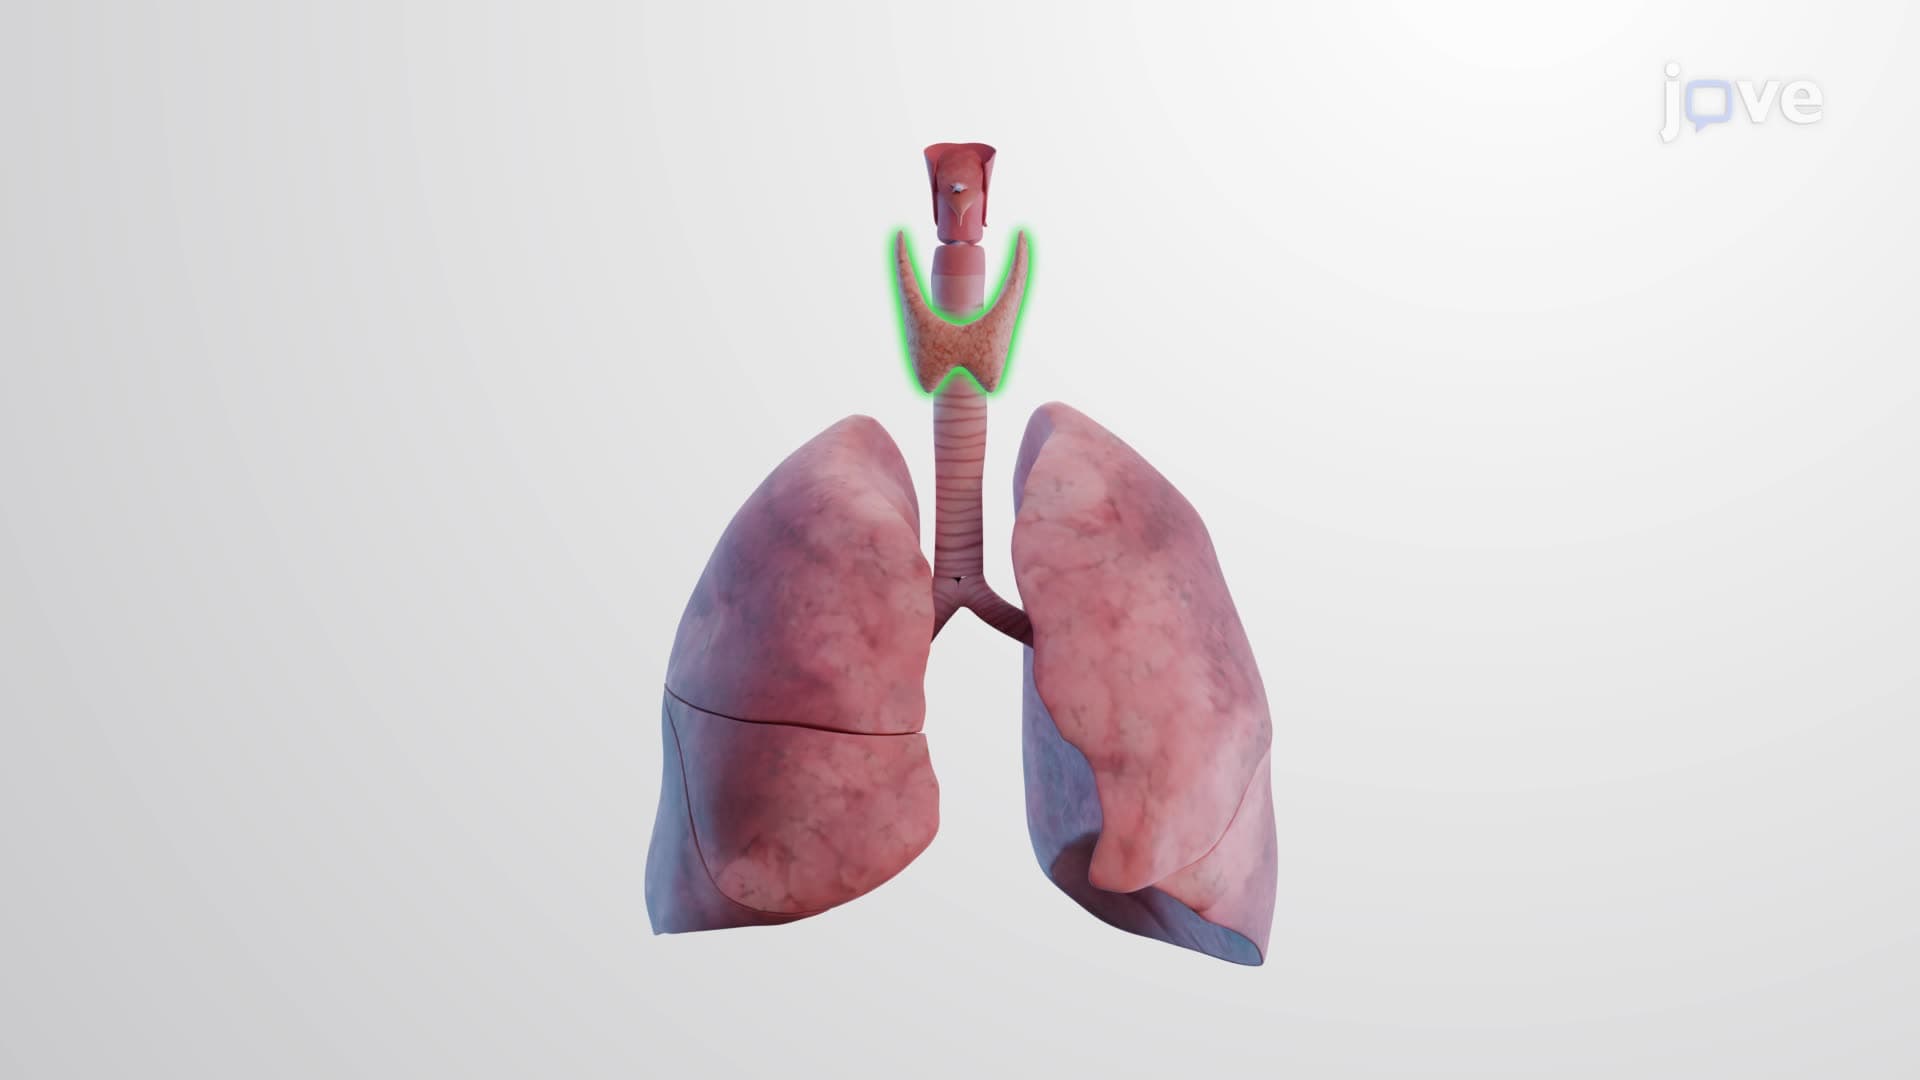
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by...