Related Experiment Video
Updated: Sep 8, 2025
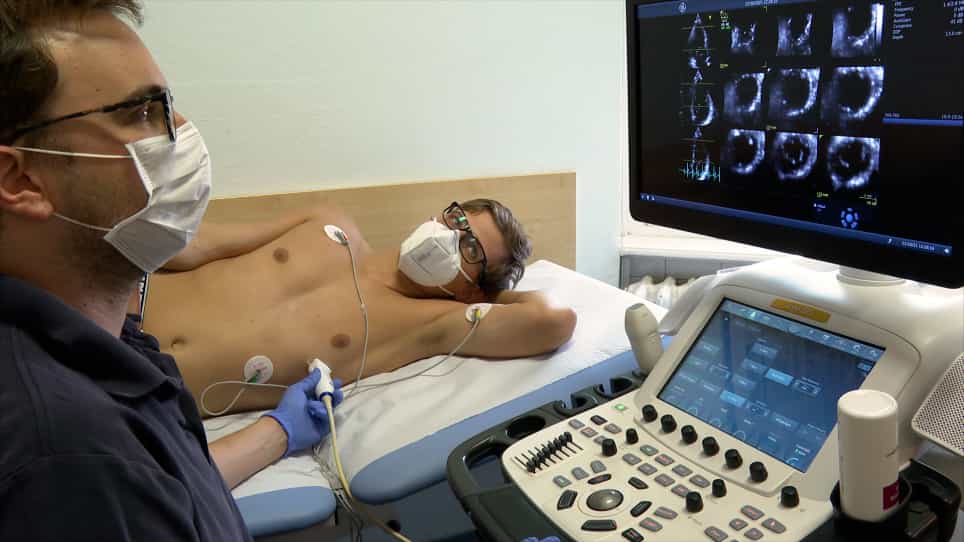

Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
Unmasking Myocardial Dysfunction in Patients Hospitalized for Community-Acquired Pneumonia Using a 4-Chamber
Moayad Khatib1, Gabby Elbaz-Greener2,3, Orna Nitzan4,5
1The Lydia and Carol Kittner, Lea and Benjamin Davidai Division of Cardiovascular Medicine and Surgery, Padeh Poriya Medical Center, Lower Galilee, Tiberias, Israel.

Abstract:
Lower respiratory infection was reported as the most common fatal infectious disease. Community-acquired pneumonia (CAP) and myocardial injury are associated; yet, true prevalence of myocardial injury is probably underestimated. We assessed the rate and severity of myocardial dysfunction in patients with CAP. Admitted patients diagnosed with CAP were prospectively recruited. All the patients had C-reactive protein (CRP), brain natriuretic peptide (BNP), and high-sensitivity cardiac troponin (hs-cTnl) tests added to their routine workup. 2D/3D Doppler echocardiography was done on a Siemens Acuson SC2000 machine ≤ 24 h of diagnosis. 3D datasets were blindly analyzed for 4-chamber volumes/strains using EchobuildR 3D-Volume Analysis prototype software, v3.0 2019, Siemens-Medical Solutions. Volume/strain parameters were correlated with admission clinical and laboratory findings. The cohort included 34 patients, median age 60 years (95% CI 55-72). The cohort included 18 (53%) patients had hypertension, 9 (25%) had diabetes mellitus, 7 (21%) were smokers, 7 (21%) had previous myocardial infarction, 4 (12%) had chronic renal failure, and 1 (3%) was on hemodialysis treatment. 2D/Doppler echocardiography findings showed normal ventricular size/function (LVEF 63 ± 9%), mild LV hypertrophy (104 ± 36 g/m2), and LA enlargement (41 ± 6 mm). 3D volumes/strains suggested bi-atrial and right ventricular dysfunction (global longitudinal strain RVGLS = - 8 ± 4%). Left ventricular strain was normal (LVGLS = - 18 ± 5%) and correlated with BNP (r = 0.40, p = 0.024). The patients with LVGLS > - 17% had higher admission blood pressure and lower SaO2 (144 ± 33 vs. 121 ± 20, systolic, mmHg, p = 0.02, and 89 ± 4 vs. 94 ± 4%, p = 0.006, respectively). hs-cTnl and CRP were not different. Using novel 3D volume/strain software in CAP patients, we demonstrated diffuse global myocardial dysfunction involving several chambers. The patients with worse LV GLS had lower SaO2 and higher blood pressure at presentation. LV GLS correlated with maximal BNP level and did not correlate with inflammation or myocardial damage markers.
More Related Videos
 07:21
Magnetic Resonance Derived Myocardial Strain Assessment Using Feature Tracking
Published on: February 12, 2011
 11:50
High-frequency High-resolution Echocardiography: First Evidence on Non-invasive Repeated Measure of Myocardial Strain, Contractility, and Mitral Regurgitation in the Ischemia-reperfused Murine Heart
Published on: July 9, 2010
