Related Experiment Video
Updated: Sep 7, 2025
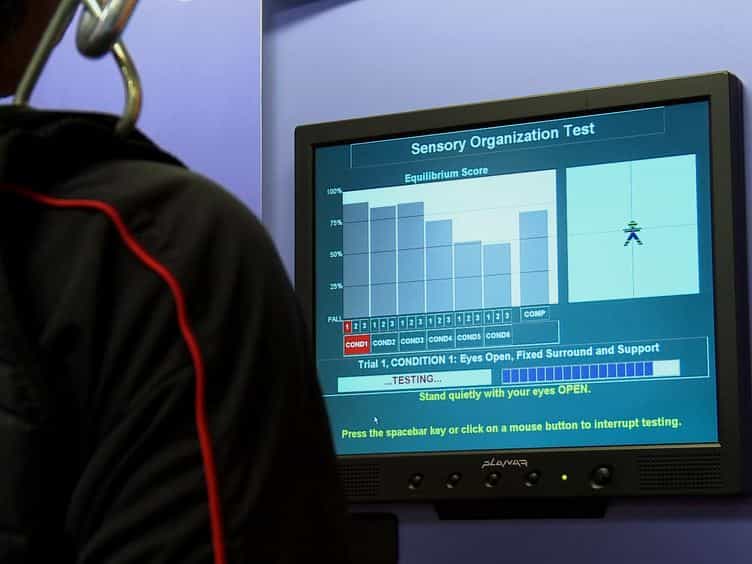
Computerized Dynamic Posturography for Postural Control Assessment in Patients with Intermittent Claudication
Published on: December 11, 2013
Underutilization of medical management of peripheral artery disease among patients with claudication undergoing lower
Ryan Howard1, Jeremy Albright2, Chloe Powell3
1Department of Surgery, University of Michigan, Ann Arbor, MI.

Insights
Optimal medical therapy for peripheral artery disease (PAD) before surgery significantly reduces postoperative risks. Patients receiving optimal treatment experienced lower mortality, myocardial infarction, and readmission rates, highlighting the importance of evidence-based care.
Area of Science:
- Vascular Surgery
- Cardiology
- Public Health
Background:
- Peripheral artery disease (PAD) management guidelines recommend medical therapy and lifestyle changes as first-line treatment.
- Evidence-based recommendations include antiplatelet, statin, antihypertensive medications, and smoking cessation/exercise.
- The adherence to these guidelines in clinical practice and its impact on surgical outcomes remain unclear.
Purpose of the Study:
- To determine the proportion of patients with claudication receiving optimal medical therapy (OMT) before elective lower extremity bypass surgery.
- To assess the association between pre-operative OMT and postoperative outcomes in patients undergoing bypass surgery for PAD.
Main Methods:
- Retrospective cohort study using a statewide surgical quality registry (2012-2021).
- Defined OMT as concurrent use of antiplatelet, statin, and ACE inhibitor/ARB (if hypertensive).
- Analyzed associations between OMT and 30-day/1-year outcomes (mortality, readmission, MI, amputation, etc.) using multivariable logistic regression.
Main Results:
- 47.6% of 3829 patients with claudication received OMT prior to bypass surgery.
- Patients on OMT had significantly lower 30-day odds of mortality (aOR 0.45) and MI (aOR 0.46).
- OMT was associated with lower 1-year odds of mortality (aOR 0.57), MI (aOR 0.48), and readmission (aOR 0.79).
Conclusions:
- Less than half of patients with PAD undergoing bypass surgery received guideline-recommended optimal medical therapy preoperatively.
- Preoperative optimal medical therapy is associated with improved postoperative outcomes, including reduced mortality, MI, and readmission.
- There is a significant opportunity to improve adherence to evidence-based PAD treatment to enhance surgical patient benefits.
Objective:
First-line treatment of peripheral artery disease (PAD) involves medical therapy and lifestyle modification. Multiple professional organizations such as the Society for Vascular Surgery and the American Heart Association/American College of Cardiology make Class I recommendations for medical management including antiplatelet, statin, antihypertensive, and cilostazol medications, as well as lifestyle therapy including exercise and smoking cessation. Although evidence supports up-front medical and lifestyle management prior to surgical intervention, it is unclear how well this occurs in contemporary clinical practice. It is also unclear whether variability in first-line treatment prior to revascularization is associated with postoperative outcomes. This study examined the proportion of patients with claudication actively receiving evidence-based therapy prior to surgery in a statewide surgical registry.
Methods:
We conducted a retrospective cohort study of adult patients undergoing elective open lower extremity bypass for claudication from 2012 to 2021 within a statewide surgical quality registry. The primary exposure was optimal medical therapy, defined as an antiplatelet agent, a statin, and an angiotensin-converting enzyme inhibitor or angiotensin II receptor blocker (if the patient had hypertension) on the patient's home medication list on admission for surgery, all of which are Class I recommendations. Despite also being Class I recommendations, cilostazol was not included in the primary exposure due to its highly selective use and our inability to capture intolerance and/or contraindications that are common, and lifestyle therapies were not included as they were only recorded at the time of discharge rather than preoperatively. The primary outcomes were mortality, hospital readmission, amputation, wound complication, myocardial infarction (MI), non-patent bypass, and non-independent ambulatory status at 30 days and 1 year after surgery. Multivariable logistic regression was performed to estimate the association of receiving optimal vs non-optimal medical therapy.
Results:
A total of 3829 patients with claudication underwent bypass surgery during the study period, with a mean age of 64.8 years (standard deviation, 9.8 years); 2690 (70.3%) were males, and 1873 (48.9%) were current smokers. Of the patients, 1822 (47.6%) were on optimal medical therapy prior to surgery. Additionally, at discharge, 66.5% of smokers received referral to smoking cessation therapy, and 54.1% of patients received referral to exercise therapy. In a multivariable logistic regression, compared with patients not on optimal medical therapy, patients on optimal medical therapy prior to surgery had lower 30-day odds of mortality (adjusted odds ratio [aOR], 0.45; 95% confidence interval [CI], 0.26-0.78) and MI (aOR, 0.46; 95% CI, 0.28-0.76), lower 1-year odds of mortality (aOR, 0.57; 95% CI, 0.39-0.82), MI (aOR, 0.48; 95% CI, 0.32-0.74), and lower readmission (aOR, 0.79; 95% CI, 0.64-0.96).
Conclusions:
Although medical and lifestyle management is recommended as first-line treatment for patients with PAD, only one-half of patients were on optimal medical therapy prior to surgery. Patients receiving optimal therapy had a lower risk of postoperative mortality, MI, and readmission. This suggests that not only are there significant opportunities to improve clinical utilization of evidence-based treatment of PAD, but that doing so can benefit patients postoperatively.
More Related Videos
 08:16
High-Resolution Three-Dimensional Imaging of the Footpad Vasculature in a Murine Hindlimb Gangrene Model
Published on: March 16, 2022
 07:25
Predicting Amputation using Local Circulating Mononuclear Progenitor Cells in Angioplasty-treated Patients with Critical Limb Ischemia
Published on: September 22, 2020
Related Concept Videos
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:30
Peripheral Artery Disease I: Introduction
 01:26
Angina IV: Management