Related Experiment Video
Updated: Sep 7, 2025


A Retrospective Study on Endoscopic Surgery for the Treatment of Paravertebral Abscess in Spinal Tuberculosis Patients
Published on: October 25, 2024
Isolated tuberculous orchitis presented as epididymo-orchitis: An unusual presentation of tuberculosis
Khurram Mehboob1,2, Tariq A Madani3
1Department of Nuclear Engineering, Faculty of Engineering, King Abdulaziz University, Jeddah, Saudi Arabia.

Abstract:
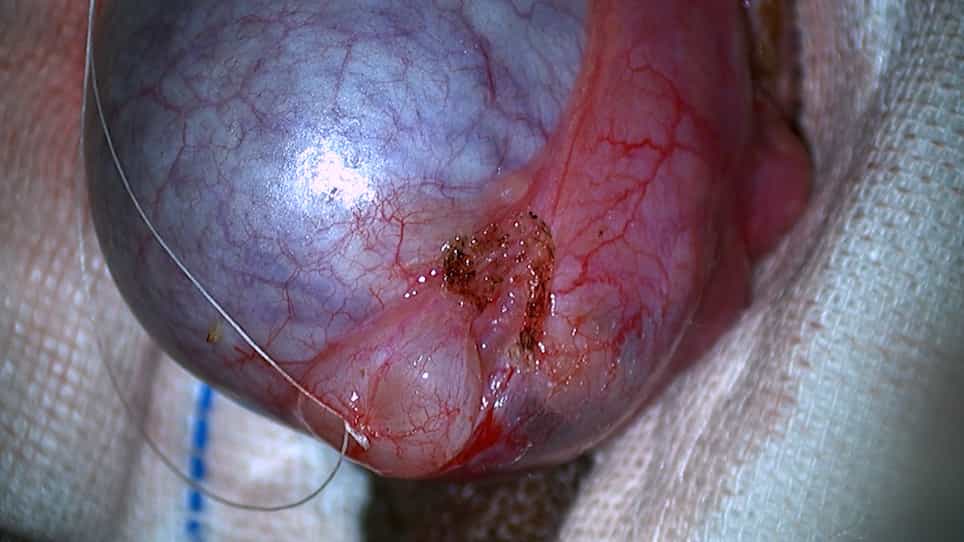
Urogenital tuberculosis (UGTB) is almost 8%-15% of the extrapulmonary site of TB of all kinds, and epididymal involvement is rarer, counted only 28% of UGTB. Isolated tuberculous epididymitis (ITE), without the inclusion of prostate or clinical evidence of renal involvement, is an even more rare entity and is challenging to diagnose. However, isolated epididymis TB presented as a huge scrotal abscess with scrotal sack involvement is exceptionally uncommon. The symptoms of such ITE resemble the epididymo-orchitis or malignant tumor, which results in misdiagnosis or delay in diagnosis. A 32-year-young man, sexually inactive, was presented with a rapid, painless scrotal growing. There was no clinical evidence for TB. Clinical examination of the genitalia revealed an enlarged right tactical with intratesticular masses (abuses) and swollen spermatic cord along with inflamed epididymitis. The radiological and laboratory shows no evidence of TB with clear chest X-rays, normal blood, and urine analysis. There were no symptoms of Mycobacterium tuberculosis during the microdot enzyme immunoassay analysis. A repeated magnetic resonance imaging and ultrasonic investigations were performed that revealed findings suggesting a chronic inflammatory process with severe abscess involving the spasmatic cord and scrotal sack, which mislead the diagnosis of epididymo-orchitis. Later, the extensive formation of superficial abscess breaches the scrotal sack. A pathological investigation of excretion and intrascrotal tissues established the diagnosis of ITE. The patient was kept on anti TB treatment medications for 12 months due to delay in diagnosis (12 weeks), continuous discharge, and severe involvement of epididymitis along with a scrotal sack and spermatic cord and had a remarkable recovery. The delayed diagnosis of ITE could lead the severe complication, which could result in surgical intervention or an orchiectomy. The first line of treatment should be the pharmacological approach for cases of epididymis TB, and surgery should be the 2nd option. A surgical procedure should be considered only in cases where the diagnosis is not established or when there is a strong clinical indication such as abscesses, cutaneous fistulas, or extensive involvement of the epididymis and testis.
More Related Videos

Related Concept Videos
 01:26
Sexually Transmitted Infections
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management