Related Experiment Video
Updated: Sep 7, 2025

Single-stage Dynamic Reanimation of the Smile in Irreversible Facial Paralysis by Free Functional Muscle Transfer
Published on: March 1, 2015
Lower Motor Neuron Facial Palsy Due to Facial Colliculus Syndrome
1Accident and Emergency Department, Changi General Hospital, Singapore, SGP.

Abstract:
In patients presenting to the Emergency Department (ED) with acute onset facial asymmetry, decision for disposition is usually based on whether it is an upper (UMN) or lower motor neuron (LMN) cranial nerve 7th (CN7) palsy. In my institution, patients with UMN CN7 palsy would require admission for further investigations to look for central causes. Those who have an isolated LMN facial nerve palsy can be managed as outpatients. A 36-year-old gentleman presented to the ED with acute vertigo and right facial weakness. He had no known cardiac risk factors. His vital signs on presentation were: Temperature 36.6℃, blood pressure 142/68mmHg, pulse rate 92/min, and oxygen saturation level (SpO2) 100% on room air. Initial neurological examination revealed a right LMN CN7 palsy without any other cranial nerve, cerebellar, or pyramidal deficits. He was given symptomatic treatment for vertigo without relief. Repeat examination subsequently showed a right conjugate gaze palsy with gaze-evoked nystagmus. There was no limb weakness or numbness. Gait was noted to be unsteady with a broad-based stance and truncal ataxia. Magnetic resonance imaging (MRI) of his brain subsequently showed an infarct affecting the right facial colliculus in the dorsal pons. In my department, this was the first case of a young patient with a stroke presenting with LMN CN7 palsy. He was initially treated for a possible peripheral cause of his vertigo as he had a history of vestibular neuronitis, but without symptomatic improvement. Patients with neurological symptoms (e.g. vertigo) not resolving with initial treatment should prompt consideration for repeat neurological examination because the patient may have evolving neurological signs, as well as consider the potential for initial anchoring/cognitive bias. In this case, the gaze palsy and cerebellar signs were only noted on subsequent examination. Presence of LMN CN7 palsy with other associated neurological signs (including other cranial nerve palsies) would warrant further imaging to look for more sinister intracranial causes, including cerebral infarcts or space-occupying lesions. This case serves to remind medical practitioners to strongly consider a central cause (e.g. stroke) for patients presenting with an LMN facial palsy, even in young patients in the absence of other vascular risk factors, especially when other neurological symptoms and signs are present.

Related Concept Videos
 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
 01:14
Muscles for Facial Expressions
 01:24
Prosopagnosia
 01:11
Direct Motor Pathways
The corticospinal tract is responsible for the voluntary movement of the limbs and trunk. It originates in the cerebral cortex of the brain and descends through the cerebrum's internal capsule and...
 01:22
Cranial Nerves: Types Part II
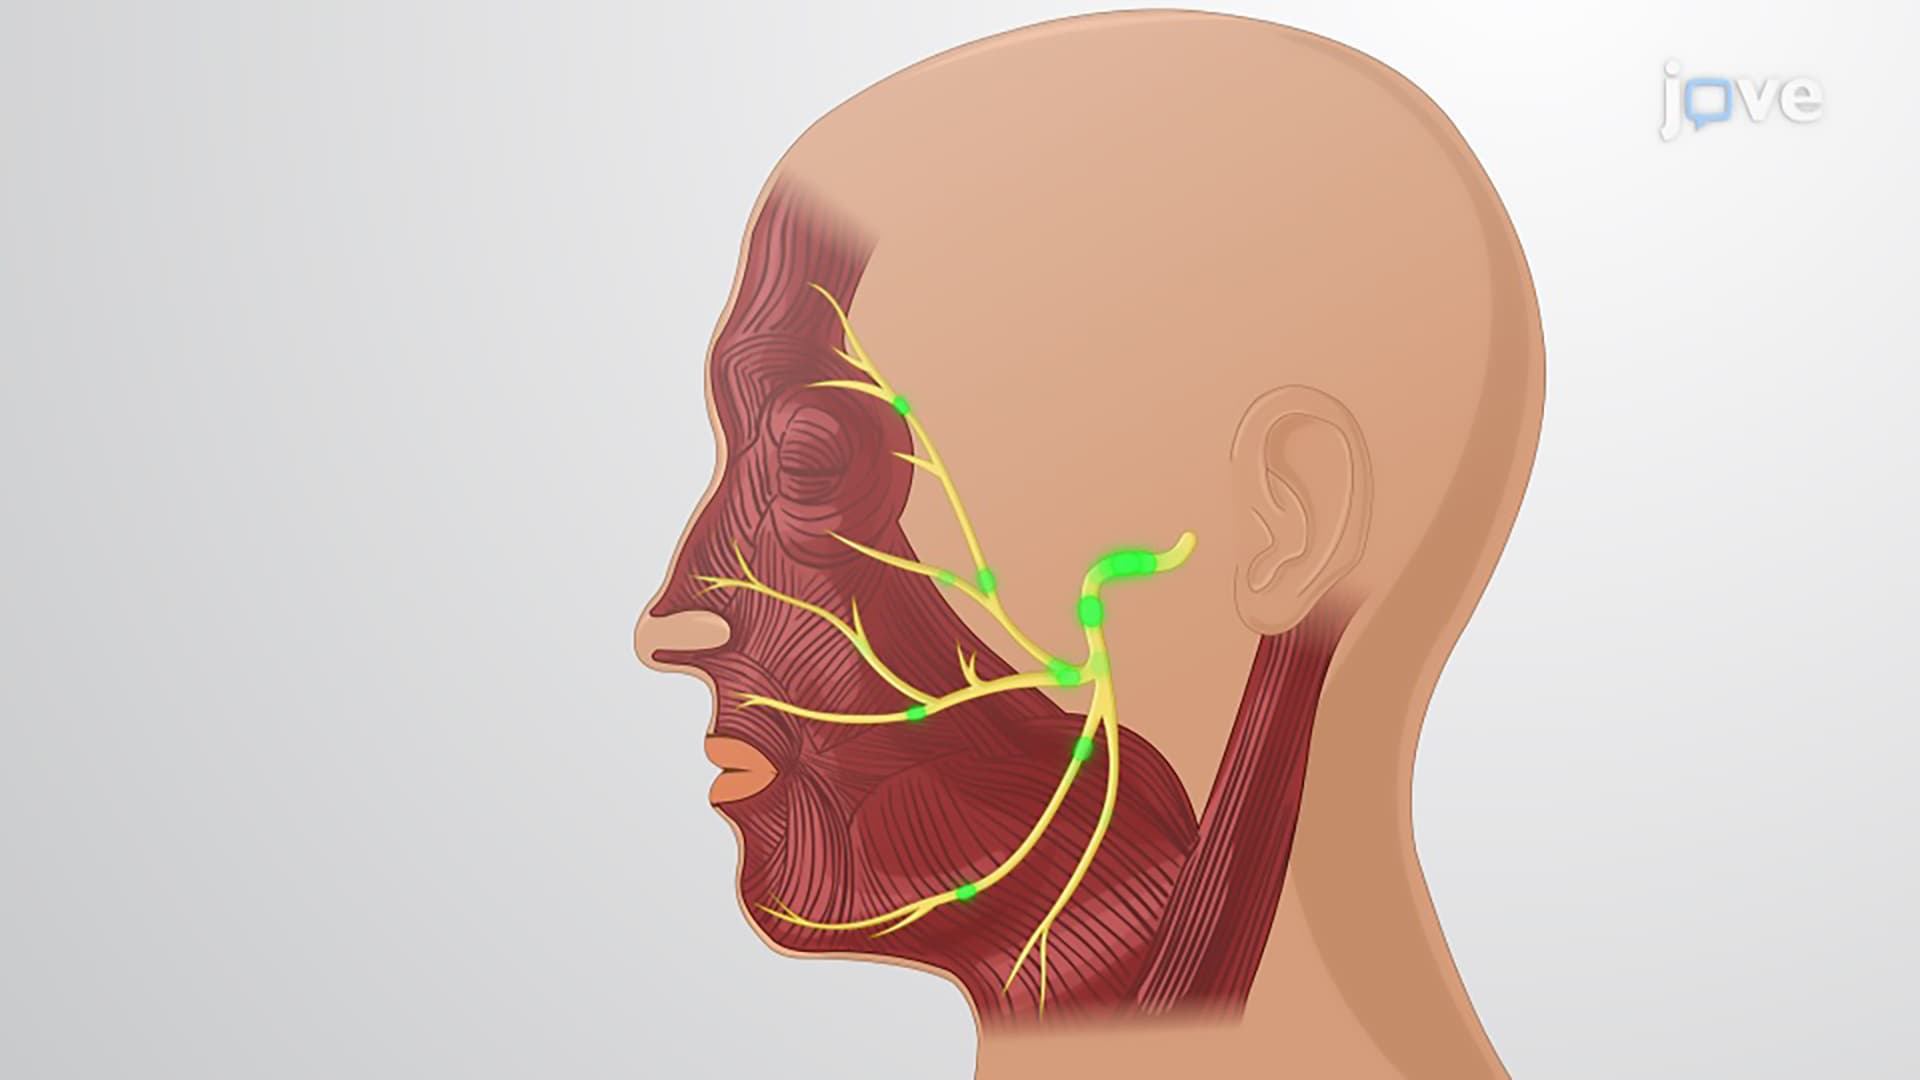
Facial Nerve (Cranial Nerve VII)
Cranial nerve VII, or the facial nerve,...
 01:22
Indirect Motor Pathways
The vestibulospinal tract originates in the vestibular nuclei of the brainstem. The vestibular system detects changes in...