Related Experiment Video
Updated: Sep 7, 2025

Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
Laparoscopic Complete Mesocolic Excision Without Routine Gastro-Pancreatico-Colic Trunk Dissection: Survival Outcomes
Nick J Battersby1,2, Hannah Wright2, Tahseen Qureshi1
1Department of Colorectal Surgery, Poole Hospital NHS FT, Dorset, United Kingdom.

Abstract:
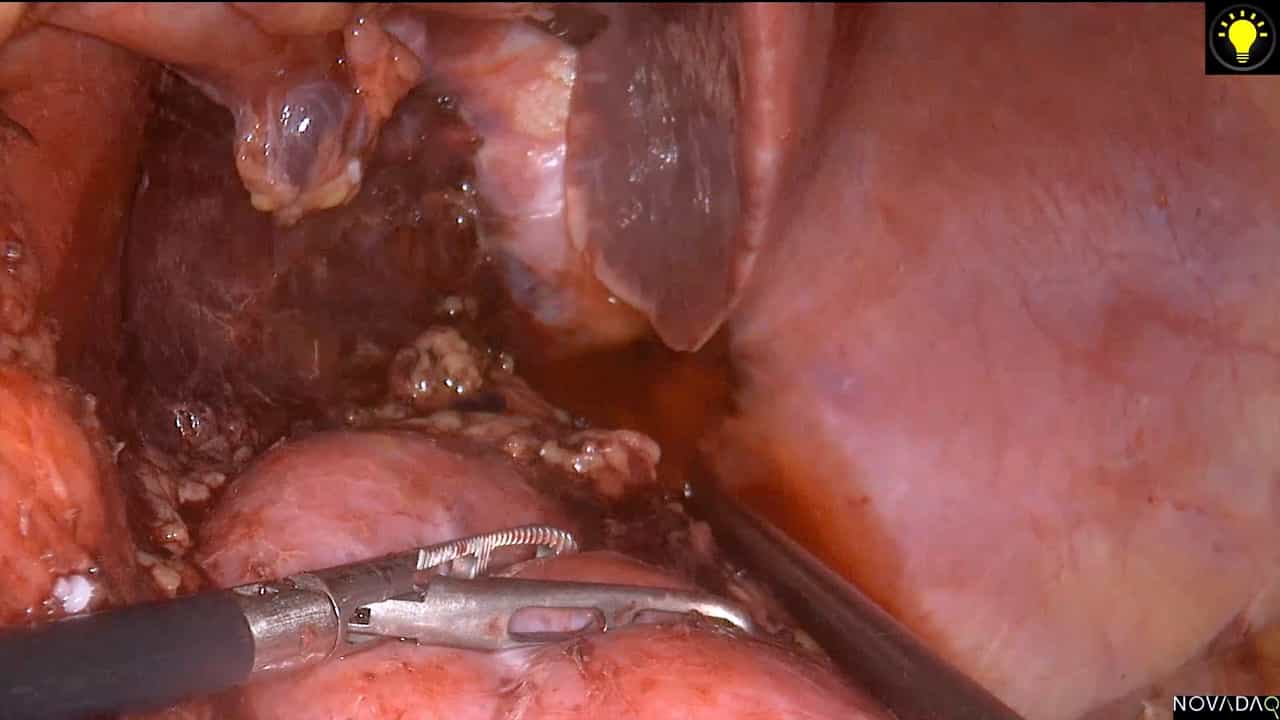
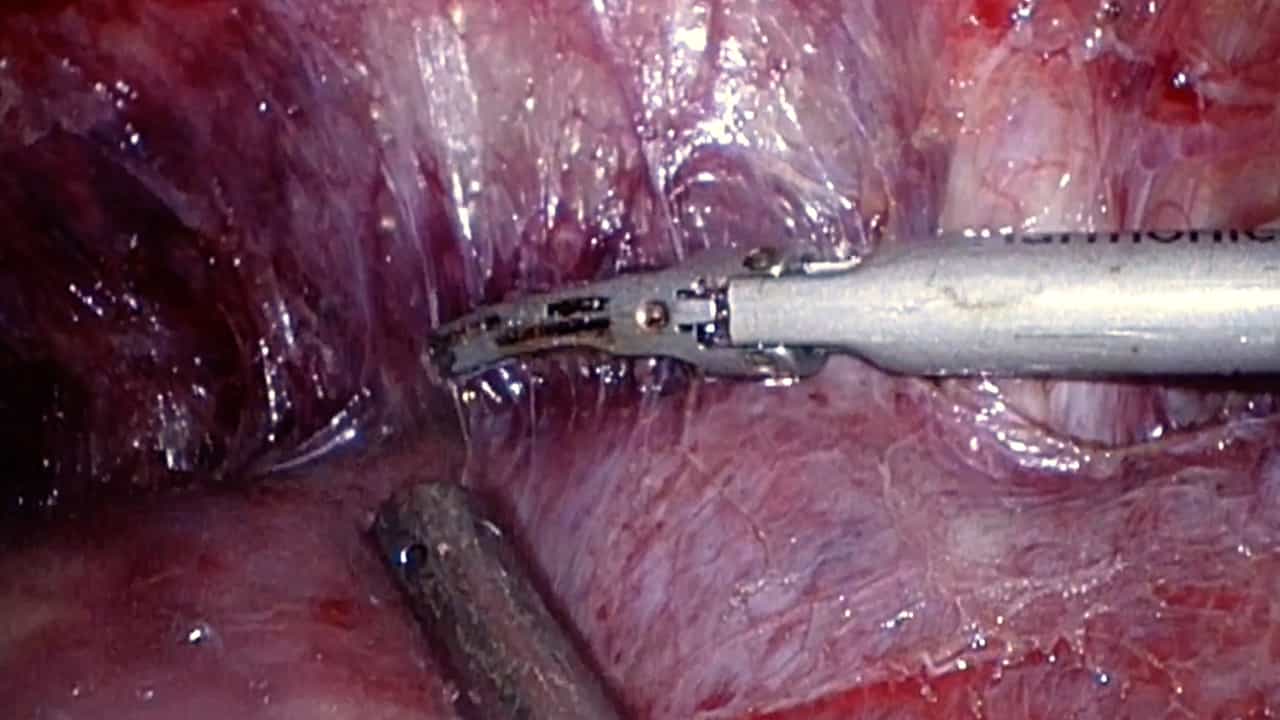
It is unclear whether the principles of open complete mesocolic excision (CME) can be safely applied to laparoscopic surgery. Furthermore, definitions vary over how radical optimal CME surgery should be. We report morbidity and oncological outcomes for laparoscopic CME without routine gastro-pancreatico-colic trunk (GPCT) dissection. An observational study with consecutive data for patients with Union for International Cancer Control (UICC) stage I-III colon adenocarcinoma who underwent elective laparoscopic resection between 2006 and 2015. Data were retrieved for demographics, tumor characteristics, treatment, and histology from prospectively maintained databases. Standardized, routinely video recorded, laparoscopic resections were performed in two United Kingdom centers from The National Training Programme for Laparoscopic Colorectal Surgery. Overall survival and disease-free survival (DFS) were reported using Kaplan-Meier curves and Cox regression. Laparoscopic CME was performed in 567 patients, 52.7% (288/546) women, median (interquartile range [IQR]) age 73 (65-80) years. Median (IQR) length of stay was 4 (3-5) days with 4.0 (2.2-5.7)-year follow-up. Significant DFS predictors (hazard ratio [HR]) by multivariable Cox regression were age >80 years (1.9), American Society of Anesthesiologists (ASA) 3 and 4 (HR = 1.1), right colon cancer (1.7), UICC stage III (3.4), and intramesocolic grade (2.2). Overall 4-year DFS (95% confidence interval) was 81.3% (77-85). Four-year DFS by UICC grades I, II, and III was 94.6% (89-99), 83.4% (77-88), and 72.2% (66-78), respectively (log-rank P = .001). Morbidity by Clavien-Dindo grade was III 18 (3.2%), IV 4 (0.7%) and V 7 (1.2%). This large series suggests standardized laparoscopic CME without routine GPCT dissection has a low morbidity and achieves equivalent outcomes to the most radical open CME techniques.