Related Experiment Video
Updated: Sep 7, 2025
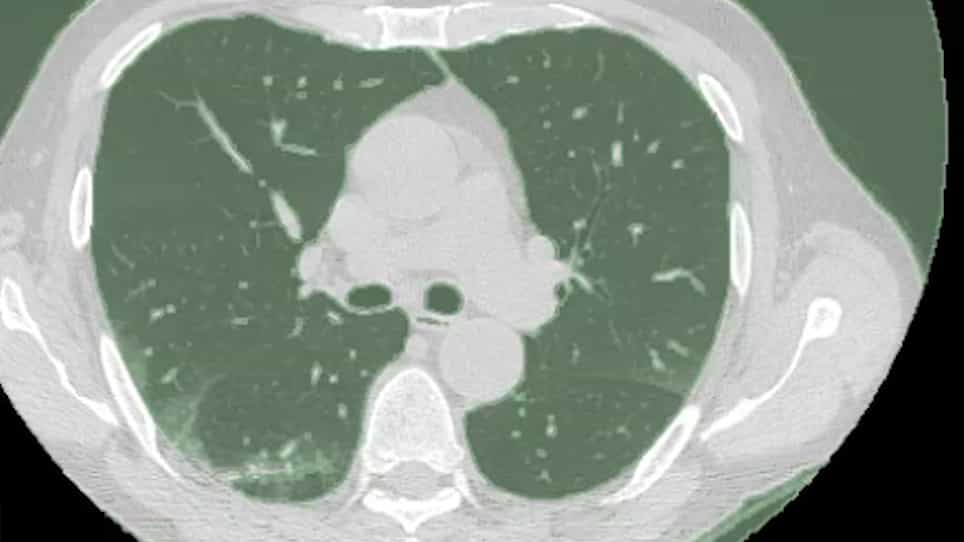

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
[Comparative analysis of clinical features between severe coronavirus disease 2019 and severe community acquired
Xiaolei Teng1, Yun Xie1, Daonan Chen1
1Department of Critical Care Medicine, Shanghai General Hospital, Shanghai Jiao Tong University School of Medicine (originally named "Shanghai First People's Hospital"), Shanghai 201620, China.

Objective:
To compare and analyze the clinical features of patients with severe coronavirus disease 2019 (sCOVID-19) and severe community acquired pneumonia (sCAP) who meet the diagnostic criteria for severe pneumonia of the Infectious Diseases Society of America/American Thoracic Society (IDSA/ATS).
Methods:
A retrospective comparative analysis of the clinical records of 116 patients with sCOVID-19 admitted to the department of critical care medicine of Wuhan Third Hospital from January 1, 2020 to March 31, 2020 and 135 patients with sCAP admitted to the department of critical care medicine of Shanghai First People's Hospital from January 1, 2010 to December 31, 2017 was conducted. The basic information, diagnosis and comorbidities, laboratory data, etiology and imaging results, treatment, prognosis and outcome of the patients were collected. The differences in clinical data between sCOVID-19 and sCAP patients were compared, and the risk factors of death were analyzed.
Results:
The 28-day mortality of sCOVID-19 and sCAP patients were 50.9% (59/116) and 37.0% (50/135), respectively. The proportion of arterial partial pressure of oxygen/fraction of inspired oxygen (PaO2/FiO2) ≤ 250 mmHg (1 mmHg ≈ 0.133 kPa) in sCOVID-19 patients was significantly higher than that of sCAP [62.1% (72/116) vs. 34.8% (47/135), P < 0.01]. The possible reason was that the proportion of multiple lung lobe infiltration in sCOVID-19 was significantly higher than that caused by sCAP [94.0% (109/116) vs. 40.0% (54/135), P < 0.01], but the proportion of sCOVID-19 patients requiring mechanical ventilation was significantly lower than that of sCAP [45.7% (53/116) vs. 60.0% (81/135), P < 0.05]. Further analysis of clinical indicators related to patient death found that for sCOVID-19 patients PaO2/FiO2, white blood cell count (WBC), neutrophils (NEU), neutrophil percentage (NEU%), neutrophil/lymphocyte ratio (NLR), total bilirubin (TBil), blood urea nitrogen (BUN), albumin (ALB), Ca2+, prothrombin time (PT), D-dimer, C-reactive protein (CRP) and other indicators were significantly different between the death group and the survival group, in addition, the proportion of receiving mechanical ventilation, gamma globulin, steroid hormones and fluid resuscitation in death group were higher than survival group. Logistic regression analysis showed that the need for mechanical ventilation, NLR > 10, TBil > 10 μmol/L, lactate dehydrogenase (LDH) > 250 U/L were risk factors for death at 28 days. For sCAP patients, there were significant differences in age, BUN, ALB, blood glucose (GLU), Ca2+ and D-dimer between the death group and the survival group, but there was no significant difference in treatment. Logistic regression analysis showed that BUN > 7.14 mmol/L and ALB < 30 g/L were risk factors for 28-day death of sCAP patients.
Conclusions:
The sCOVID-19 patients in this cohort have worse oxygen condition and symptoms than sCAP patients, which may be due to the high proportion of lesions involving the lungs. The indicators of the difference between the death group and the survival group were similar in sCOVID-19 and sCAP patients. It is suggested that the two diseases have similar effects on renal function, nutritional status and coagulation function. But there were still differences in risk factors affecting survival. It may be that sCOVID-19 has a greater impact on lung oxygenation function, inflammatory cascade response, and liver function, while sCAP has a greater impact on renal function and nutritional status.

Related Concept Videos
 01:29
Pneumonia II: Pathophysiology
 01:30
Pneumonia III: Complications and Assessment
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...