
NLRP3 inflammasome-mediated choroid plexus hypersecretion contributes to hydrocephalus after intraventricular
Zhaoqi Zhang1,2,3, Qiang Tan1,2,3, Peiwen Guo1,2,3
1Department of Neurosurgery and State Key Laboratory of Trauma, Burn and Combined Injury, Southwest Hospital, Third Military Medical University (Army Medical University), 29 Gaotanyan Street, Shapingba District, Chongqing, 400038, China.

Insights
The NLRP3 inflammasome drives cerebrospinal fluid (CSF) overproduction after brain hemorrhage, leading to hydrocephalus. Inhibiting NLRP3 reduces CSF secretion and brain swelling, offering a new therapeutic target for hydrocephalus.
Area of Science:
- Neuroscience
- Immunology
- Pathophysiology
Background:
- Hydrocephalus is a severe complication of intracerebral hemorrhage with ventricular extension (ICH-IVH), causing cerebrospinal fluid (CSF) accumulation.
- The choroid plexus epithelium is crucial for CSF secretion and the brain-immune interface.
- The role of the NLRP3 inflammasome in ICH-IVH-induced hydrocephalus was previously unknown.
Purpose of the Study:
- To investigate the role of the NLRP3 inflammasome in the pathogenesis of hydrocephalus following ICH-IVH.
- To explore the potential mechanism of NLRP3 inflammasome activation in CSF hypersecretion.
- To identify NLRP3 as a potential therapeutic target for hydrocephalus.
Main Methods:
- Developed a rat model of hydrocephalus after ICH-IVH using autologous blood infusion.
- Utilized wild-type and Nlrp3 knockout rats for comparative analysis.
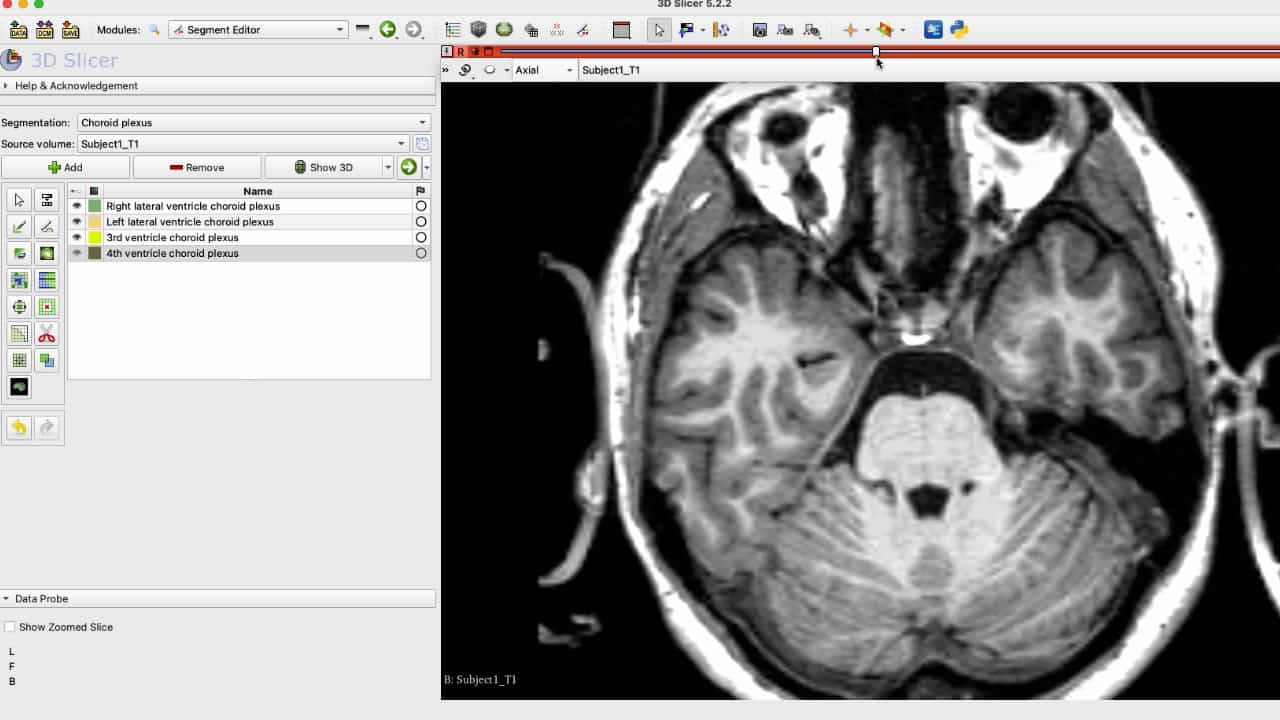
- Performed RNA-sequencing and proteomics on choroid plexus tissue, alongside in vitro experiments.
Main Results:
- ICH-IVH rats exhibited ventricular dilation and CSF hypersecretion, with peak NLRP3 inflammasome component expression at 3 days post-hemorrhage.
- Inhibition of NLRP3 (via MCC950 or knockout) reduced CSF secretion, ventricular dilation, and neurological deficits.
- NLRP3 inhibition decreased NKCC1 phosphorylation, implicating the NLRP3/p-NKCC1 pathway and ion flux in CSF regulation.
Conclusions:
- NLRP3 inflammasome activation promotes CSF hypersecretion in the choroid plexus epithelium post-hemorrhage.
- The NLRP3/p-NKCC1 pathway is a key mechanism in hydrocephalus pathogenesis after ICH-IVH.
- Targeting the NLRP3 inflammasome presents a novel therapeutic strategy for hydrocephalus.
Background:
Hydrocephalus is a severe complication of intracerebral hemorrhage with ventricular extension (ICH-IVH) and causes cerebrospinal fluid (CSF) accumulation. The choroid plexus epithelium plays an important role in CSF secretion and constitutes the blood-CSF barrier within the brain-immune system interface. Although the NLRP3 inflammasome, as a key component of the innate immune system, promotes neuroinflammation, its role in the pathogenesis of hydrocephalus after hemorrhage has not been investigated. Therefore, this study aimed to investigate the potential mechanism of NLRP3 in hydrocephalus to discover a potential marker for targeted therapy.
Methods:
A rat model of hydrocephalus after ICH-IVH was developed through autologous blood infusion in wild-type and Nlrp3-/- rats. By studying the features and processes of the model, we investigated the relationship between the NLRP3 inflammasome and CSF hypersecretion in the choroid plexus.
Results:
The ICH-IVH model rats showed ventricular dilation accompanied by CSF hypersecretion for 3 days. Based on the choroid plexus RNA-seq and proteomics results, we found that an inflammatory response was activated. The NLRP3 inflammasome was investigated, and the expression levels of NLRP3 inflammasome components reached a peak at 3 days after ICH-IVH. Inhibition of NLRP3 by an MCC950 inflammasome inhibitor or Nlrp3 knockout decreased CSF secretion and ventricular dilation and attenuated neurological deficits after ICH-IVH. The mechanism underlying the neuroprotective effects of NLRP3 inhibition involved decreased phosphorylation of NKCC1, which is a major protein that regulates CSF secretion by altering Na+- and K+-coupled water transport, via MCC950 or Nlrp3 knockout. In combination with the in vitro experiments, this experiment confirmed the involvement of the NLRP3/p-NKCC1 pathway and Na+ and K+ flux.
Conclusions:
This study demonstrates that NKCC1 phosphorylation in the choroid plexus epithelium promotes NLRP3 inflammasome-mediated CSF hypersecretion and that NLRP3 plays an important role in the pathogenesis of hydrocephalus after hemorrhage. These findings provide a new therapeutic strategy for treating hydrocephalus.
Related Concept Videos
 01:26
Bacterial Meningitis II: Pathophysiology
 01:26
Encephalitis ll: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:19
Cerebral Edema l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology