Related Experiment Video
Updated: Sep 6, 2025


Improved Renal Denervation Mitigated Hypertension Induced by Angiotensin II Infusion
Published on: May 26, 2022
Cardiovascular and Renal Outcomes with Finerenone, a Selective Mineralocorticoid Receptor Antagonist
Srikanth Palanisamy1, Mario Funes Hernandez2,3, Tara I Chang3
1Department of Medicine, Stanford University School of Medicine, Stanford, CA, USA. sripal@stanford.edu.

Abstract:
Overactivation of the renin-angiotensin-aldosterone system (RAAS) has been shown to be pathologic in heart failure and albuminuric chronic kidney disease (CKD), triggering pro-inflammatory and pro-fibrotic cellular pathways. The standard of care in these disease states includes treatment with angiotensin-converting enzyme (ACE) inhibitors or angiotensin receptor blockers. Mineralocorticoid receptor antagonists (MRAs) are also a mainstay in the treatment of heart failure with reduced ejection fraction; however, therapy is often limited by treatment-related hyperkalemia. In albuminuric CKD, the risk of hyperkalemia, acute kidney injury (AKI), and hypotension also remains significant. Finerenone is a novel non-steroidal MRA that may obviate some of these concerns and have therapeutic potential in additional patient populations. Finerenone was developed using the chemical structure of a dihydropyridine channel blocker but optimized to create a bulky MRA without any activity at the L-type calcium channel. It has several novel cellular mechanisms that may account for its ability to reduce cardiac hypertrophy and proteinuria more efficiently than an equinatriuretic dose of a steroidal MRA, while retaining anti-inflammatory and anti-fibrotic properties. Finerenone also has a lower rate of treatment-related hyperkalemia and AKI than steroidal MRAs with a smaller effect on systolic blood pressure, greatly expanding its therapeutic utility. The recently published FIGARO-DKD and FIDELIO-DKD trials demonstrate that treatment with finerenone in patients with type II diabetes and albuminuric CKD results in improved cardiovascular outcomes and a lower risk of CKD progression. Patients enrolled in these studies were already on maximally tolerated ACE inhibitor or angiotensin receptor blocker therapy. Trials investigating finerenone's therapeutic effect in patients with heart failure with preserved ejection fraction (HFpEF) and non-diabetic CKD, as well sodium-glucose cotransporter 2 (SGLT2) and finerenone combination therapy in patients with diabetic nephropathy, are ongoing.
More Related Videos
 08:50
5/6th Nephrectomy in Combination with High Salt Diet and Nitric Oxide Synthase Inhibition to Induce Chronic Kidney Disease in the Lewis Rat
Published on: July 3, 2013
 03:13
Technical Refinement of a Bilateral Renal Ischemia-Reperfusion Mouse Model for Acute Kidney Injury Research
Published on: November 3, 2023
Related Concept Videos
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:22
Heart Failure Drugs: Diuretics
 01:30
Heart Failure V: Medical Management
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:15
Renal Drug Excretion: Overview
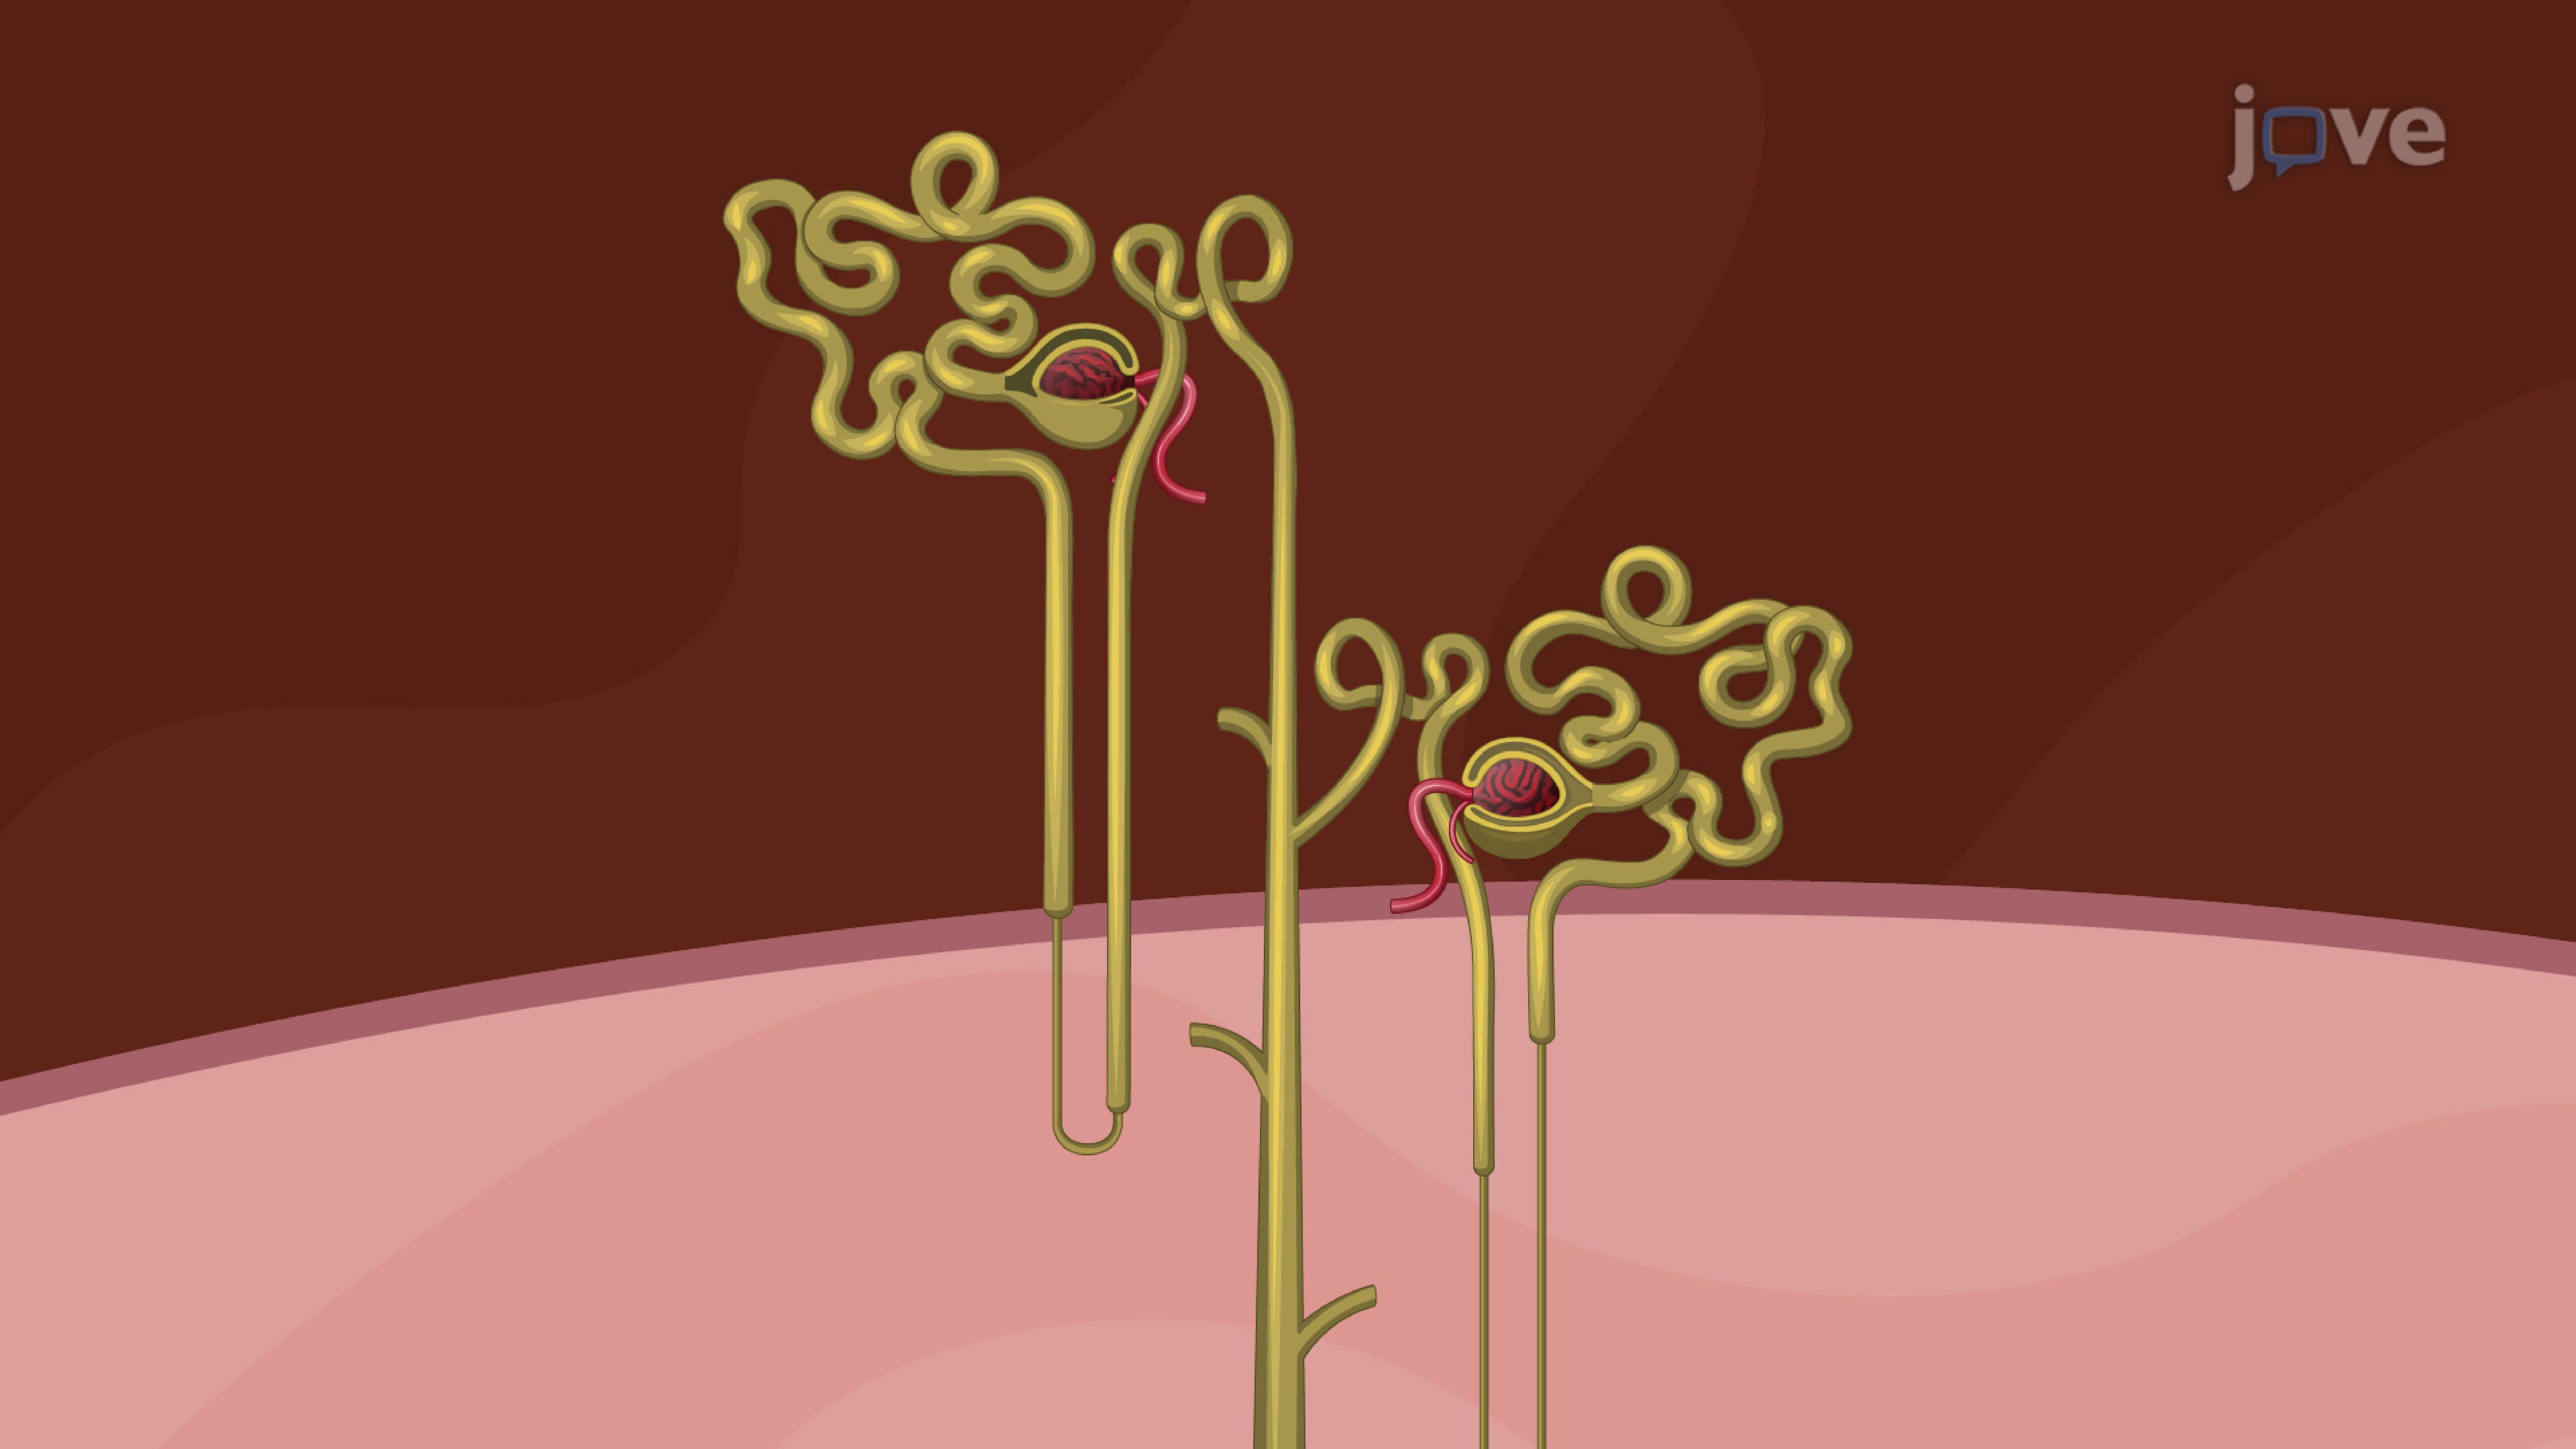
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...