Related Experiment Video
Updated: Sep 6, 2025
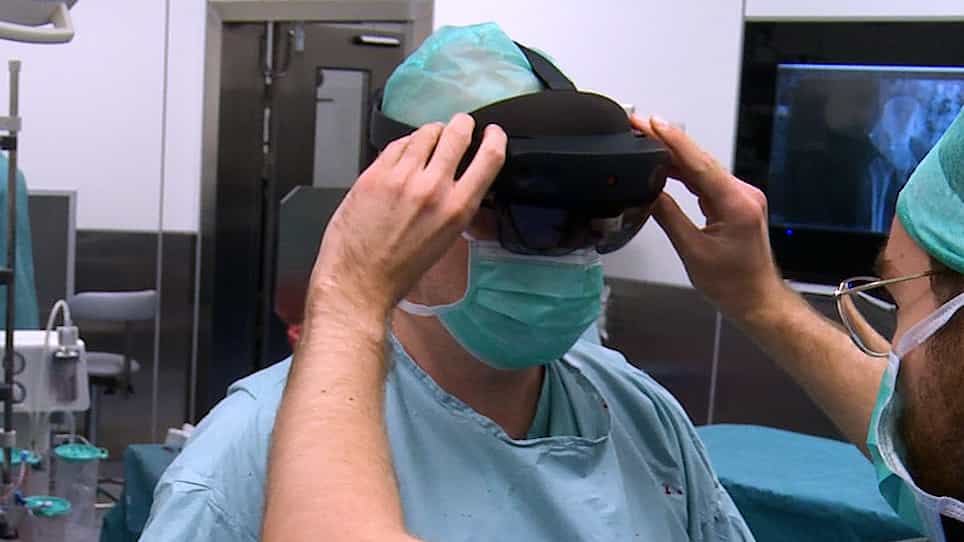

The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Revision Total Hip Arthroplasty for Aseptically Failed Metal-On-Metal Hip Resurfacing Arthroplasty
Harold I Salmons1, Kristin M Fruth1, David G Lewallen1
1Department of Orthopedic Surgery, Mayo Clinic, Rochester, Minnesota.

Background:
While common, studies assessing outcomes of failed metal-on-metal (MoM) resurfacings converted to total hip arthroplasties (THAs) are limited. We determined the outcomes following revision THA of aseptic MoM hip resurfacings.
Methods:
Between 2000 and 2019, we identified 52 revision THAs for failed MoM hip resurfacings through our total joint registry. Mean age was 55 years, 42% were women, and mean body mass index was 28 kg/m2. Adverse local tissue response led to THA in 67% of the cases. The most common revision articulation was metal-on-cross-linked or ceramic-on-cross-linked polyethylene (71%). Median head size was 36 mm. The acetabular component was retained in 21% and 28% used dual-mobility constructs. The mean follow-up was 6 years (range, 2-12 years).
Results:
The 5-year survivorships free of any re-revision or reoperation were 89% and 85%, respectively. The primary cause of re-revision (6) was dislocation (4). The 5-year cumulative probability of dislocation was 19% and was 13% in those patients treated with dual-mobility constructs versus 22% in those treated with standard articulations (P = .58). No dislocations occurred in THAs with retained acetabular components and dual-mobility constructs versus a 5-year cumulative probability of dislocation of 25% in those with revised acetabular components and standard articulations (P = .24).
Conclusion:
Revision THAs for aseptically failed MoM hip resurfacings yielded a 5-year survivorship free of re-revision of 89%. The main reason for failure was dislocation, which was reduced, but not statistically significantly, when a dual-mobility construct was used, especially if the acetabular component was retained.
Level Of Evidence:
IV.

