Related Experiment Video
Updated: Sep 6, 2025


Improving IV Insulin Administration in a Community Hospital
Published on: June 11, 2012
MEALTIME BOLUS INSULIN DOSE TIMING IN CHILDREN WITH TYPE 1 DIABETES: REAL-LIFE DATA FROM A TERTIARY CARE CENTRE IN
L Rohilla1, D Dayal1, N Gujjar1
1Post Graduate Institute of Medical Education and Research - Endocrinology and Diabetes Unit, Department of Pediatrics, Chandigarh, India.

Insights
Administering insulin bolus after meals for children with type 1 diabetes (T1D) showed similar glycemic control and safety compared to premeal dosing. This real-world study suggests flexible insulin timing may be effective for young children with T1D.
Area of Science:
- Pediatrics
- Endocrinology
- Metabolic Diseases
Background:
- Type 1 diabetes (T1D) management in young children typically involves preprandial (before meal) insulin bolus administration.
- Limited real-world data exists on postprandial (after meal) insulin bolus timing in this age group.
- Previous controlled studies on pre- vs. postprandial insulin bolus have yielded variable results.
Observation:
- This retrospective study analyzed data from 44 children under 7 years old with T1D.
- Children were divided into two groups: preprandial insulin bolus (Group 1) and postprandial insulin bolus (Group 2).
- Mean follow-up duration was two years.
Findings:
- No significant differences were observed in mean glycosylated hemoglobin (HbA1c) levels between the preprandial and postprandial groups.
- Hypoglycemic events and diabetic ketoacidosis (DKA) episodes were comparable in both groups.
- Postprandial insulin bolus administration demonstrated similar long-term glycemic control and safety profiles.
Implications:
- Flexible insulin bolus timing (during or after meals) appears safe and effective for young children with T1D.
- These findings support considering postprandial insulin bolus as a viable option for managing T1D in this population.
- Larger real-world studies are warranted to further investigate flexible insulin bolus strategies in pediatric T1D.
Context:
Mealtime insulin bolus is traditionally administered before meals in children with type 1 diabetes (T1D). Controlled studies on the use of pre-and postprandial insulin bolus have shown variable results. There are no real-world studies on postprandial bolusing of insulin in young children with T1D.
Methods:
Children with T1D aged <7 years were grouped into preprandial (Group 1) or postprandial (Group 2) groups according to the practice of prandial insulin use. Their retrospective data on mean glycosylated hemoglobin (HbA1c), hypoglycemic events, and diabetic ketoacidosis (DKA) episodes were compared.
Results:
Forty-four children (mean age 4.1±1.3 years, range 2-7 years) with mean diabetes duration of 2.0±0.7 years (range, 1-4 years) were identified; 23 (52.3%) belonged to Group 1 and 21 (47.7%) to Group 2. There were no differences in the mean HbA1c levels, mean hypoglycemic events, and DKA episodes between the two groups during a mean follow-up duration of two years.
Conclusion:
Young children with T1D administered insulin bolus during or immediately after meals showed similar long-term glycemic control and diabetes-related adverse event profile compared to the premeal timing of insulin bolus. Larger real-world studies are needed on flexible insulin bolus timing in young children with T1D.
More Related Videos
 05:35
Author Spotlight: Developing a Point-of-Care Hemoglobin Estimation Method for Anemia Management
Published on: January 19, 2024
 08:13
Study of In Vivo Glucose Metabolism in High-fat Diet-fed Mice Using Oral Glucose Tolerance Test OGTT and Insulin Tolerance Test ITT
Published on: January 7, 2018
Related Concept Videos
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into...
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:18
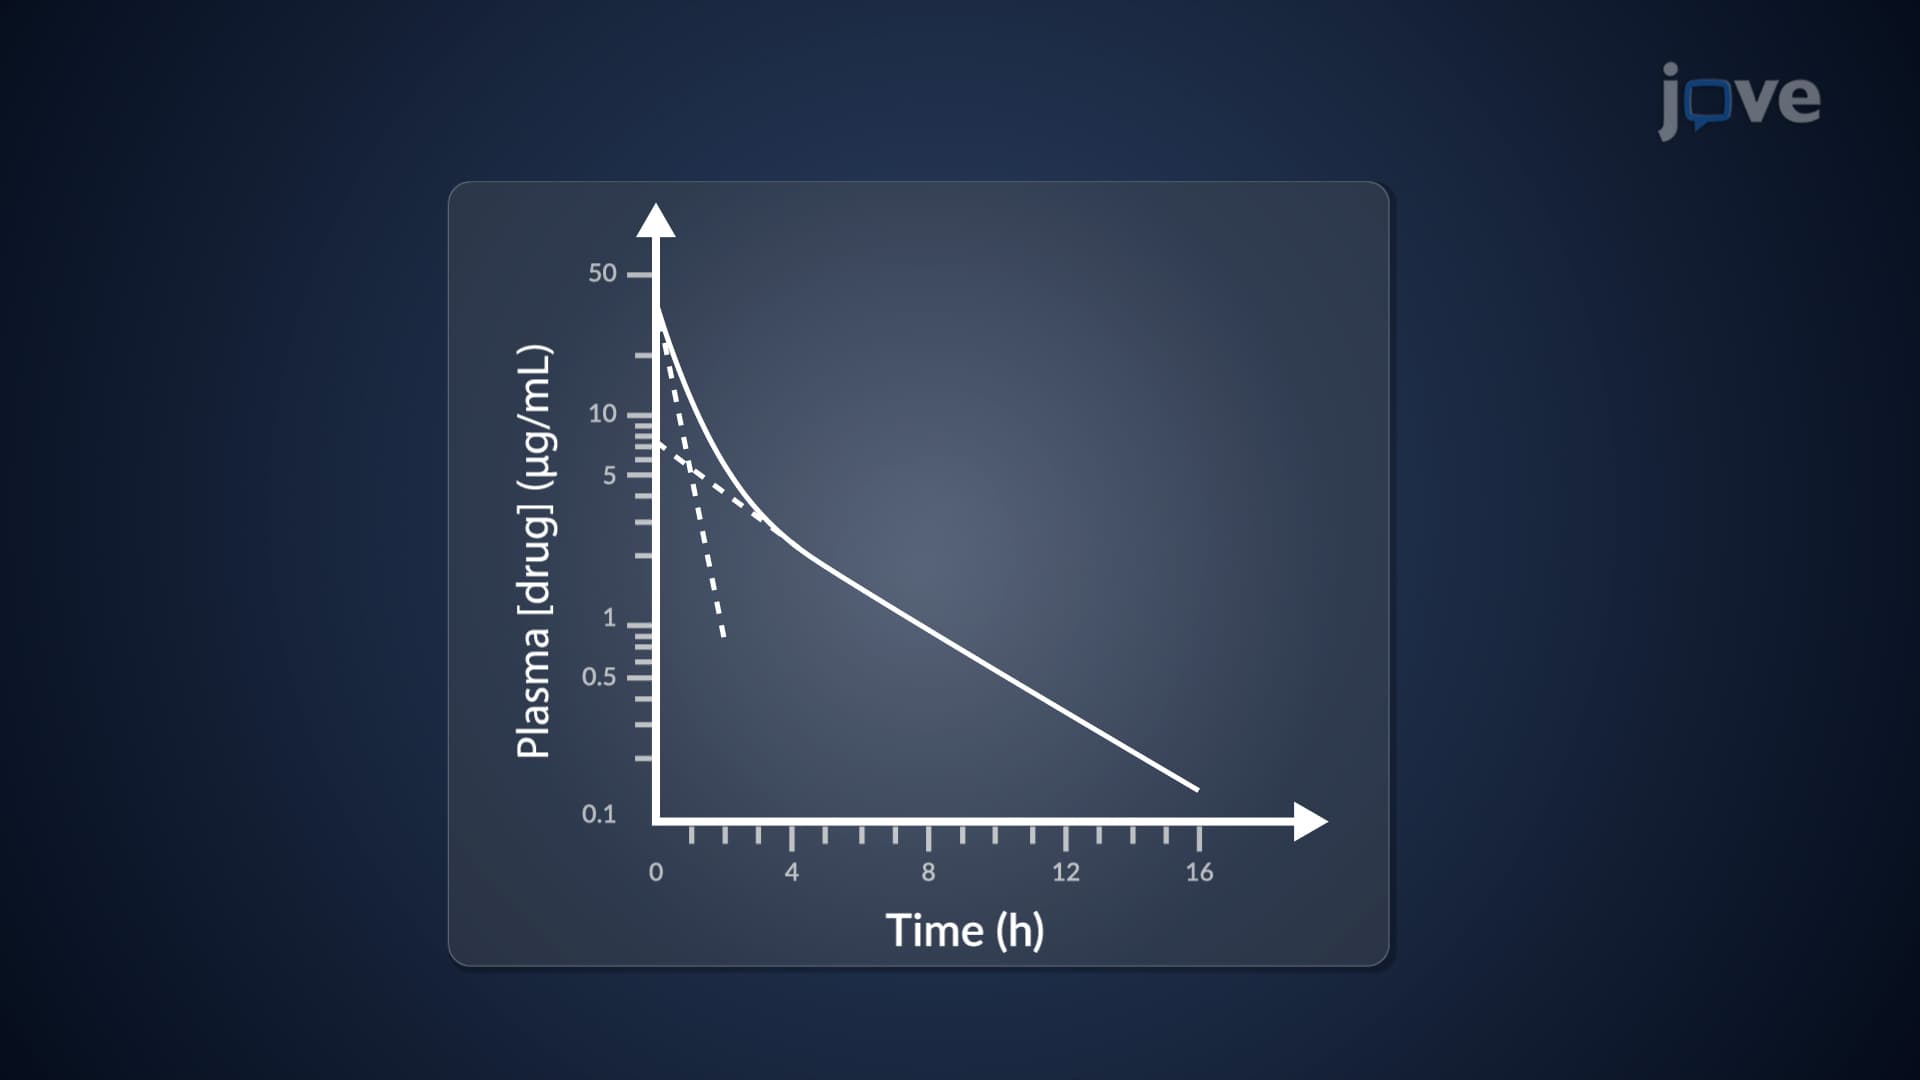
Two-Compartment Open Model: IV Bolus Administration
The disparity between drug input and the sum of drug transfer rates between...
 01:19
One-Compartment Open Model for IV Bolus Administration: General Considerations
The drug's presence in the body is defined by an equation representing the difference between the rates of drug entry and exit. Key parameters—elimination rate constant,...
 01:09
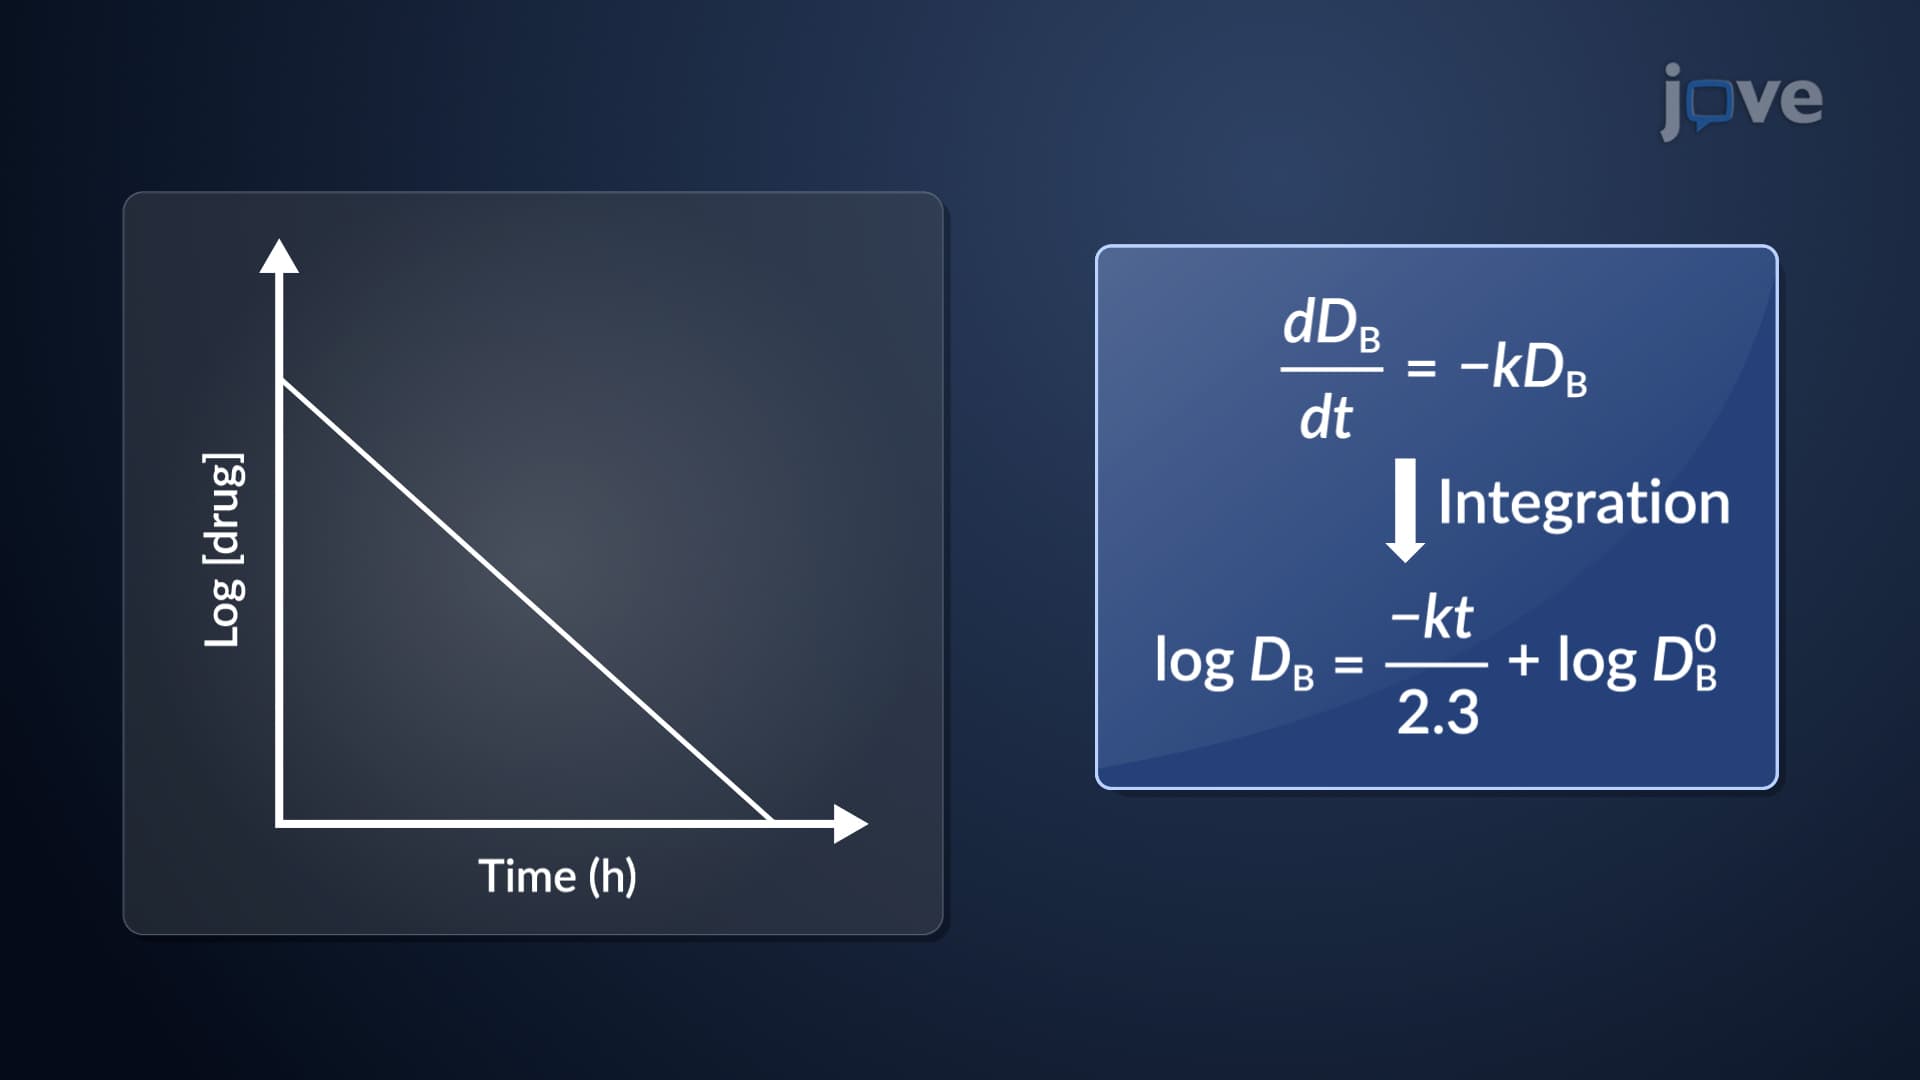
One-Compartment Open Model for IV Bolus Administration: Estimation of Elimination Rate Constant, Half-Life and Volume of Distribution