Is it Necessary to Stabilize Every Fracture in Patients with Serial Rib Fractures in Blunt Force Trauma?
Sebastian Reindl1, Philipp Jawny1, Evaldas Girdauskas1
1Department for Cardiothoracic Surgery, Medical Faculty, University Hospital Augsburg, Augsburg, Germany.

Introduction:
Management of traumatic rib fractures is subject of controversial discussions. Rib fractures are common, especially after traffic accidents and falls. There is no consensus on whether and how many rib fractures need reconstruction. Not every rib fracture needs to be stabilized, but conservative treatment by internal splinting and analgesia is not effective for all patients. Deformities of the chest wall with reduced thoracic volume and restrictive ventilation disorders must be avoided. Intraoperative assessment of fractures and chest stability plays a central role.
Material And Methods:
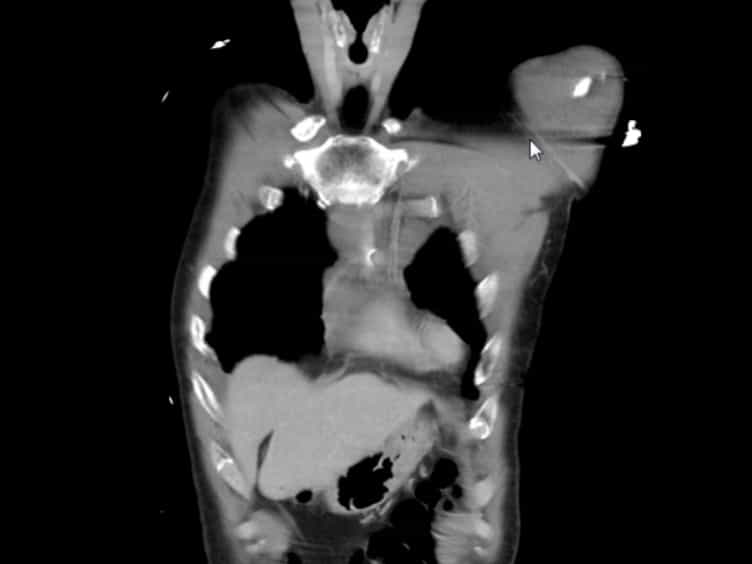
From 07/2016 to 07/2021, a total of 121 chest wall stabilizations were performed (m:f = 2:1, age 65 ± 14.5 a). Indications for surgery were the following criteria: (1) palpatory instability of the chest wall, (2) dislocated fracture endings, (3) concomitant injuries, (4) uncontrollable pain symptoms. In all patients, a computed tomography scan of the thorax was performed before the osteosynthetic treatment to assess dislocation of the fracture endings and possible concomitant injuries of intrathoracic organs.
Results:
Video-assisted thoracoscopy was performed in all patients. Hemothorax and concomitant injuries of the lung, diaphragm and mediastinum could be assessed. This was followed by an intraoperative assessment of the rib fractures, in particular penetration of fracture endings and resulting instability and deformity. Relevant fractures could be identified and subsequent incisions for rib osteosynthesis precisely defined. 6.3 (±2.7) rib fractures were detected, but 2.4 (±1.2) ribs treated osteosynthetically. Bilateral rib fractures were present in 26 patients (21.5%). Post-operative bleeding occurred in seven patients (5.8%), a breakage of the osteosynthetic material in two patients (1.7%).
Discussion:
Intraoperative assessment of relevant fractures and dislocation is the decisive criterium for osteosynthesis. Thoracoscopy is mandatory for this purpose - also to identify accompanying injuries. Not every fracture has to be approached osteosynthetically. Even with serial rib fractures or multiple fractures in a single rib, the thoracic contour can be restored by stabilizing only relevant fractures. Intraoperative palpation can adequately assess the stability and thus the result of the osteosynthesis. Even after surgical treatment of thoracic trauma, adequate analgesia and respiratory therapy are important to the healing process.
More Related Videos
 07:35
Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...