Related Experiment Video
Updated: Sep 6, 2025


Effect of Hyaluronic Acid 35 kDa on an In Vitro Model of Preterm Small Intestinal Injury and Healing Using Enteroid-Derived Monolayers
Published on: July 28, 2022
Complementary food introduction practices in infants with intestinal failure
Anita M Nucci1, Kate Samela2, Elizabeth Bobo3
1Department of Nutrition, Georgia State University, Atlanta, Georgia, USA.

Background:
Oral intake in infants with intestinal failure (IF) may be limited due to intolerance or feeding difficulties. Guidelines for the introduction of semisolid or solid complementary foods (CFs) to infants with IF do not exist. CF intake and caloric contribution from CF is difficult to assess due to malabsorption and incomplete recording. The aim of this study was to identify institutional approaches to introducing CF to infants with IF.
Methods:
The American Society for Parenteral and Enteral Nutriton (ASPEN) Pediatric Intestinal Failure Section Registered Dietitian/Nutritionist (RDN) working group designed a 10-question online cloud-based survey to assess group member practice related to the introduction of CF to infants with IF.
Results:
Twenty-six surveys were completed. Thirteen (50%) RDNs recommend introduction of CF between 4 and 6 months of age. Nineteen (76%) recommend adding pureed foods to gastrostomy tube feedings. Seventeen (65%) follow standard infant feeding practice guidelines with half citing the American Academy of Pediatrics. Approximately half (44%) recommend introducing vegetables first and the majority (80%) recommend delaying the introduction of fruits. The vast majority (92%) recommend specific foods to minimize stool output including green beans, bananas, infant cereals, and meats/protein.
Conclusion:
Institutional practices related to the introduction of CF to infants with IF vary. Similarities with first food choice and foods to avoid were observed. Evidenced-based practice guidelines for the introduction of CF to infants with IF need to be established to determine best practices for reducing stool output, encouraging weaning from parenteral nutrition, and achieving enteral autonomy.
Related Concept Videos
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the...
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:29
Intestinal Phase of Digestion
The arrival of the chyme in the small intestine distends the duodenum, which triggers the enterogastric reflex. This distension...
 01:18
Routes of Drug Administration: Enteral
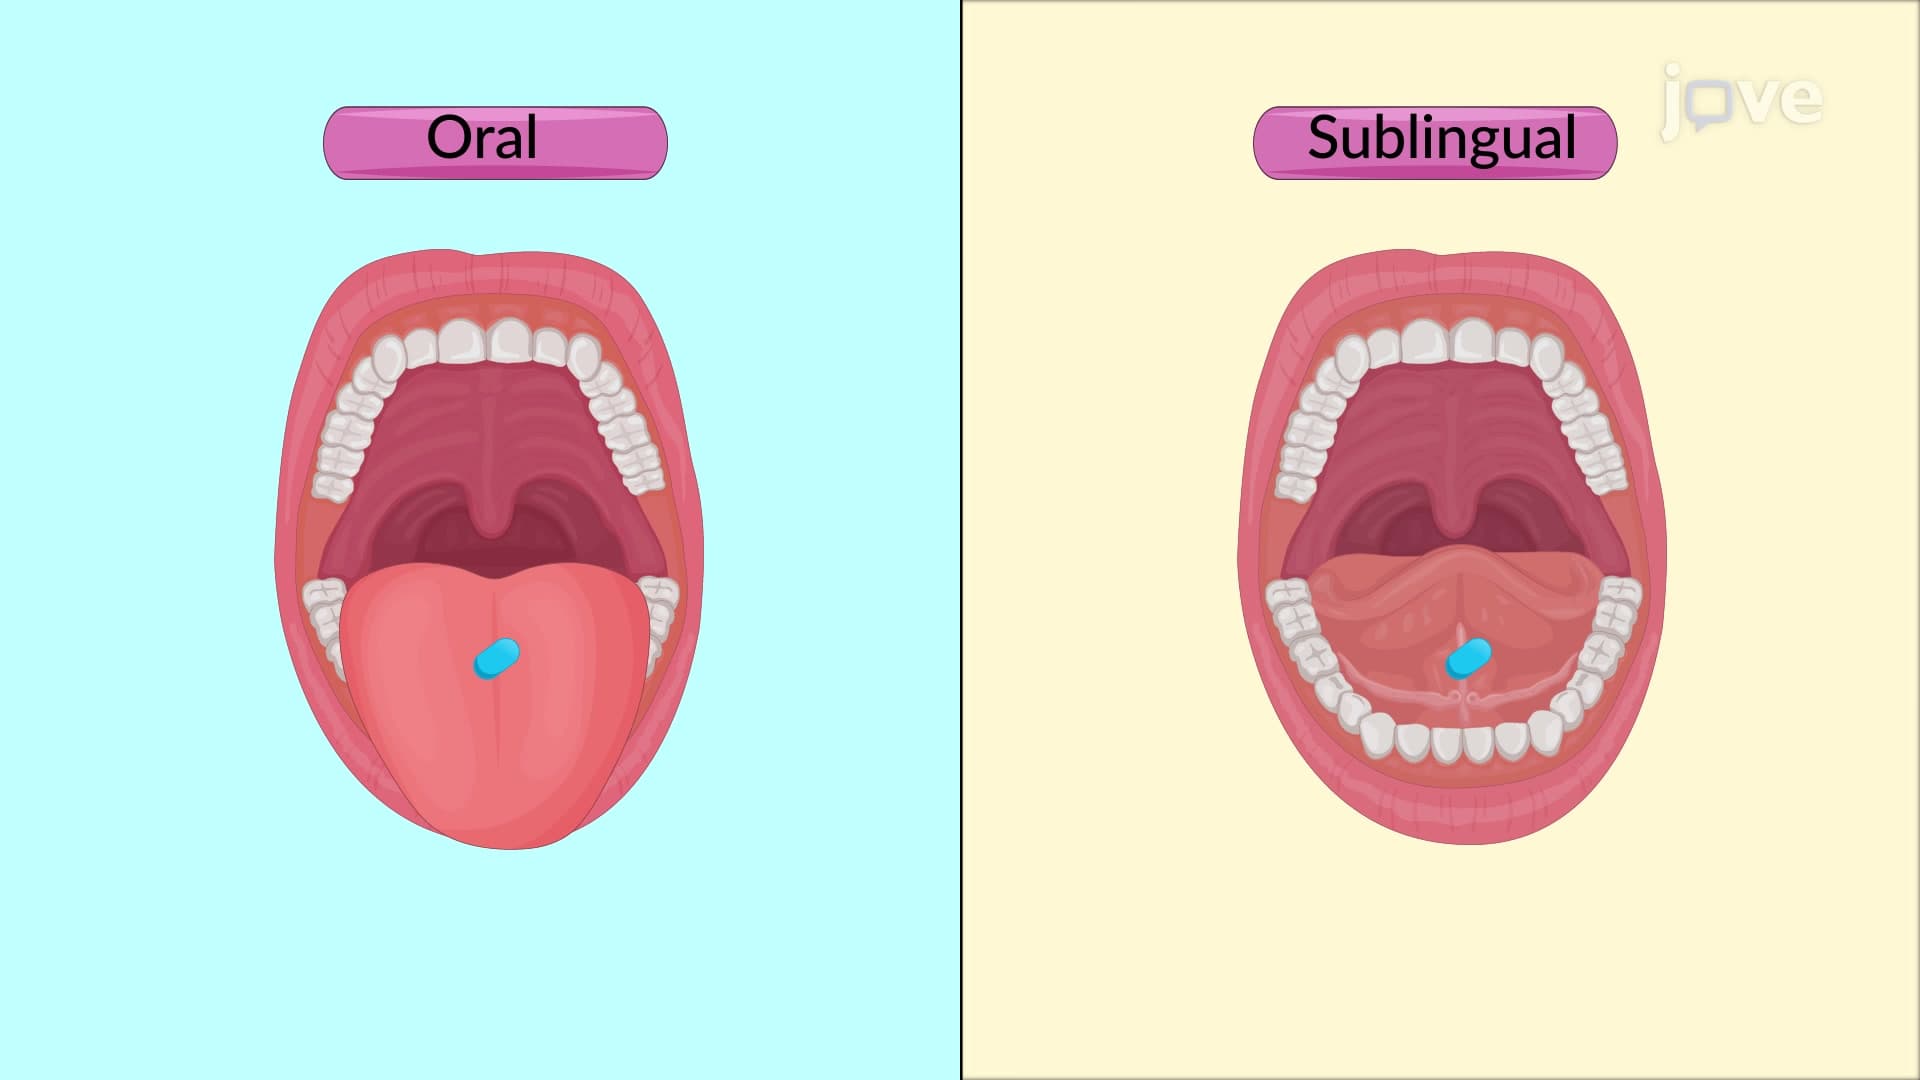
Enteral administration involves drug administration via the mouth in two ways: orally or sublingually.
Unlike sublingually drugs, drugs that are taken orally pass through the gastrointestinal (GI) tract and get metabolized by the liver. Once metabolized, the drug is absorbed into the systemic circulation, reaching different body parts via the bloodstream. However, while passing through the stomach,...