Related Experiment Video
Updated: Sep 6, 2025
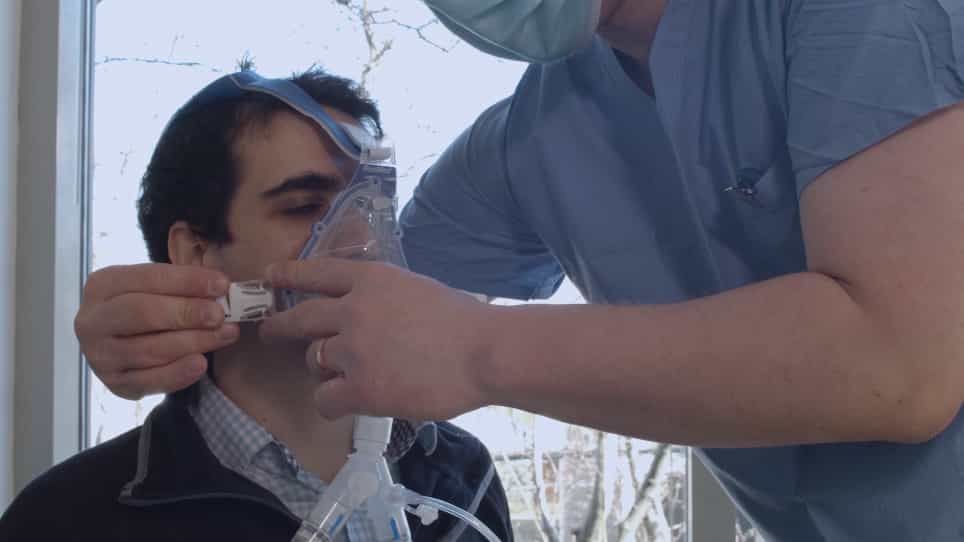

A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
Effect of asthma management with exhaled nitric oxide versus usual care on perinatal outcomes
Vanessa E Murphy1,2, Megan E Jensen3,2, Elizabeth G Holliday2
1Priority Research Centre Grow Up Well, University of Newcastle, and Hunter Medical Research Institute, Newcastle, Australia vanessa.murphy@newcastle.edu.au.

Introduction:
Asthma exacerbations in pregnancy are associated with adverse perinatal outcomes. We aimed to determine whether fractional exhaled nitric oxide (F ENO)-based asthma management improves perinatal outcomes compared to usual care.
Methods:
The Breathing for Life Trial was a multicentre, parallel-group, randomised controlled trial conducted in six hospital antenatal clinics, which compared asthma management guided by F ENO (adjustment of asthma treatment according to exhaled nitric oxide and symptoms each 6-12 weeks) to usual care (no treatment adjustment as part of the trial). The primary outcome was a composite of adverse perinatal events (preterm birth, small for gestational age (SGA), perinatal mortality or neonatal hospitalisation) assessed using hospital records. Secondary outcomes included maternal asthma exacerbations. Concealed random allocation, stratified by study site and self-reported smoking status was used, with blinded outcome assessment and statistical analysis (intention to treat).
Results:
Pregnant women with current asthma were recruited; 599 to the control group (608 infants) and 601 to the intervention (615 infants). There were no significant group differences for the primary composite perinatal outcome (152 (25.6%) out of 594 control, 177 (29.4%) out of 603 intervention; OR 1.21, 95% CI 0.94-1.56; p=0.15), preterm birth (OR 1.14, 95% CI 0.78-1.68), SGA (OR 1.06, 95% CI 0.78-1.68), perinatal mortality (OR 3.62, 95% CI 0.80-16.5), neonatal hospitalisation (OR 1.24, 95% CI 0.89-1.72) or maternal asthma exacerbations requiring hospital admission or emergency department presentation (OR 1.19, 95% CI 0.69-2.05).
Conclusion:
F ENO-guided asthma pharmacotherapy delivered by a nurse or midwife in the antenatal clinic setting did not improve perinatal outcomes.

Related Concept Videos
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by...
 01:30
Asthma-IV: Nursing Management
First, in...
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:24
Asthma-III: Symptoms and Complications
Classification of Asthma