The optimal extent of lymph node dissection in N1b papillary thyroid microcarcinoma based on clinicopathological factors and preoperative ultrasonography
Related Experiment Video
Updated: Sep 5, 2025
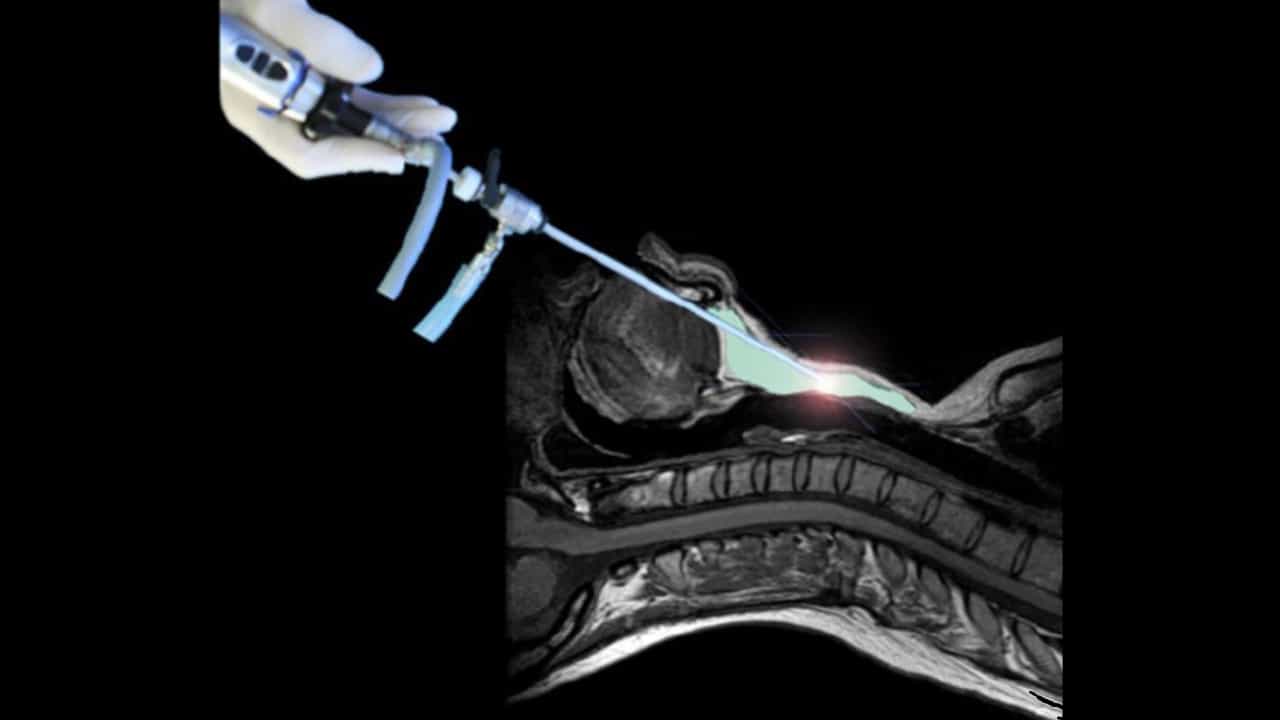
Transoral Robotic Total Thyroidectomy and Bilateral Central Regional Lymph Node Dissection for Papillary Thyroid Carcinoma
Published on: September 15, 2023
Xiao-Nan Liu1,2, Yuan-Sheng Duan1, Kai Yue1
1Department of Maxillofacial & E.N.T. Oncology, Tianjin Medical University Cancer Institute and Hospital, National Clinical Research Center for Cancer; Key Laboratory of Cancer Prevention and Therapy, Tianjin; Tianjin's Clinical Research Center for Cancer, Tianjin, China.

Background:
The optimal extent of lymph node (LN) dissection in the management of N1b papillary thyroid microcarcinoma (PTMC) is still under debate in clinical practice, so we aimed to identify the risk factors associated with multilevel lateral lymph node metastasis (LLNM) with regard to the extent of LN dissection.
Methods:
The clinical data of 182 N1b PTMC patients between January 2019 and June 2021 at Tianjin Medical University Cancer Institute and Hospital were retrospectively reviewed. The frequency pattern and distribution of LLNM were analyzed for risk factors. We assessed the diagnostic value of preoperative ultrasonography (USG) for identifying levels II-V metastasis in PTMC patients.
Results:
The proportion of multilevel LLNM in N1b PTMC was 72.1%, and the most common pattern was metastasis at two levels (41.2%). Capsule invasion [odds ratio (OR) =6.861, 95% confidence interval (CI): 1.462-32.190, P=0.015], upper pole [OR =2.125, 95% CI: 1.010-4.473, P=0.047], central LN ratio [OR =7.315, 95% CI: 1.309-40.877, P=0.023], thyroid-stimulating hormone (TSH) >1.5 mIU/mL [OR =2.773, 95% CI: 1.269-6.060, P=0.011], and extranodal extension (ENE) [OR =2.632, 95% CI: 1.207-5.739, P=0.015] were independent risk factors for multilevel metastasis. In addition, unltrasonography had high sensitivity and specificity in the diagnosis of metastasis at level V (75.0%, 78.4%) and multilevel LLNM (67.2%, 64.8%).
Conclusions:
Modified radical neck dissection (MRND) in N1b PTMC patients may be reserved for patients with simultaneous 3-level LLNM or clinically evident metastasis at level V. Preoperative USG may have certain suggestive significance in the diagnosis of multilevel LLNM in primary PTMC.