Related Experiment Video
Updated: Sep 5, 2025
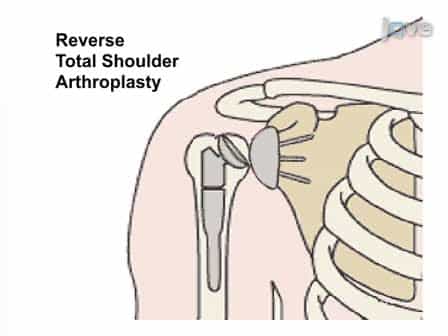

Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Opioid-sparing pain management protocol after shoulder arthroplasty results in less opioid consumption and higher
Caleb A Jones1, Thomas W Throckmorton1, Jeff Murphy2
1University of Tennessee Health Science Center, Campbell Clinic Department of Orthopaedic Surgery and Biomedical Engineering, Memphis, TN, USA.

Background:
The opioid epidemic has become a central focus in health care. In an effort to reduce opioid use, orthopedic surgeons use multimodal strategies to control postoperative pain. However, no clear consensus exists on ideal pain management strategies after shoulder arthroplasty, and most protocols are opioid-driven. This study sought to determine if patients undergoing shoulder arthroplasty using a postoperative opioid-sparing pain-control regimen would have equivalent pain scores and satisfaction as patients using a traditional opioid-based regimen.
Methods:
Patients undergoing primary anatomic or reverse total shoulder arthroplasty were prospectively enrolled and randomized into an opioid-sparing (OS) or a traditional opioid-based (OB) postoperative pain protocol. Both groups received opioid education, periarticular injection with liposomal bupivacaine, and preoperative and postoperative multimodal management (acetaminophen, celecoxib, and gabapentin). The OB group was discharged with 40 oxycodone tablets and standard icing, whereas the OS group received ketorolac during admission, continuous cryotherapy, and discharged with 10 oxycodone tablets for rescue. Patients were queried regarding levels of pain and opioid consumption at days 1-7 and at 2, 6, and 12 weeks postoperatively. Patient satisfaction was recorded at 1, 2, 6, and 12 weeks. Range of motion (ROM), American Shoulder and Elbow Surgeons Standardized Shoulder Assessment Form (ASES), and Single Assessment Numerical Evaluation (SANE) scores were assessed preoperatively and at 12 weeks postoperatively. Complications, readmissions, and reoperations were recorded.
Results:
In 78 patients, no difference in VAS pain scores were seen at any time between groups. The OS group consumed less oral morphine equivalents (OME) from inpatient hospitalization to 12 weeks postoperatively (P < .05). Total OME consumption was reduced by 213% for the OS vs. the OB group (112 vs. 239; P < .0001). The OS group consumed fewer opioid pills at all time points (P < .05). A 395% reduction in number of opioid pills consumed in the first 12 weeks postoperatively was seen in the OS vs. the OB group (4.3 vs. 17.0; P < .0001). Significantly more patients in the OS group discontinued opioids by 2 weeks postoperatively (86.1% vs. 58.5%; P = .011), and 94.4% in the OS group discontinued opioids by 6 weeks postoperatively. The OS group was more satisfied with pain management at 1 and 6 weeks (P = .05). No difference in ROM, ASES or SANE scores, complications, readmissions, or reoperations were seen between groups.
Conclusions:
This study demonstrated a nearly 4-fold reduction in opioid pain pill consumption and earlier cessation of opioids with an OS pain management protocol. Patients also reported higher satisfaction with this pain management strategy.
More Related Videos

Related Concept Videos
 01:15
Opioid Analgesics: Synthetic and Semisynthetic Opioids
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:25
Analgesia and Pain Management
 01:20
Opioid Analgesics: Morphine and Other Natural Cogeners
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...