Related Experiment Video
Updated: Sep 5, 2025
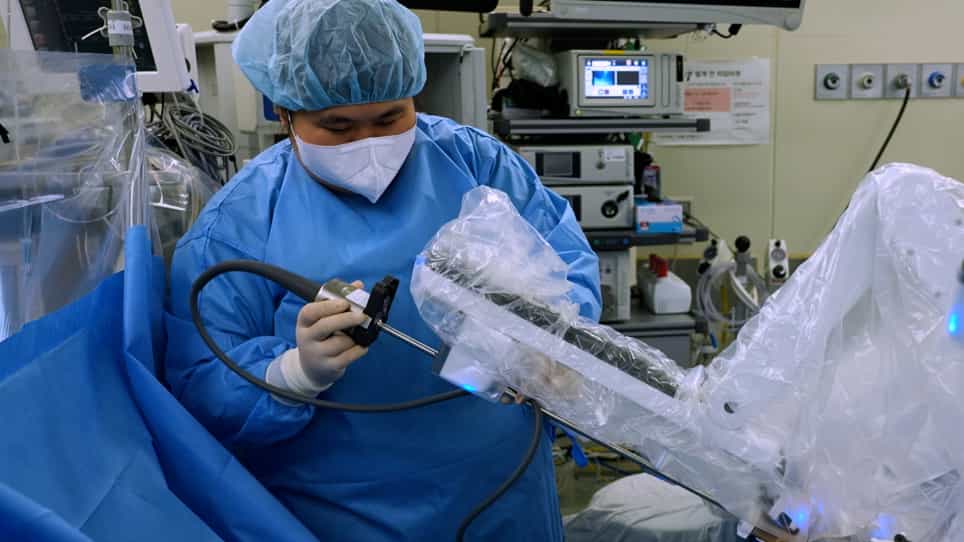
Robot-Assisted Kidney Transplantation
Published on: July 19, 2021
Continuous Renal Replacement Therapy in Pediatric Patients With Acute Kidney Injury After Liver Transplantation
Yan Sun1,2, Sinan Gao1,2, Xingqiang Wang1,2
1Organ Transplantation Center, Tianjin First Central Hospital, Tianjin, China.

Insights
Continuous renal replacement therapy (CRRT) is crucial for pediatric acute kidney injury (AKI) post-liver transplant. While CRRT is linked to lower survival rates, it effectively improves outcomes for critically ill children.
Area of Science:
- Pediatric Nephrology
- Transplant Surgery
- Critical Care Medicine
Background:
- Acute kidney injury (AKI) is a significant complication in pediatric liver transplant recipients.
- Early identification and management of AKI are critical for improving patient prognosis.
Purpose of the Study:
- To investigate the clinical application and outcomes of continuous renal replacement therapy (CRRT) in pediatric patients with AKI following liver transplantation.
- To identify risk factors associated with the need for CRRT in this patient population.
Main Methods:
- Retrospective analysis of pediatric liver transplant patients who developed AKI within one year post-transplant.
- Comparison of perioperative conditions, postoperative complications, and prognoses between patients who received CRRT and those who did not.
- Multivariate logistic regression to identify risk factors for CRRT use.
Main Results:
- 189 patients (36.91%) developed AKI post-liver transplant; 18 received CRRT.
- CRRT patients had higher rates of intraoperative hemorrhage, unscheduled surgery, primary nonfunction, and hepatic artery occlusion.
- AKI stage 3, unscheduled surgery, and hepatic artery occlusion were significant risk factors for CRRT.
- CRRT initiation was typically around postoperative day 10, with an average of 2 treatments per patient.
Conclusions:
- Pediatric liver transplant recipients with severe AKI (stage 3), hepatic artery occlusion, or requiring unscheduled surgery are more likely to need CRRT.
- While CRRT use is associated with lower survival rates, it is a necessary intervention for critically ill patients.
- CRRT effectively improved survival rates in this cohort, highlighting its importance in managing severe AKI post-liver transplant.
Objective:
This study aimed to explore the clinical application of continuous renal replacement therapy (CRRT) in pediatric patients with acute kidney injury (AKI) after liver transplantation.
Methods:
Pediatric patients who underwent liver transplantation were retrospectively investigated. Those who developed AKI within 1 year after the surgery were included and divided into a CRRT group and a non-CRRT group. The perioperative conditions and postoperative complications of the two groups were compared along with the prognoses of the groups to analyze the high-risk factors of the postoperative CRRT.
Results:
189 (36.91%) patients developed AKI within 1 year after the liver transplantation surgery. There were 18 patients in the CRRT group and 171 in the non-CRRT group. The differences in the preoperative conditions were not statistically significant between the two groups. Compared with the non-CRRT group, patients in the CRRT group had significantly longer transplantation times, higher volumes of intraoperative hemorrhage, and increased incidence of postoperative unscheduled surgery, postoperative primary nonfunction of the transplanted liver, secondary liver transplantation, hepatic artery occlusion, and intestinal fistula (P < 0.05). Moreover, the proportion of patients in AKI stage 3 is higher in the CRRT group (83.33%) than that in the non-CRRT group (11.11%), P < 0.001. The median time to initiate CRRT was 10 days postoperatively, the median number of CRRT treatments per patient was 2 times, the average duration of each CRRT treatment was 10.1 h, and the average rate of the decrease in blood creatinine per treatment was 25.6%. Results of multivariate logistic regression analysis showed that AKI stage 3 [OR=40.000, 95%CI (10.598, 150.969), P = 0.016], postoperative unscheduled surgery [OR=6.269, 95%CI (3.051, 26.379), P = 0.007], and hepatic artery occlusion [OR = 17.682, 95%CI (1.707, 40.843), P = 0.001] were recognized as risk factors for postoperative AKI with CRRT therapy. The one- and two-year survival rates were 72.22% and 72.22% in the CRRT group, respectively; and 97.08% and 96.49% in the non-CRRT group, accordingly. There were statistically significant differences in the one- and two-year survival rates between the two groups (P < 0.001).
Conclusion:
The incidence of AKI after liver transplantation in pediatric patients was high. Patients with AKI stage 3, hepatic artery occlusion, and underwent unscheduled surgery postoperatively were with a high likelihood of receiving CRRT, which was related to a lower one- and two-year survival rates. CRRT effectively improved the one- and two-year survival rates.


Related Concept Videos
 01:30
Continuous Renal Replacement Therapy
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:26
Kidney Transplant II: Surgical Procedure
 01:28
Kidney Transplant I: Introduction
 01:22
Acute Kidney Injury I: Introduction
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention