Related Experiment Video
Updated: Sep 5, 2025
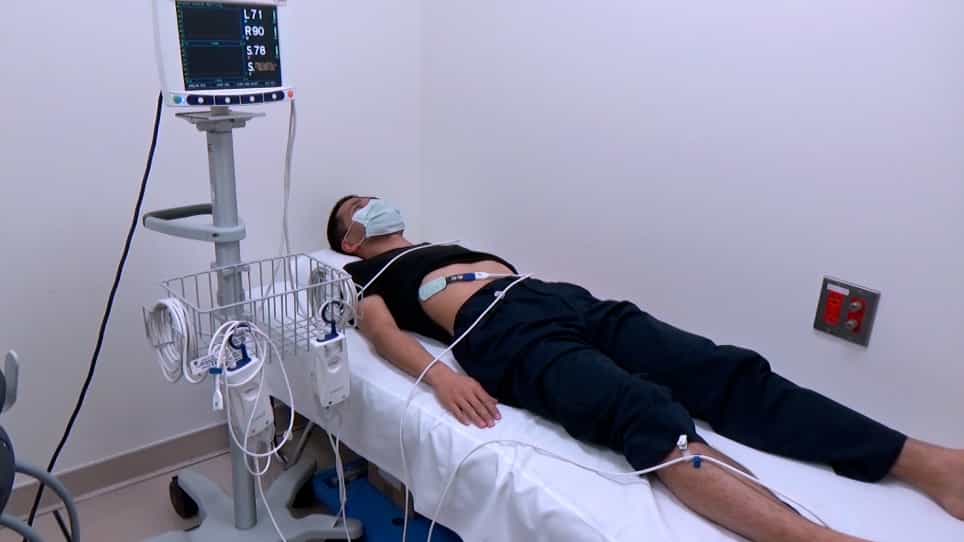

Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
Could incremental haemodialysis be a new standard of care? A suggestion from a long-term observational study
Francesco G Casino1, Teodoro Lopez2, Giovanni Santarsia2
1Dialysis Centre SM2, Policoro (Matera), Italy.

Introduction: The term incremental haemodialysis (HD) means that both dialysis dose and frequency can be low at dialysis inception but should be progressively increased, to compensate for any subsequent reduction in residual kidney function. Policy of the Matera Dialysis Center is to attempt an incremental start of HD without a strict low-protein diet in all patients choosing HD and with urine output (UO) >500 ml/day. The present study aimed at analyzing the results of this policy over the last 20 years. Subjects and methods: The dataset of all patients starting HD between January 1st, 2000 and December 31st, 2019 was retrieved from the local electronic database. Exclusion criteria were: urine output <500 ml/day or follow-up <3 months after the start of the dialysis treatment. Results: A total of 266 patients were retrieved; 64 of them were excluded from the study. The remaining 202 patients were enrolled into the study and subdivided into 3 groups (G1, G2 and G3) according to the frequency of treatment at the start of dialysis: 117 patients (57.9%) started with once-a-week (1HD/wk) (G1); 46 (22.8%) with twice-a-week (2HD/wk) (G2); 39 (19.3%) with thrice-a-week (3HD/wk) dialysis regimen (G3). Patients of G1 remained on 1HD/wk for 11.9 ±14.8 months and then transferred to 2HD/wk for further 13.0 ±20.3 months. Patients of G2 remained on 2HD/wk for 16.7 ±23.2 months. Altogether, 25943 sessions were administered during the less frequent treatment periods instead of 47988, that would have been delivered if the patients had been on 3HD/wk, thus saving 22045 sessions (45.9%). Gross mortality of the entire group was 12.6%, comparable to the mean mortality of the Italian dialysis population (16.2%). Survival at 1 and 5 years was not significantly different among the 3 groups: 94% and 61% (G1); 83% and 39% (G2); 84% and 46% (G3). Conclusions: Our long-term observational study suggests that incremental HD is a valuable option for incident patients. For most of them (80.7%) it is viable for about 1-2 years, with obvious socio-economic benefits and survival rates comparable to that of the Italian dialysis population. However, randomized controlled trials are lacking and therefore urgently needed. If they will confirm observational data, incremental HD will be a new standard of care.
Introduction: The term incremental haemodialysis (HD) means that both dialysis dose and frequency can be low at dialysis inception but should be progressively increased, to compensate for any subsequent reduction in residual kidney function. Policy of the Matera Dialysis Center is to attempt an incremental start of HD without a strict low-protein diet in all patients choosing HD and with urine output (UO) >500 ml/day. The present study aimed at analyzing the results of this policy over the last 20 years. Subjects and methods: The dataset of all patients starting HD between January 1st, 2000 and December 31st, 2019 was retrieved from the local electronic database. Exclusion criteria were: urine output <500 ml/day or follow-up <3 months after the start of the dialysis treatment. Results: A total of 266 patients were retrieved; 64 of them were excluded from the study. The remaining 202 patients were enrolled into the study and subdivided into 3 groups (G1, G2 and G3) according to the frequency of treatment at the start of dialysis: 117 patients (57.9%) started with once-a-week (1HD/wk) (G1); 46 (22.8%) with twice-a-week (2HD/wk) (G2); 39 (19.3%) with thrice-a-week (3HD/wk) dialysis regimen (G3). Patients of G1 remained on 1HD/wk for 11.9 ±14.8 months and then transferred to 2HD/wk for further 13.0 ±20.3 months. Patients of G2 remained on 2HD/wk for 16.7 ±23.2 months. Altogether, 25943 sessions were administered during the less frequent treatment periods instead of 47988, that would have been delivered if the patients had been on 3HD/wk, thus saving 22045 sessions (45.9%). Gross mortality of the entire group was 12.6%, comparable to the mean mortality of the Italian dialysis population (16.2%). Survival at 1 and 5 years was not significantly different among the 3 groups: 94% and 61% (G1); 83% and 39% (G2); 84% and 46% (G3). Conclusions: Our long-term observational study suggests that incremental HD is a valuable option for incident patients. For most of them (80.7%) it is viable for about 1-2 years, with obvious socio-economic benefits and survival rates comparable to that of the Italian dialysis population. However, randomized controlled trials are lacking and therefore urgently needed. If they will confirm observational data, incremental HD will be a new standard of care.


Related Concept Videos
 01:25
Hemodialysis I: Introduction
 01:24
Hemodialysis II: Procedure and Complications
 01:25
Hemodialysis III: Nursing Management
 01:30
Continuous Renal Replacement Therapy
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:28
Chronic Kidney Disease III: Interprofessional Care