Related Experiment Video
Updated: Sep 4, 2025

Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Exertional dyspnoea in patients with mild-to-severe chronic obstructive pulmonary disease: neuromechanical mechanisms
Matthew D James1, Devin B Phillips1, Sandra G Vincent1
1Respiratory Investigation Unit, Department of Medicine, Queen's University and Kingston Health Sciences Centre, Kingston, Ontario, Canada.

Abstract:
In patients with chronic obstructive pulmonary disease (COPD), exertional dyspnoea generally arises when there is imbalance between ventilatory demand and capacity, but the neurophysiological mechanisms are unclear. We therefore determined if disparity between elevated inspiratory neural drive (IND) and tidal volume (VT ) responses (neuromechanical dissociation) impacted dyspnoea intensity and quality during exercise, across the COPD severity spectrum. In this two-centre, cross-sectional observational study, 89 participants with COPD divided into tertiles of FEV1 %predicted (Tertile 1 = FEV1 = 87 ± 9%, Tertile 2 = 60 ± 9%, Tertile 3 = 32 ± 8%) and 18 non-smoking controls, completed a symptom-limited cardiopulmonary exercise test (CPET) with measurement of IND by diaphragm electromyography (EMGdi (%max)). The association between increasing dyspnoea intensity and EMGdi (%max) during CPET was strong (r = 0.730, P < 0.001) and not different between the four groups who showed marked heterogeneity in pulmonary gas exchange and mechanical abnormalities. Significant inspiratory constraints (tidal volume/inspiratory capacity (VT /IC) ≥ 70%) and onset of neuromechanical dissociation (EMGdi (%max):VT /IC > 0.75) occurred at progressively lower minute ventilation ( ) from Control to Tertile 3. Lower resting IC meant earlier onset of neuromechanical dissociation, heightened dyspnoea intensity and greater propensity (93% in Tertile 3) to select qualitative descriptors of 'unsatisfied inspiration'. We concluded that, regardless of marked variation in mechanical and pulmonary gas exchange abnormalities in our study sample, exertional dyspnoea intensity was linked to the magnitude of EMGdi (%max). Moreover, onset of critical inspiratory constraints and attendant neuromechanical dissociation amplified dyspnoea intensity at higher exercise intensities. Simple measurements of IC and breathing pattern during CPET provide useful insights into mechanisms of dyspnoea and exercise intolerance in individuals with COPD. KEY POINTS: Dyspnoea during exercise is a common and troublesome symptom reported by patients with chronic obstructive pulmonary disease (COPD) and is linked to an elevated inspiratory neural drive (IND). The precise mechanisms of elevated IND and dyspnoea across the continuum of airflow obstruction severity in COPD remains unclear. The present study sought to determine the mechanisms of elevated IND (by diaphragm EMG, EMGdi (%max)) and dyspnoea during cardiopulmonary exercise testing (CPET) across the continuum of COPD severity. There was a strong association between increasing dyspnoea intensity and EMGdi (%max) during CPET across the COPD continuum despite significant heterogeneity in underlying pulmonary gas exchange and respiratory mechanical impairments. Critical inspiratory constraints occurred at progressively lower ventilation during exercise with worsening severity of COPD. This was associated with the progressively lower resting inspiratory capacity with worsening disease severity. Earlier critical inspiratory constraint was associated with earlier neuromechanical dissociation and greater likelihood of reporting the sensation of 'unsatisfied inspiration'.
More Related Videos
 09:33
Using Near-Infrared Spectroscopy Wearable Devices to Identify Central Versus Peripheral Limitations During Exercise
Published on: December 19, 2024
 04:53
Author Spotlight: Traditional Chinese Medicine for Sleep Disorders in Acute COPD — A Safe, Cost-Effective Approach
Published on: October 18, 2024
Related Concept Videos
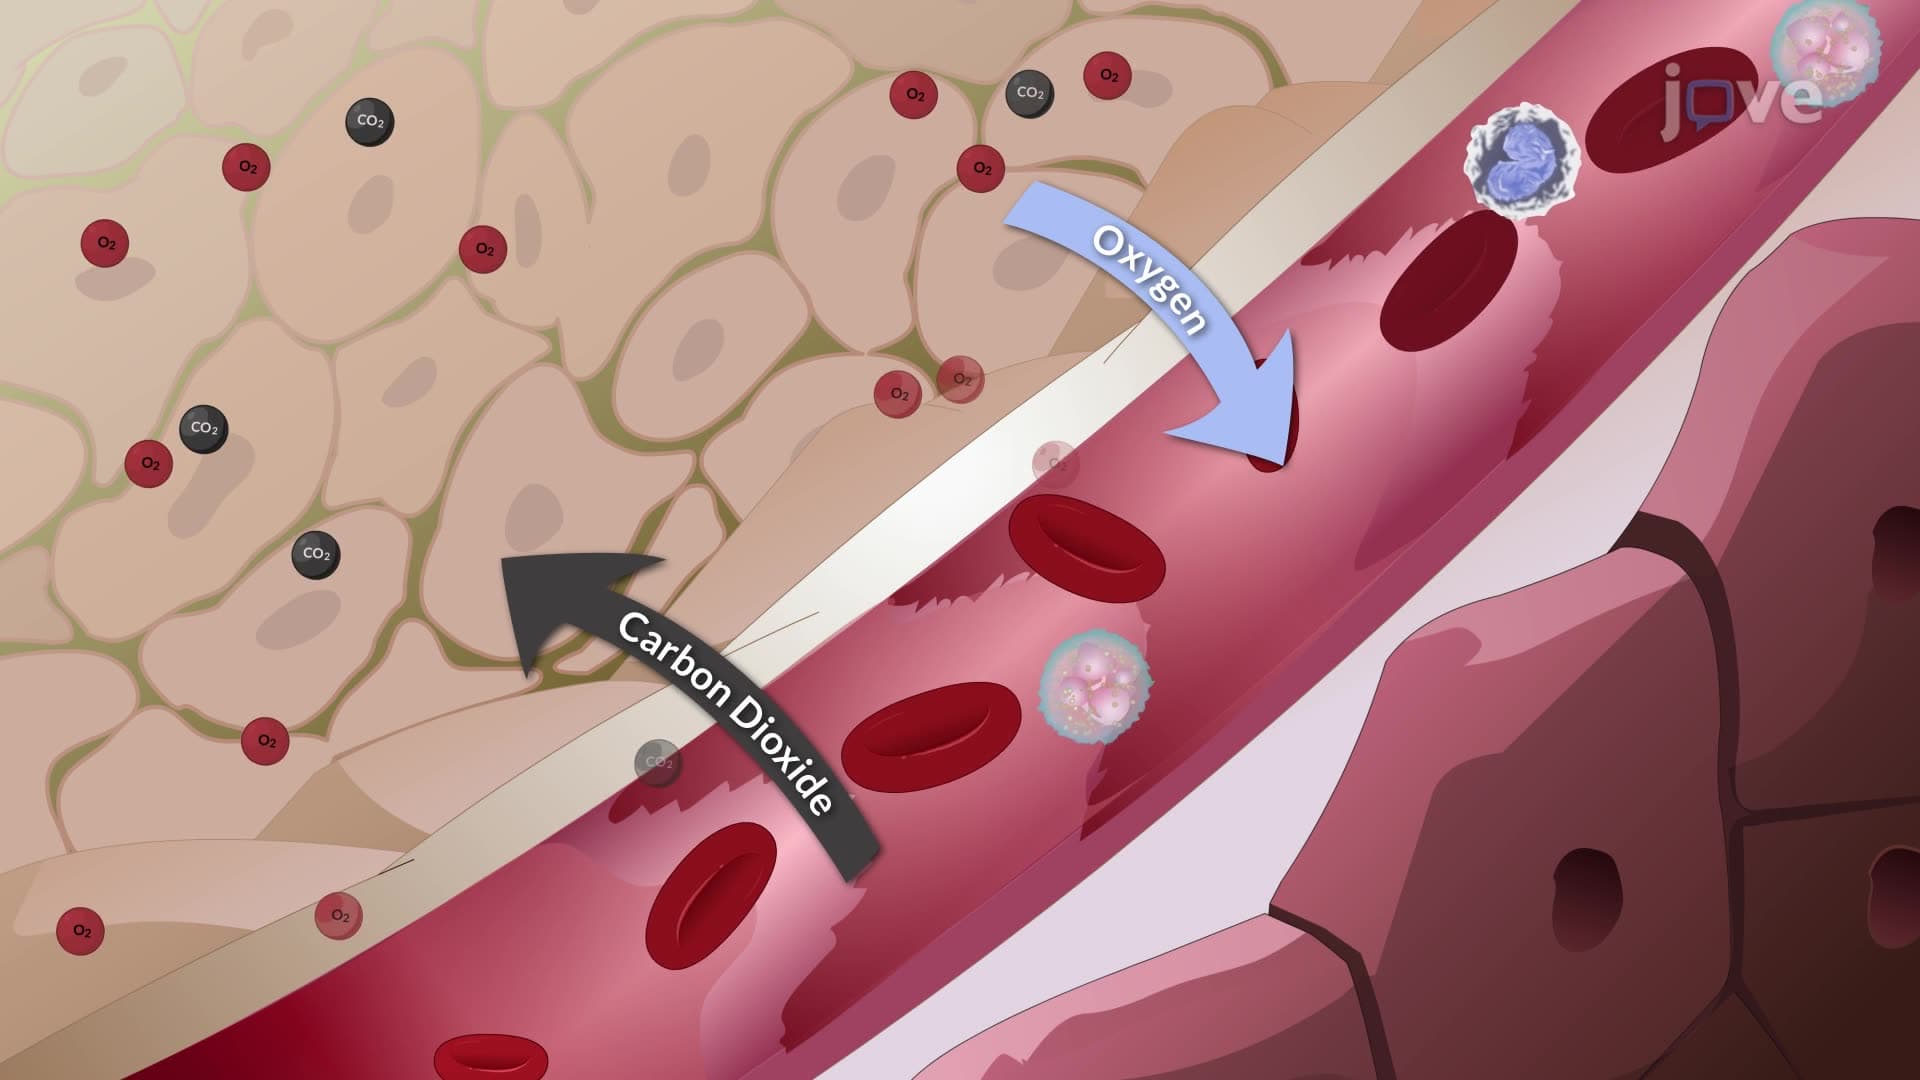 01:21
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:23
Mechanism of Breathing II: Expiration
Expiration, or exhaling, is a complex physiological process that begins as the inspiratory muscles begin to relax. This relaxation triggers a series of events that epitomize the efficiency of the respiratory system.
Mechanism of Expiration: