Related Experiment Video
Updated: Sep 3, 2025


Endoscopic Septoplasty with Limited Two-line Resection: Minimally Invasive Surgery for Septal Deviation
Published on: June 20, 2018
Rhinomanometry with and without decongestant used to select children for adenoidectomy: a cohort study
Christian Calvo-Henriquez1,2, Irene Rivero3,4, Byron Maldonado-Alvarado3,5
1Rhinology Study Group of the Young-Otolaryngologists of the International Federations of Oto-Rhino-Laryngological Societies (YO-IFOS), Paris, France. christian.ezequiel.calvo.henriquez@sergas.es.

Objective:
Adenoid hypertrophy may coexist, and often does, with rhinitis. Therefore, in some cases, adenoidectomy alone, despite the fact that it reduces nasal resistance, may be insufficient to restore nasal breathing. Juliusson et al. suggested using rhinomanometry with and without nasal decongestant as a method for selecting patients for adenoidectomy. In this study, we aim to assess whether the decongestant test, when using normative data, is useful to select children for adenoidectomy.
Methods:
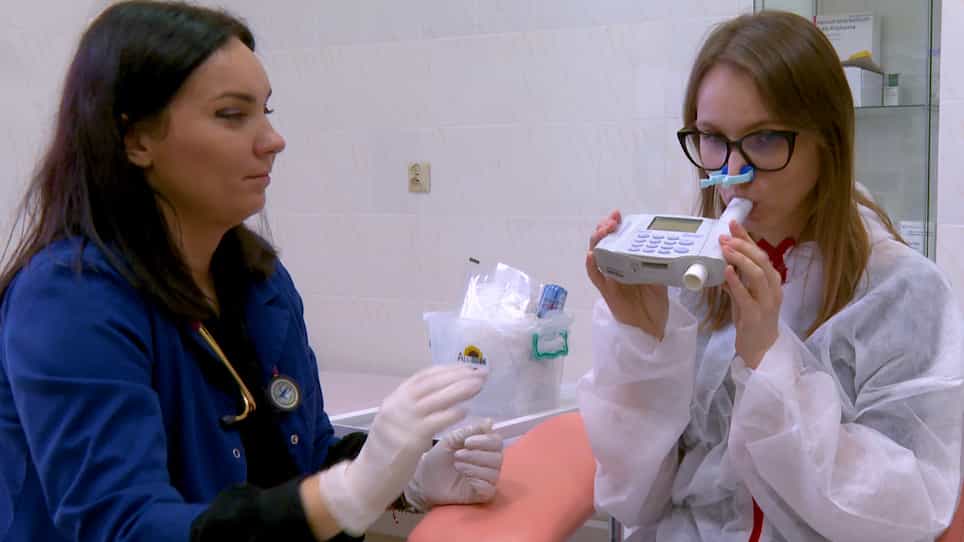
Children between 4 and 15 years old undergoing adenoidectomy were selected from two tertiary referral university hospitals. Participants underwent anterior active rhinomanometry with and without nasal decongestant before and after surgery. Parents fill in the sinus and nasal quality-of-life survey (SN5).
Results:
47 participants were included, and mean age 6.5 ± 2.15. 2 cohorts were defined according to the result of the nasal decongestant test (> 40% improvement in nasal resistance or not). There is a statistically significant difference between groups, with a higher improvement in nasal resistance and airflow after adenoidectomy in the group with less than 40% improvement in nasal resistance.
Conclusions:
In conclusion, this study supports the use of the decongestant test with rhinomanometry to select children for adenoidectomy; especially as it has proven to be a simple technique, harmless, fast, and easily performed on collaborative children.

Related Concept Videos
 01:27
Upper Respiratory Drugs: Decongestants
Most decongestants are readily available over-the-counter in...
 01:16
Drugs Used in Upper Respiratory Disorders: Overview
Antihistamines (e.g., Benadryl) block histamines from binding. Histamines are chemicals released during an allergic reaction in the body. As a...
 01:23
Upper Respiratory Drugs: Antitussives, Expectorants, and Mucolytics
Antitussives include codeine, dextromethorphan (Robitussin), and benzonatate (Tessalon). Codeine and dextromethorphan exert their effects centrally by suppressing the cough reflex center in the medulla. Benzonatate operates peripherally within the respiratory tract by...
 01:29
Suctioning the Nasopharyngeal Airway
Equipment Required
 01:28
Adrenergic Agonists: Mixed-Action Agents
Ephedrine and pseudoephedrine lack a catecholamine group, making them less susceptible to degradation by metabolic enzymes. They have increased oral bioavailability and lipophilicity, resulting in a longer duration of action. Their response is reduced by...
 01:30
Epistaxis
Etiology
Possible causes of this condition include high blood pressure, trauma, low humidity, upper respiratory tract infections, allergies, foreign bodies, nasal inhalation of corticosteroids or illicit drugs, excessive use of decongestant nasal sprays, facial or nasal surgery, anatomic malformation, tumors, or systemic...